
Introduction
Congenital hypothyroidism (CH) is one of the most prevalent endocrine disorders among children and is a common preventable cause of mental retardation in childhood [1]. Early initiation of treatment within the first weeks of life significantly improves neurodevelopmental outcomes [2]. Implementing newborn thyroid screening with lower thyroid-stimulating hormone (TSH) thresholds has increased the incidence of CH from 1 in 4,000 to 1 in 2,000 [3].
CH can be transient or permanent. Thyroid dysgenesis accounts for 80% of permanent cases, including thyroid aplasia, hypoplasia, or ectopic gland, while thyroid dyshormonogenesis accounts for 20% of cases [4].
Accurate determination of the underlying cause of CH is crucial for establishing an appropriate lifelong treatment plan. Thyroid imaging modalities, including thyroid scintigraphy and ultrasonography, are valuable, accurate diagnostic tools [5]. Scintigraphy yields reliable results within 7–10 days after treatment initiation [6]. It is the ideal modality for detecting ectopic thyroid glands, whereas ultrasonography effectively identifies cases of thyroid aplasia or hypoplasia but not ectopic glands [7]. However, each modality has its limitations and pitfalls.
Given the constraints of resource-limited settings and the lack of access to routine imaging for every CH patient, this study aimed to evaluate the diagnostic performance of thyroid scintigraphy and ultrasonography in detecting the etiology of thyroid dysgenesis in patients with permanent CH. The goal was to establish a stepwise approach to imaging modalities for managing CH in our community.
Material and methods
Patients
This observational cross-sectional study was conducted over 12 months, from February 2023 to February 2024. It included patients diagnosed with permanent congenital primary hypothyroidism due to thyroid dysgenesis who were followed up at the Endocrinology Clinic of the Diabetes, Endocrine, and Metabolism Pediatric Unit, Cairo University, Children’s Hospital.
Fifty-six patients with permanent congenital primary hypothyroidism were enrolled. These patients were diagnosed either through neonatal screening or after presenting with suggestive symptoms of hypothyroidism, such as constipation and developmental delay, accompanied by elevated TSH and low thyroxine (T4) and free thyroxine (FT4) levels. All included patients had thyroid dysgenesis (ectopia, hypoplasia, or agenesis), confirmed by 99mTc thyroid scintigraphy performed at the time of initial diagnosis before initiating hormonal replacement therapy. All participants underwent thyroid ultrasonography. Patients with CH who had a normal or enlarged thyroid gland on thyroid scintigraphy and patients with chronic systemic illnesses were excluded.
Methodology
All study participants were subjected to the following evaluations:
History
A comprehensive history was taken, including sex, residence, gestational age, birth weight, current age, and age at diagnosis. The disease history covered the following aspects:
duration of illness (from the date of diagnosis to the present);
follow-up duration;
abnormalities noted in the neonatal screening test;
detailed history of disease onset, focusing on presenting manifestations;
history of other disease presentations, such as developmental delay, tongue base mass, constipation, and prematurity;
other associated clinical conditions;
treatment history, including details on school performance reports or learning disabilities, family history of the same condition, and hormonal replacement therapy (dose, compliance, and follow-up intervals).
Clinical examination
A single experienced endocrinologist performed the clinical examination, which included:
Laboratory investigations
Thyroid function test results (serum-FT4 and TSH levels) were retrieved from patient records at the time of initial diagnosis and at recruitment:
Thyroid imaging study
Thyroid scintigraphy. The results of 99mTc-pertechnetate thyroid scintigraphy performed at the time of initial diagnosis were retrieved. Spot views of the neck were acquired using gamma cameras 20 minutes after injecting 185 MBq (5 mCi) of the tracer.
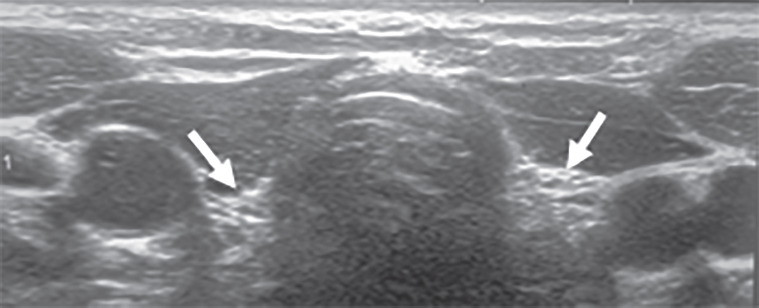
Thyroid ultrasonography. A single operator performed thyroid ultrasonography on all patients using a high-frequency linear-array transducer (10–17 MHz). No special preparations were required. The scan was conducted with the patient in a supine position, with the neck extended using a folded towel under the shoulders. A detailed scan was performed in both the transverse and longitudinal planes, covering the entire embryological path of the thyroid from the base of the tongue to the mediastinum. Scans included the thyroid gland, isthmus, cervical lymph nodes, and mediastinal thymus. Thyroid volume was calculated using the ellipsoid formula: width × length × height × 0.523. There is a lack of universal agreement on normal pediatric thyroid dimensions (Figure 1).
Sample size
The sample size for the study was calculated using the PASS 11 sample size calculator with the following parameters: alpha error: 0.05; confidence interval: 0.95; and power of the study: 0.80. The minimal sample size required was 47 cases of children with CH due to thyroid dysgenesis.
Sampling technique
A convenient sampling method was used, where patients who met the inclusion and exclusion criteria were recruited for the study until the total sample size of 47 was reached.
Statistical analysis of the data
Statistical analysis was conducted using IBM SPSS Statistics version 27. Categorical variables were presented as numbers and percentages and compared between groups using the χ2 test. Quantitative variables were presented as mean, standard deviation, minimum, and maximum. Diagnostic indices were calculated using 2 × 2 contingency tables, and a p-value < 0.05 was considered significant. Sensitivity (true positive rate) refers to the probability of a positive test result among individuals who truly have the disease. Specificity (true negative rate) refers to the probability of a negative test result among individuals who truly do not have the disease. A false positive refers to a test result indicating the presence of a disease in an individual who does not actually have the disease. A false negative refers to a negative test result in an individual who actually has the disease. Positive predictive value refers to the probability that individuals with a positive test result truly have the disease. Negative predictive value refers to the probability that individuals with a negative test result truly do not have the disease.
Bioethical standards
The study was approved by the institutional review board of Kasr Al-Ainy Medical School (Cairo University) (IRB: MS-601-2022) on March 30, 2023, and adhered to the principles of the Declaration of Helsinki. Written informed consent was obtained from the patient’s legal guardian for participation in the research. Informed consent was obtained from both parents and children for those above 7 years, but for children younger than 7 years consent was obtained from their parents only.
Results
Patients' characteristics
Fifty-six patients with permanent CH due to thyroid dysgenesis were enrolled in the study. The mean age of the recruited patients was 14.26 ±5.43 years, with the median age at diagnosis being 14 days. Female patients predominated, accounting for 76.8%, compared to 23.2% male patients. Most of the patients (80.4%) were diagnosed and started treatment before the age of one month. However, 11 (19.6%) patients experienced a delayed diagnosis. Twenty-one (37.5%) patients were born to consanguineous parents. A family history of thyroid disease was positive in 11 (19.6%) patients, seven of whom had CH. All patients (100%) were born at full-term pregnancy. The children’s mean birth weight was 3.04 ±0.41 kg; four patients were born with low birth weight (< 2.5 kg).
All patients underwent a dried blood spot screening test for thyroid functions at birth. Abnormal screening results were reported in 42 (75%) patients, while 12 patients (21.4%) showed normal results, and two patients missed their test results (Table I).
Table I
Demographic and clinical characteristics of recruited patients (N = 56)
Thyroid imaging study (thyroid scintigraphy and thyroid ultrasonography)
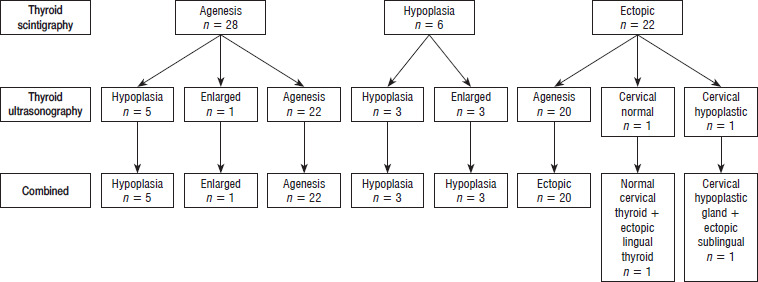
Thyroid scintigraphy revealed that 28 (50%) patients had thyroid agenesis, 22 (39.3%) patients had ectopic thyroid tissue (lingual in 3 patients and sublingual in 19 patients), and hypoplasia was diagnosed in 6 (10.7%) patients. Ultrasonography revealed that 45 (80.4%) patients had thyroid agenesis, 9 (16.1%) patients had thyroid hypoplasia, 1 patient had an enlarged thyroid gland, and 1 patient had normal cervical thyroid tissue and failed to detect any ectopic thyroid tissue.
The final diagnosis was based on combining both modalities and reviewing the clinical features, as illustrated in Figure 2. It showed that 22 (39.3%) patients had thyroid agenesis, 20 (37.5%) patients had ectopic thyroid, 11 (19.6%) patients had thyroid hypoplasia, 1 patient had goiter in the cervical gland, 1 patient had normal cervical thyroid with ectopic lingual thyroid, and another patient had a cervical hypoplastic gland with ectopic sublingual thyroid. Thyroid scintigraphy was the only modality that detected ectopic thyroid tissues. Additionally, there was inconsistency between the ultrasonographic diagnosis and final diagnosis in 20 cases, which were diagnosed as agenesis by ultrasonography but as ectopic by the final diagnosis.
Figure 2
Distribution of patients according to thyroid scintigraphy and thyroid ultrasonography separately and the final diagnosis according to the combined modalities
The thyroid scintigraphy showed a sensitivity of 96% and a diagnostic accuracy of 85.7%. However, ultrasonography showed a sensitivity of 56.4% and a diagnostic accuracy of 92.9%. The combination of both imaging modalities showed 100% sensitivity and 100% accuracy. Ultrasonography sensitivity was highest in diagnosing thyroid hypoplasia (75%) and agenesis (100%). However, ultrasonography lacked sensitivity in diagnosing ectopic thyroid. Regarding accuracy, ultrasonography was most accurate (94.7%) in diagnosing hypoplasia but not accurate at all in diagnosing ectopic glands. Thyroid scintigraphy showed the highest sensitivity for diagnosing ectopic glands and agenesis (100%). However, it was less sensitive in diagnosing hypoplasia (54.5%). Regarding accuracy, scintigraphy was 100% accurate in diagnosing ectopic glands but less accurate (89.4%) in diagnosing hypoplasia and agenesis (89.3%) (Table II).
Table II
Diagnostic indices of thyroid scintigraphy and thyroid ultrasonography of each diagnosis
Comparison between different groups of patients according to final diagnosis
Patients were categorized into three groups according to the final diagnosis (agenesis, ectopic thyroid gland, and hypoplasia). We found that gender, age at diagnosis, region, natal history, postnatal history, birth weight, consanguinity, family history, initial newborn thyroid screening results, and Tanner staging showed no statistically significant difference between the groups.
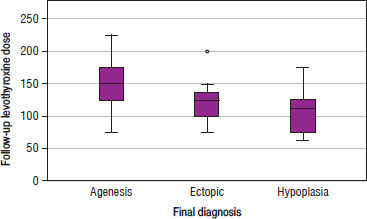
No statistically significant differences were detected regarding the initial dose of thyroid hormone replacement therapy, initial thyroid hormone profile, and follow-up thyroid hormone profile between the groups, with p-values of 0.184, 0.147, 0.579, 0.725, and 0.598, respectively. However, the follow-up dose of thyroid hormone replacement therapy was significantly higher among patients with agenesis compared to those with hypoplasia and ectopic thyroid, with a p-value of 0.01 (Table III and Figure 3).
Table III
Comparison of clinical characteristics, anthropometric measurements, and hormonal profile of patients according to final diagnosis
Discussion
Thyroid dysgenesis is the predominant etiological factor for permanent CH in pediatrics [8]. Prompt treatment and identification of the underlying cause, along with achieving euthyroid status, are crucial for normal brain development during early childhood. Additionally, determining the cause is essential for parental counseling regarding lifelong hormonal replacement therapy [9]. Consequently, thyroid gland visualization using imaging modalities such as ultrasonography, scintigraphy, or both is recommended [10]. However, some clinicians do not routinely recommend such imaging in resource-limited settings.
In this study, we assessed the diagnostic accuracy of thyroid ultrasonography compared to thyroid scintigraphy in categorizing the type of thyroid dysgenesis.
Our findings revealed that ultrasonography failed to detect any ectopic thyroid tissue. Scintigraphy was the sole modality capable of detecting ectopic thyroid glands with 100% sensitivity and accuracy. Among the 20 cases diagnosed with ectopic thyroid by scintigraphy, ultrasonography failed to detect any thyroid tissue and incorrectly diagnosed these cases as agenesis. These findings align with the studies of Chun et al. [11], and Perry et al. [12], which identified scintigraphy as the preferred modality for detecting thyroid ectopia. The complete inability of ultrasonography to detect ectopic thyroid tissue in our study may be attributed to the use of gray-scale ultrasonography instead of color Doppler ultrasonography, as previous studies have reported better detection rates with the latter [13, 14]. Moreover, it likely reflects the small size and atypical location of the glands, in addition to the operator-dependent nature of the modality. Once identified on scintigraphy, targeted ultrasonographic examination may aid in the subsequent localization and follow-up of the ectopic tissue.
Additionally, ultrasonography identified thyroid hypoplasia in one patient and normal thyroid tissue in another, both of whom were diagnosed with ectopic thyroid according to scintigraphy. Consequently, the final diagnosis of the two cases was revised to cervical hypoplastic gland with ectopic sublingual tissue for the first patient and normal cervical thyroid with ectopic lingual tissue for the second. According to the literature, normal thyroid tissue is undetectable in 70% of patients with ectopic thyroid, and the coexistence of an ectopic thyroid with a normal in situ cervical thyroid gland is exceedingly rare [15].
In our series, thyroid hypoplasia was detected in 19.6% (11/56) of patients. The reported frequency of thyroid hypoplasia varies widely in previous studies, ranging from 5% to 26% [12, 16, 17]. In our cohort, the sensitivity of ultrasonography for detecting thyroid hypoplasia was 75%, compared to 50% for scintigraphy. Discordance between the two modalities was noted in 6 patients initially diagnosed with agenesis by scintigraphy, where ultrasonography revealed hypoplastic thyroid tissue. These findings indicate that ultrasonography was superior to scintigraphy in identifying thyroid hypoplasia.
Several factors may complicate the accurate diagnosis of thyroid hypoplasia in infants. First, scintigraphy is more precise in assessing gland function than in morphological evaluation or volume measurement. Both hypoplastic and severely atrophic glands may exhibit reduced or absent tracer uptake due to markedly diminished thyroid activity, potentially leading to false-negative results. Second, technical errors such as low radioisotope dose, patient motion, or delayed imaging may further reduce the detectability of small or poorly functioning thyroid remnants. Third, the absence of normative cut-off values for thyroid gland measurements by ultrasonography in neonates presents another challenge. Finally, the very short neck of newborns may hinder accurate localization and measurement of the gland. Our study’s mean age of patients was 14.26 ±5.43 years, ranging from 4.72 to 25.4 years. We presume that our patients’ older age at the ultrasonographic evaluation contributed to more accurate gland localization and measurement.
Another notable finding in our study was the inability of the thyroid scintigraphy to detect thyroid tissue in a patient with a normally located cervical gland. This case involved a 12-year-old girl diagnosed with CH at 12 days of age via neonatal screening. Confirmatory venous TSH was 60 μIU/ml, and FT4 was 0.2 ng/dl. The initial thyroid scintigraphy suggested agenesis, leading to the immediate initiation of levothyroxine (L-T4) at 50 μg/day. The patient demonstrated proper control during the first five years of life but lost follow-up for the subsequent five years. At 10.5 years old, she presented with neck swelling, suspected to be goiter, and the mother disclosed cessation of replacement therapy for two years. Thyroid ultrasonography revealed multinodular goiter with an uncontrolled thyroid profile and negative thyroid antibodies.
The discrepancy between the initial diagnosis of agenesis and the later diagnosis of multinodular goiter raises the likelihood of a defect in iodine uptake, although molecular diagnostics were unavailable at our center. Despite detection by ultrasonography, commonly reported reasons for a scintigraphy’s failure to detect thyroid tissue include the presence of TSH receptor maternal blocking antibodies, prematurity, TSH receptor defects, and iodide trapping defects [12]. However, in our study, all patients were full-term, and thyroid scintigraphy was performed before initiating thyroid hormone replacement therapy, with TSH values ≥ 20 μIU/ml. This underscores the importance of dual imaging modalities for confirming the diagnosis of thyroid agenesis.
Ectopic thyroid tissue is the most common etiology of thyroid dysgenesis, with the lingual type being the most frequent site (90% of cases) [18]. However, in our cohort, sublingual ectopia was the predominant site, observed in 86.3% of cases (19/22), while the remaining cases had lingual thyroid. This finding aligns with the observations of Santangelo et al. [19], who reported a lower prevalence of lingual ectopic thyroid in their series.
Female sex predominance was evident in our cohort, accounting for 76.8% of the total cases and 75% of the ectopic cases. The underlying mechanisms of sexual dimorphism in thyroid dysgenesis remain unclear, with conflicting reports in the literature [20, 21].
It is well established that thyroid ultrasonography is superior to other imaging modalities, particularly thyroid scintigraphy, in several aspects, such as being radiation-free, not requiring patient sedation, and providing accurate visualization of in situ cervical thyroid tissue with precise evaluation of its dimensions [11]. However, thyroid ultrasonography is operator-dependent, posing challenges for patients residing far from imaging services. However, thyroid scintigraphy is excellent for detecting ectopic tissue, as demonstrated in our series. Combined thyroid ultrasonography and scintigraphy yielded 100% sensitivity and accuracy in diagnosing our cohort’s etiology of thyroid dysgenesis. Consistent with our findings, Lucas-Herald et al. [22] reported that combined imaging at the initial visit resulted in a correct final diagnosis in 79 of 97 (81%) cases. However, Supakul et al. [23] proposed using ultrasonography as the primary imaging modality for managing children with CH to reduce radiation exposure and cost. Their study showed that ultrasonography had high specificity (100%) but low sensitivity (44%) for detecting sublingual thyroid glands. Similarly, Karakoc-Aydiner et al. [16] emphasized that dual thyroid imaging is essential for accurately defining thyroid dysgenesis.
Based on our experience as a limited-resource tertiary referral center serving patients from various governorates, we recommend initiating thyroid scintigraphy as the primary imaging modality for evaluating thyroid dysgenesis. These steps must occur during rapid, prescheduled visits, as initiating hormonal replacement therapy and subsequent TSH suppression may impair radioisotope uptake by the thyroid. In resource-limited settings, for patients who cannot undergo imaging studies at the time of initial diagnosis, the diagnostic approach is primarily guided by biochemical evaluation, with imaging deferred until 3 years of age, when temporary L-T4 withdrawal is feasible. It is well known that serum thyroglobulin measurement plays a critical role in measurement in the evaluation and categorization of etiological diagnosis of CH [6]. However, in our setting, this investigation is not routinely available and is not reimbursed by insurance. Due to these resource limitations, the use of thyroglobulin testing remains restricted to a few specialized centers. This limitation underlines the relevance of our study, which aims to optimize the use of other accessible diagnostic tools and propose a practical algorithm applicable in low-resource contexts.
Our study revealed that the initial venous thyroid profile did not effectively differentiate among the various types of thyroid dysgenesis at the time of diagnosis. Moreover, the initial dose of thyroid hormone replacement therapy did not vary significantly across the different types of dysgenesis. However, the current dose was significantly higher among patients with agenesis compared to other groups, supporting the concept that patients with athyreosis experience more severe hypothyroidism, necessitating strict follow-up visits.
In our series, all patients underwent dried blood spot screening for thyroid function at birth. Abnormal screening results were identified in 42 patients (75%), while 12 patients (21.4%) had normal results, and two patients had missing test results. Notably, 11 patients were diagnosed after one month of age, despite normal newborn screening (NBS) results, due to symptoms such as failure to thrive, prolonged jaundice, developmental delays, and excessive sleep. Previous studies have reported that 5–10% of CH cases yield false-negative results on NBS, with causes including sampling errors, transportation issues, inadequate follow-up, and technical errors [24].
Limitations
This study has certain limitations, including a small study population and the retrospective analysis of thyroid scintigraphy results from medical records. Additionally, the lack of molecular analysis for our patients is a significant limitation. Routine assessment of thyroglobulin levels in patients with athyreosis, which could confirm the diagnosis of true athyreosis, was not performed.
Conclusions
Combined thyroid ultrasonography and thyroid scintigraphy allow for accurate anatomical and structural characterization of thyroid dysgenesis. Thyroid scintigraphy is superior to ultrasonography in detecting athyreosis and ectopic thyroid tissue given its superior ability to detect functional and ectopic thyroid tissue. Neck ultrasonography can serve as a complementary second-line imaging technique, providing valuable anatomical information and facilitating the follow-up of residual or rudimentary thyroid tissue in the neck. Adopting this stepwise and complementary imaging approach may enhance the accuracy of etiological diagnosis, which is essential for optimizing long-term management and guiding lifelong follow-up in patients with CH.










