
Summary
Retrograde chronic total occlusions-percutaneous coronary intervention (CTO-PCI) is increasingly used for complex CTO revascularization, yet the impact of older age on the individual procedural steps of the retrograde approach remains uncertain. In this multicenter analysis, older age was associated with more challenging collateral anatomy and lower collateral and retrograde crossing success, and independently predicted retrograde crossing failure after inverse probability of treatment weighting (IPTW) adjustment. These findings suggest that age should be considered in procedural planning, with meticulous collateral assessment and timely consideration of alternative crossing strategies to improve the likelihood of successful retrograde crossing.
Introduction
Retrograde percutaneous coronary intervention (PCI) is a key component of the hybrid approach to treating chronic total occlusions (CTO) [1–3]. The development and wider adoption of retrograde techniques have substantially increased procedural success in CTO-PCI [4]. However, retrograde CTO-PCI is also associated with higher procedural complexity, longer procedure duration, and a higher risk of complications compared with antegrade strategies alone [5, 6].
Older age has been associated with higher procedural risk and complication rates in CTO-PCI [7, 8]. However, the association of older age, particularly in patients aged ≥ 65 years, with retrograde CTO-PCI remains poorly understood. Specifically, data regarding the influence of older age on collateral channel availability, collateral crossing, and all stages of the retrograde approach remain limited.
Aim
Therefore, the aim of this study was to investigate age-related changes in all procedural stages of retrograde CTO-PCI and to evaluate the procedural characteristics and outcomes of retrograde PCI in elderly patients.
Material and methods
Study population
This study included consecutive retrograde CTO-PCI procedures performed at four centers from January 2019 to April 2026, with procedures performed by experienced CTO operators.
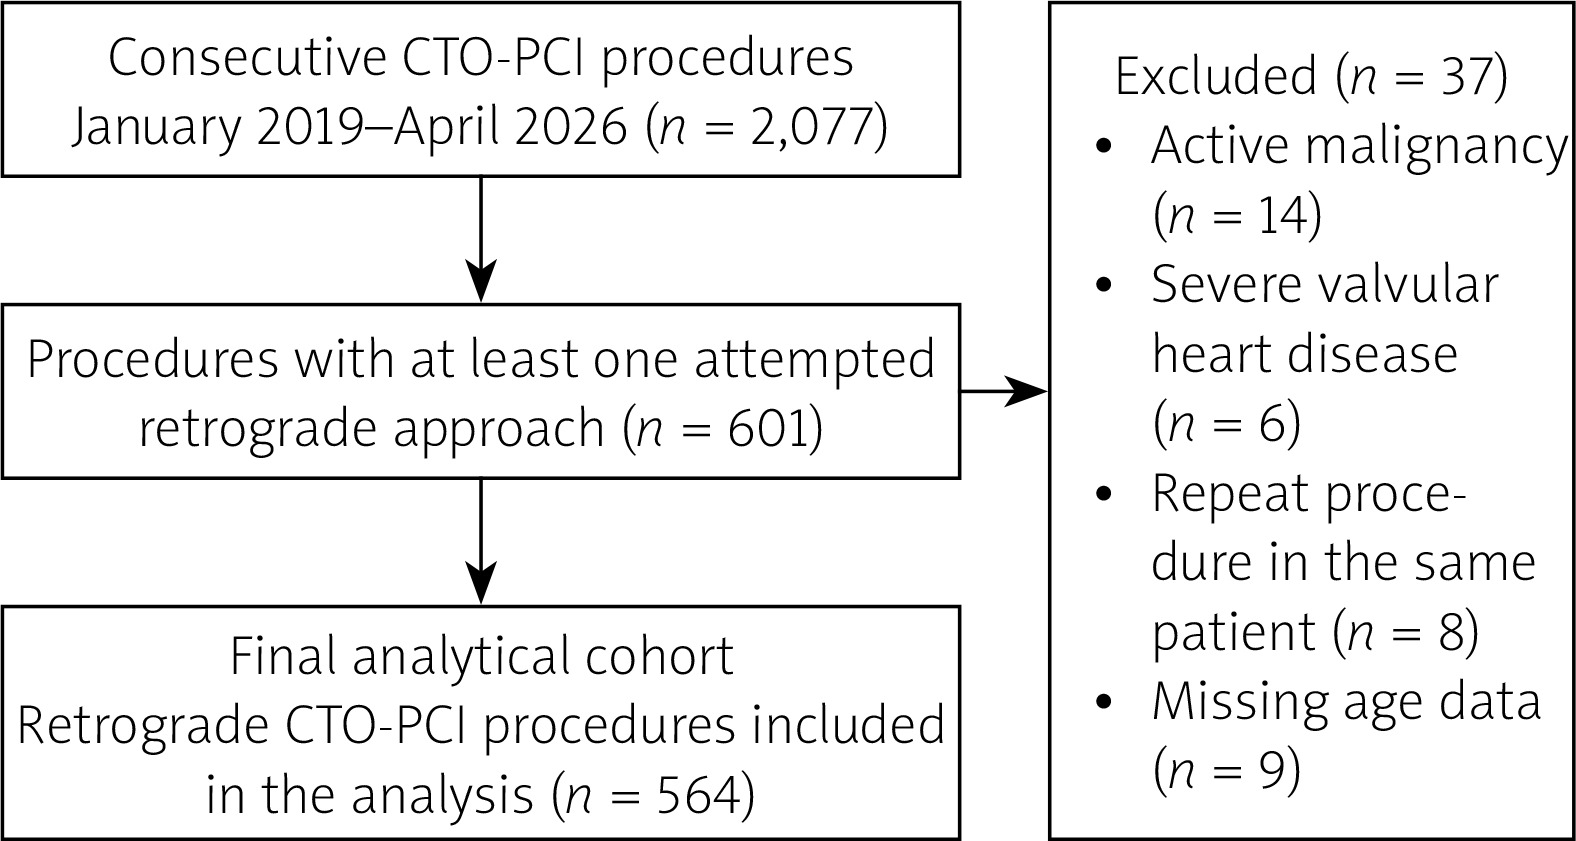
Data were collected through a dedicated online database (PROGRESS-CTO [Prospective Global Registry for the Study of Chronic Total Occlusion Intervention]; ClinicalTrials.gov identifier: NCT02061436). All data regarding CTO procedures were collected and managed using REDCap (Research Electronic Data Capture), hosted at the Minneapolis Heart Institute Foundation [9]. All centers obtained ethical approval for data collection, and secondary approval for data analysis was granted on 06/05/2026 by the local ethical committee with decision number 2026/295. The registry comprised 2,077 CTO-PCI procedures performed during the study period, including antegrade wiring, antegrade dissection and re-entry (ADR), and retrograde procedures. Because the objective of the present study was to evaluate retrograde CTO-PCI, only procedures in which a retrograde approach was attempted at least once were considered eligible (n = 601). Of these, 14 procedures in patients with active malignancy, 6 procedures in patients with severe valvular heart disease, 8 repeat procedures performed in the same patient, and 9 procedures with missing age data were excluded. After exclusion of the repeat procedures, each of the remaining 564 procedures represented a unique patient. Thus, the number of procedures was identical to the number of study patients. Consequently, 564 procedures constituted the final analytical cohort (Figure 1).
Figure 1
Study flow diagram
ADR – antegrade dissection and re-entry, CTO – chronic total occlusion, PCI – percutaneous coronary intervention.
Procedures were stratified using a 65-year age cut-off, as previous CTO studies have commonly defined procedures performed in patients aged ≥ 65 years as elderly [10, 11]. Furthermore, previous CTO studies have reported age-related differences in retrograde procedural outcomes, supporting the clinical relevance of this threshold [12]. In addition, age was analyzed as a continuous variable to assess its effect across the entire age spectrum. The retrograde CTO-PCI procedure was systematically analyzed across all procedural stages, including collateral assessment, collateral crossing, retrograde lesion crossing, and final crossing strategies.
Collateral complexity was assessed using the J-Channel Score [13], CC score [14], and Werner classification for each selected collateral channel [15]. Collateral channel morphology was assessed angiographically by the operating CTO interventional cardiologists at each participating center and recorded in the data collection system immediately after completion of CTO procedures. All collateral scores and classifications were calculated as shown in Supplementary Figure S1.
For collateral assessment, only collateral channels that were successfully crossed and reached the recipient vessel were included [12]. These channels were classified as septal, epicardial (ipsilateral or contralateral), or bypass graft (SVG or LIMA) collaterals. A total of 804 collateral channel crossing attempts were performed. Channel-crossing success was analyzed at both the procedure and collateral levels. Procedure-level analyses were based on whether at least one collateral channel was successfully crossed with a guidewire or microcatheter. Collateral-level analyses were performed separately for the first, second, and third collateral crossing attempts, with success rates calculated using the number of attempted collateral channels at each level as the denominator.
The initial crossing strategy was categorized as retrograde, antegrade wiring, or antegrade dissection and re-entry according to the first crossing approach selected by the operator. Subsequently, the final successful crossing strategy was recorded. Successful retrograde crossing, technical success, procedural success, in-hospital major adverse cardiac events (MACE), and procedural complications, including coronary perforation, tamponade, donor vessel injury, vascular access-site complications, pericardiocentesis, and stroke, were also documented. Procedural characteristics and outcomes were compared across age groups to assess the impact of older age on all stages of retrograde CTO-PCI.
Definitions
CTO was defined as a coronary segment demonstrating complete absence of antegrade flow (Thrombolysis in Myocardial Infarction [TIMI] grade 0) for an estimated or documented duration of ≥ 3 months [16]. Coronary blood flow was classified using the TIMI grading scale (grades 0–3) [17].
A CTO-PCI procedure was classified as “retrograde” if lesion crossing was attempted through a collateral channel or bypass conduit providing distal access to the occluded target vessel. Procedures performed without a retrograde crossing attempt were categorized as “antegrade-only”. “Antegrade dissection and re-entry (ADR)” referred to an antegrade crossing technique in which the guidewire was intentionally advanced into the subintimal space proximal to the occlusion, with subsequent efforts to re-enter the distal true lumen following intentional or unintentional subintimal tracking.
Retrograde crossing success was defined as successful CTO lesion crossing in a procedure in which the retrograde approach contributed to the final successful crossing strategy, following successful collateral traverse (e.g., CART and marker wire technique). A successful retrograde collateral traverse was defined as a guidewire passage through the collateral channel, successfully reaching the recipient vessel [12].
Technical success was considered achieved when the target CTO vessel and all distal branches ≥ 2.5 mm demonstrated final antegrade TIMI flow grade ≥ 2 with less than 30% residual stenosis at the completion of the procedure. Procedural success was defined as the achievement of technical success in the absence of any in-hospital MACE, defined as the composite of all-cause mortality, myocardial infarction (MI), urgent repeat revascularization with PCI or coronary artery bypass grafting (CABG), and cardiac tamponade requiring pericardiocentesis or surgery during the index hospitalization [16]. Stroke was recorded separately and was not included in the composite MACE endpoint.
Statistical analyses
Data were analyzed according to variable type and distribution. Normality was assessed using the Shapiro–Wilk test. Continuous variables were compared using Student’s t-test or the Mann–Whitney U test, as appropriate, and are presented as mean ± standard deviation or median [IQR], according to their distribution. Categorical variables are reported as frequencies and percentages and were compared using the χ2 test or Fisher’s exact test when required. For variables with missing observations, analyses were conducted using available data without imputation.
The primary endpoint was successful retrograde CTO lesion crossing. Secondary endpoints included technical success, procedural success, collateral guidewire crossing success, and collateral microcatheter crossing success. The primary endpoint was prespecified, whereas all secondary endpoint analyses were considered exploratory. No formal adjustment for multiple comparisons was performed for the exploratory secondary analyses; therefore, these findings should be interpreted as hypothesis-generating. For regression analyses evaluating retrograde crossing, successful retrograde CTO crossing was the dependent variable and was coded as 1 (success), whereas failed retrograde crossing was coded as 0. Univariate logistic regression analyses were initially conducted to identify predictors of successful retrograde crossing. Variables with p < 0.10 in the univariable analysis, together with clinically relevant variables, were subsequently entered into a multivariable logistic regression model. The final multivariable model included age ≥ 65 years, hypertension, target vessel location, CTO length, Werner CC0 morphology, and difficult collateral anatomy (J-channel score ≥ 3).
Effect estimates are presented as odds ratios with corresponding 95% confidence intervals. Because baseline characteristics differed between age groups, inverse probability of treatment weighting (IPTW) was performed as a sensitivity analysis. Propensity scores were derived from a logistic regression model including sex, hypertension, prior MI, previous CABG, baseline creatinine, J-CTO score, and left ventricular ejection fraction. Balance between groups was evaluated using standardized mean differences, with values below 0.10 considered acceptable.
Covariate balance before and after weighting was illustrated using a Love plot (Supplementary Figure S2). An IPTW-weighted multivariable logistic regression model was then constructed to confirm the robustness of the findings after adjustment for baseline differences. The IPTW model was constructed to balance baseline characteristics, with the J-CTO score representing CTO lesion complexity, whereas retrograde-specific anatomical variables were evaluated separately in the multivariable logistic regression model.
Age was also analyzed as a continuous variable using logistic regression to estimate the association between increasing age and the probability of successful retrograde CTO crossing. Restricted cubic spline analysis was performed to explore potential non-linear relationships between age and retrograde crossing outcomes. All statistical analyses were performed with R Statistical Software, version 4.5.2 (R Foundation for Statistical Computing, Vienna, Austria). All statistical tests were two-sided, and statistical significance was defined as p < 0.05.
Results
Procedural volume and success rates for each participating center are presented in Supplementary Table SI. No significant differences were observed among the four centers with respect to technical success (p = 0.527) or retrograde crossing success (p = 0.664).
Baseline clinical characteristics
Of the 564 retrograde CTO-PCI procedures, 363 (64.4%) were performed in patients aged < 65 years, whereas 201 (35.6%) were performed in patients aged ≥ 65 years.
Baseline demographic and clinical characteristics are summarized in Table I. Procedures performed in patients aged ≥ 65 years were more often female (14.9% vs. 7.2%, p = 0.003), had a higher prevalence of hypertension (82.1% vs. 74.4%, p = 0.042), previous CABG (28.9% vs. 12.4%, p < 0.001), higher serum creatinine levels (1.2 ±0.7 vs. 1.0 ±0.6 mg/dl, p = 0.003), lower e-GFR (74.2 ±21.2 vs. 89.6 ±18.9 ml/min/1.73 m², p < 0.001), and lower left ventricular ejection fraction (48.8 ±10.1% vs. 51.1 ±9.4%, p = 0.010).
Table I
Baseline demographic and clinical characteristics according to age group
| Variables | Pooled (n = 564) | Retrograde CTO-PCI | P-value* | |
|---|---|---|---|---|
| < 65 years (n = 363) | ≥ 65 years (n = 201) | |||
| Age [years] | 60.5 ±9.8 | 54.9 ±6.7 | 70.8 ±5.0 | < 0.001 |
| BMI [kg/m2] | 28.8 ±10.1 | 29.0 ±12.0 | 28.4 ±4.9 | 0.37 |
| Sex, n (%) | 0.003 | |||
| Male | 508 (90.1) | 337 (92.8) | 171 (85.1) | |
| Female | 56 (9.9) | 26 (7.2) | 30 (14.9) | |
| Diabetes mellitus, n (%) | 242 (42.9) | 149 (41.0) | 93 (46.3) | 0.23 |
| Hypertension, n (%) | 435 (77.1) | 270 (74.4) | 165 (82.1) | 0.042 |
| Family history, n (%) | 229 (40.6) | 158 (43.5) | 71 (35.3) | 0.06 |
| Previous PCI, n (%) | 339 (60.1) | 227 (62.5) | 112 (55.7) | 0.13 |
| Previous MI, n (%) | 196 (34.8) | 127 (35.0) | 69 (34.3) | 0.86 |
| MI territory of CTO† | 54 (27.6) | 34 (26.8) | 20 (29.0) | 0.72 |
| Previous CABG, n (%) | 103 (18.3) | 45 (12.4) | 58 (28.9) | < 0.001 |
| Previous CABG CTO area† | 92 (89.3) | 41 (91.1) | 51 (87.9) | 0.75 |
| Dyslipidemia, n (%) | 295 (52.3) | 189 (52.1) | 106 (52.7) | 0.87 |
| PAD, n (%) | 32 (5.7) | 19 (5.2) | 13 (6.5) | 0.52 |
| Prior neurological events, n (%) | 14 (2.5) | 8 (2.2) | 6 (3.0) | 0.55 |
| Creatinine [mg/dl] | 1.1 ±0.7 | 1.0 ±0.6 | 1.2 ±0.7 | 0.003 |
| e-GFR [ml/min/1.73 m²] | 84.2 ±21.0 | 89.6 ±18.9 | 74.2 ±21.2 | < 0.001 |
| LV EF, % | 50.3 ±9.7 | 51.1 ±9.4 | 48.8 ±10.1 | 0.010 |
| In-stent restenosis | 74 (13.1) | 52 (14.3) | 22 (10.9) | 0.26 |
| CAD presentation | 0.90 | |||
| Stable angina | 368 (65.2) | 244 (67.2) | 124 (61.7) | |
| Unstable angina | 7 (1.2) | 5 (1.4) | 2 (1.0) | |
| NSTEMI | 27 (4.8) | 16 (4.4) | 11 (5.5) | |
| Others‡ | 162 (28.7) | 98 (27.0) | 64 (31.8) | |
BMI – body mass index, CABG – coronary artery bypass grafting, CAD – coronary artery disease, CTO – chronic total occlusion, CTO-PCI – chronic total occlusion percutaneous coronary intervention, eGFR – estimated glomerular filtration rate, LV EF – left ventricular ejection fraction, MI – myocardial infarction, NSTEMI – non-ST-segment elevation myocardial infarction, PAD – peripheral artery disease, PCI – percutaneous coronary intervention, STEMI – ST-segment elevation myocardial infarction.
Angiographic and collateral channel characteristics
Angiographic characteristics are shown in Table II. Elderly patients had significantly greater lesion complexity, including a higher prevalence of moderate/severe calcification (58.7% vs. 43.3%, p < 0.001), higher J-CTO scores (3.3 ±1.0 vs. 3.0 ±1.0, p = 0.004), and a greater proportion of difficult collateral channels according to the J-channel score classification (38.8% vs. 30.3%, p = 0.020).
Table II
Angiographic features, lesion complexity, and collateral-channel characteristics of patients undergoing retrograde CTO-PCI, classified by age
| Variables | Pooled (n = 564) | Retrograde CTO-PCI | P-value* | |
|---|---|---|---|---|
| < 65 years (n = 363) | ≥ 65 years (n = 201) | |||
| CTO target vessel | 0.08 | |||
| Right coronary artery | 389 (69.0) | 258 (71.1) | 131 (65.2) | |
| Left anterior descending | 131 (23.2) | 82 (22.6) | 49 (24.4) | |
| Left circumflex | 41 (7.3) | 20 (5.5) | 21 (10.4) | |
| Side branch | 3 (0.5) | 3 (0.8) | 0 (0.0) | |
| Lesion characteristics | ||||
| Interventional collaterals | 451 (80.0) | 297 (81.8) | 154 (76.6) | 0.15 |
| Vessel diameter [mm] | 3.3 ±0.4 | 3.3 ±0.5 | 3.3 ±0.4 | 0.36 |
| Occlusion length [mm] | 35.2 ±14.1 | 35.1 ±14.2 | 35.4 ±13.9 | 0.99 |
| Proximal cap ambiguity | 364 (64.5) | 237 (65.3) | 127 (63.2) | 0.60 |
| Side branch at the proximal cap | 522 (92.6) | 332 (91.5) | 190 (94.5) | 0.18 |
| Blunt/no stump | 430 (76.2) | 278 (76.6) | 152 (75.6) | 0.84 |
| Moderate/severe calcification | 275 (48.8) | 157 (43.3) | 118 (58.7) | < 0.001 |
| Moderate/severe proximal tortuosity | 165 (29.3) | 100 (27.5) | 65 (32.3) | 0.24 |
| J-CTO score | 3.1 ±1.0 | 3.0 ±1.0 | 3.3 ±1.0 | 0.004 |
| PROGRESS-CTO score | 1.2 ±0.8 | 1.2 ±0.8 | 1.3 ±0.9 | 0.06 |
| Collateral channel complexity | ||||
| Werner classification | 0.92 | |||
| CC0 | 18 (3.2) | 11 (3.0) | 7 (3.5) | |
| CC1 | 427 (75.7) | 274 (75.5) | 153 (76.1) | |
| CC2 | 119 (21.1) | 78 (21.5) | 41 (20.4) | |
| J-Channel score category | 0.020 | |||
| Easy (0) | 54 (9.6) | 30 (8.3) | 24 (11.9) | |
| Intermediate (1–2) | 322 (57.1) | 223 (61.4) | 99 (49.3) | |
| Difficult (≥ 3) | 188 (33.3) | 110 (30.3) | 78 (38.8) | |
| CC score | 0.39 | |||
| Favorable collateral (≥ 2) | 213 (37.8) | 143 (39.4) | 70 (34.8) | |
| Unfavorable collateral (< 2) | 351 (62.2) | 220 (60.6) | 131 (65.2) | |
Collateral crossing success according to age
Collateral crossing outcomes are presented in Table III. At the procedure level, successful guidewire collateral crossing was achieved less frequently in elderly patients (70.6% vs. 80.2%, p = 0.010). Similarly, successful microcatheter collateral crossing was lower in procedures performed in patients aged ≥ 65 years (65.7% vs. 74.7%, p = 0.024).
Table III
Collateral channel crossing success according to age group
| Variable | Total | < 65 years | ≥ 65 years | P-value* |
|---|---|---|---|---|
| Procedure-level outcomes | ||||
| Any channel crossed with wire | 433 (76.8) | 291 (80.2) | 142 (70.6) | 0.010 |
| Any channel crossed with microcatheter | 403 (71.5) | 271 (74.7) | 132 (65.7) | 0.024 |
| Collateral level outcomes | ||||
| Collateral 1 wire success | 375/564 (66.5) | 248/363 (68.3) | 127/201 (63.2) | 0.22 |
| Collateral 1 microcatheter success | 352/564 (62.4) | 232/363 (63.9) | 120/201 (59.7) | 0.32 |
| Collateral 2 wire success | 48/151 (31.8) | 36/99 (36.4) | 12/52 (23.1) | 0.10 |
| Collateral 2 microcatheter success | 39/151 (25.8) | 30/99 (30.8) | 9/52 (17.3) | 0.08 |
| Collateral 3 wire success | 29/89 (32.6) | 23/56 (41.1) | 6/33 (18.2) | 0.026 |
| Collateral 3 microcatheter success | 21/89 (23.6) | 17/56 (30.4) | 4/33 (12.1) | 0.11 |
Data are presented as n (%). Procedure-level outcomes were calculated per procedure, whereas collateral-level outcomes were calculated per collateral crossing attempt. Percentages for collateral-level outcomes were calculated using the corresponding number of collateral crossing attempts as the denominator.
At the collateral level, first-channel guidewire and microcatheter crossing success rates were comparable between groups. However, age-related differences became more pronounced with subsequent collateral attempts. Third-channel guidewire crossing success was significantly lower among elderly patients (18.2% vs. 41.1%, p = 0.026), whereas third-channel microcatheter crossing showed a numerically lower success rate without reaching statistical significance (12.1% vs. 30.4%, p = 0.112).
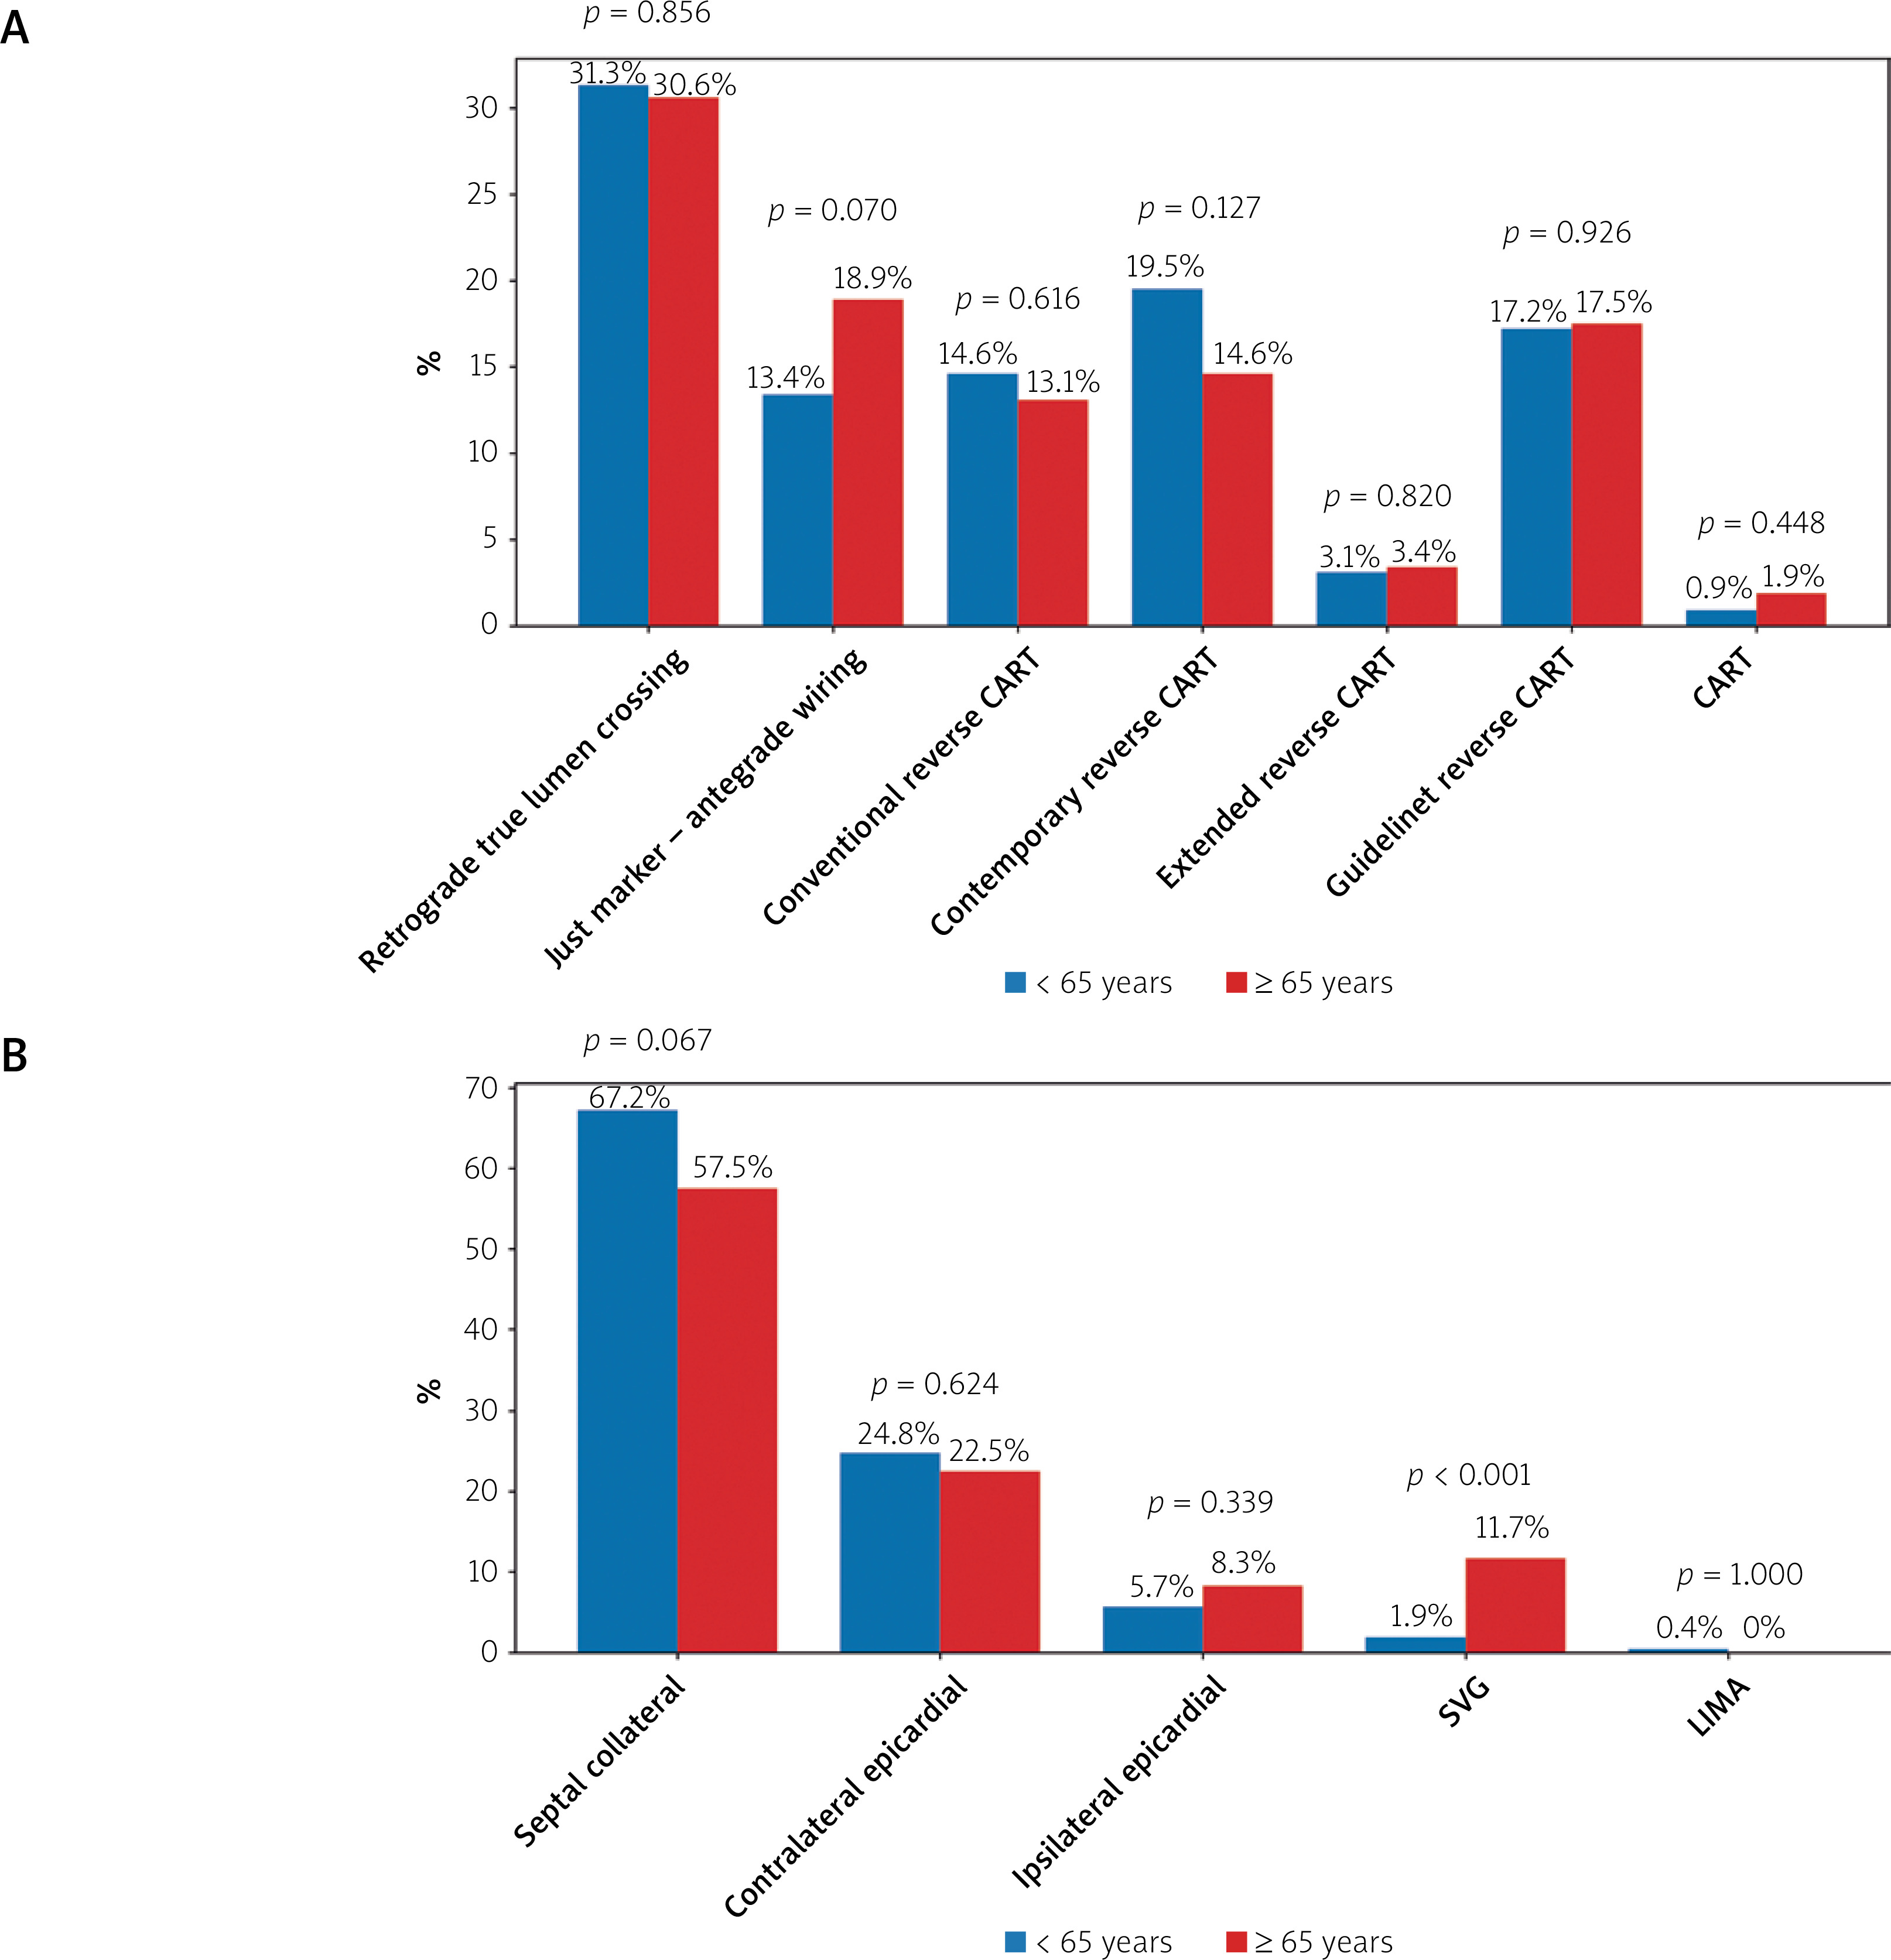
The distribution of successful retrograde crossing techniques was similar between age groups (p = 0.856) (Figure 2 A). Collateral utilization patterns differed according to age group, particularly with regard to bypass graft use. Saphenous vein graft collaterals were more frequently used among elderly patients, whereas septal and epicardial collateral utilization was similar between groups (Figure 2 B).
Figure 2
Retrograde crossing techniques and collateral utilization according to age group. A – Distribution of successful retrograde crossing techniques according to age group. B – Collateral utilization according to age group
CART – controlled antegrade and retrograde subintimal tracking, CTO – chronic total occlusion, LIMA – left internal mammary artery, SVG – saphenous vein graft.
Unadjusted procedural outcomes and complications
Unadjusted procedural characteristics, outcomes, and complications are summarized in Table IV. Initial crossing strategy selection did not differ between age groups (p = 0.898). However, the final successful crossing strategy differed significantly (p = 0.049), with procedures performed in patients aged ≥ 65 years more frequently requiring ADR techniques. Successful retrograde CTO crossing was significantly lower in procedures performed in patients aged ≥ 65 years (61.7% vs. 73.0%, p = 0.007). Likewise, technical success (74.6% vs. 83.7%, p = 0.009) and procedural success (73.1% vs. 82.1%, p = 0.013) were lower in elderly patients (Table IV and Supplementary Figure S3). Hospital stay was modestly longer among elderly patients (1.7 ±1.1 vs. 1.5 ±1.0 days, p = 0.002). Elderly patients also required a greater number of guidewires during the procedure (9.9 ±3.7 vs. 9.0 ±3.3, p = 0.009). In-hospital MACE rates were similar between groups, although vascular access-site complications were more frequent in elderly patients (4.5% vs. 1.7%, p = 0.046) (Table IV).
Table IV
Procedural characteristics, outcomes, and complications according to age group
| Variables | Pooled (n = 564) | Retrograde CTO-PCI | P-value* | |
|---|---|---|---|---|
| < 65 years (n = 363) | ≥ 65 years (n = 201) | |||
| First crossing strategy | 0.90 | |||
| Retrograde | 276 (48.9) | 177 (48.8) | 99 (49.3) | |
| Antegrade wiring | 283 (50.2) | 182 (50.1) | 101 (50.2) | |
| Antegrade dissection and re-entry | 5 (0.9) | 4 (1.1) | 1 (0.5) | |
| Successful crossing strategy† | 0.049 | |||
| Retrograde | 389 (77.6) | 265 (80.6) | 124 (72.1) | |
| Antegrade wiring | 57 (11.4) | 35 (10.6) | 22 (12.8) | |
| Antegrade dissection and re-entry | 55 (11.0) | 29 (8.8) | 26 (15.1) | |
| Procedural outcomes | ||||
| Successful retrograde crossing, n (%) | 389 (69.0) | 265 (73.0) | 124 (61.7) | 0.007 |
| Technical success, n (%) | 454 (80.5) | 304 (83.7) | 150 (74.6) | 0.009 |
| Procedural success, n (%) | 445 (78.9) | 298 (82.1) | 147 (73.1) | 0.013 |
| Fluoroscopy time [min] | 72 [57–93] | 71 [55–91] | 74 [60–97] | 0.06 |
| Procedure time [min] | 143 [117–178] | 142 [113–173] | 145.5 [123–180] | 0.09 |
| Contrast volume [ml] | 350 [250–500] | 350 [250–500] | 350 [250–500] | 0.84 |
| Air kerma radiation dose [Gy] | 5.7 [3.8–9.0] | 5.8 [3.9–9.0] | 5.6 [3.8–8.9] | 0.68 |
| Length of hospital stay [days] | 1.5 ±1.0 | 1.5 ±1.0 | 1.7 ±1.1 | 0.002 |
| Number of DES, n | 1.8 ±0.9 | 1.8 ±0.9 | 1.7 ±0.8 | 0.62 |
| Total length DES [mm] | 61.5 ±32.4 | 62.9 ±32.8 | 58.6 ±31.6 | 0.39 |
| Total number of balloons, n | 5.0 ±3.1 | 4.8 ±2.7 | 5.3 ±3.8 | 0.53 |
| Total number of guidewires, n | 9.3 ±3.5 | 9.0 ±3.3 | 9.9 ±3.7 | 0.009 |
| In-hospital MACE, n (%) | 32 (5.7) | 17 (4.7) | 15 (7.5) | 0.24 |
| Mortality, n (%) | 14 (2.5) | 7 (1.9) | 7 (3.5) | 0.26 |
| Acute myocardial infarction, n (%) | 2 (0.4) | 1 (0.3) | 1 (0.5) | 1.00 |
| Repeat PCI, n (%) | 1 (0.2) | 1 (0.3) | 0 (0.0) | 1.00 |
| Stroke, n (%) | 0 (0.0) | 0 (0.0) | 0 (0.0) | 1.00 |
| Emergency CABG, n (%) | 3 (0.5) | 1 (0.3) | 2 (1.0) | 0.29 |
| Vascular access site complications, n (%) | 15 (2.7) | 6 (1.7) | 9 (4.5) | 0.046 |
| Tamponade, n (%) | 13 (2.3) | 8 (2.2) | 5 (2.5) | 0.83 |
| Pericardiocentesis, n (%) | 12 (2.1) | 7 (1.9) | 5 (2.5) | 0.66 |
| All coronary perforation, n (%) | 60 (10.6) | 33 (9.1) | 27 (13.4) | 0.11 |
| Ellis ≥ 2 coronary perforation, n (%) | 53 (9.4) | 30 (8.3) | 23 (11.4) | 0.22 |
| Donor vessel injury, n (%) | 13 (2.3) | 9 (2.5) | 4 (2.0) | 1.00 |
To assess the robustness of the primary findings, sensitivity analyses were performed using alternative age thresholds of ≥ 70, ≥ 75, and ≥ 80 years. The numbers of patients aged ≥ 70, ≥ 75, and ≥ 80 years were 104, 43, and 13, respectively. Across these alternative age thresholds, older age remained consistently associated with lower retrograde crossing success. The association was statistically significant for the ≥ 75-year and ≥ 80-year thresholds, whereas the ≥ 70-year threshold demonstrated a similar direction of association that did not reach statistical significance (OR = 0.665; 95% CI: 0.428–1.034; p = 0.070) (Supplementary Table SII). Given the limited number of patients aged ≥ 80 years, these findings should be interpreted with caution.
Predictors of retrograde crossing success and final technical success
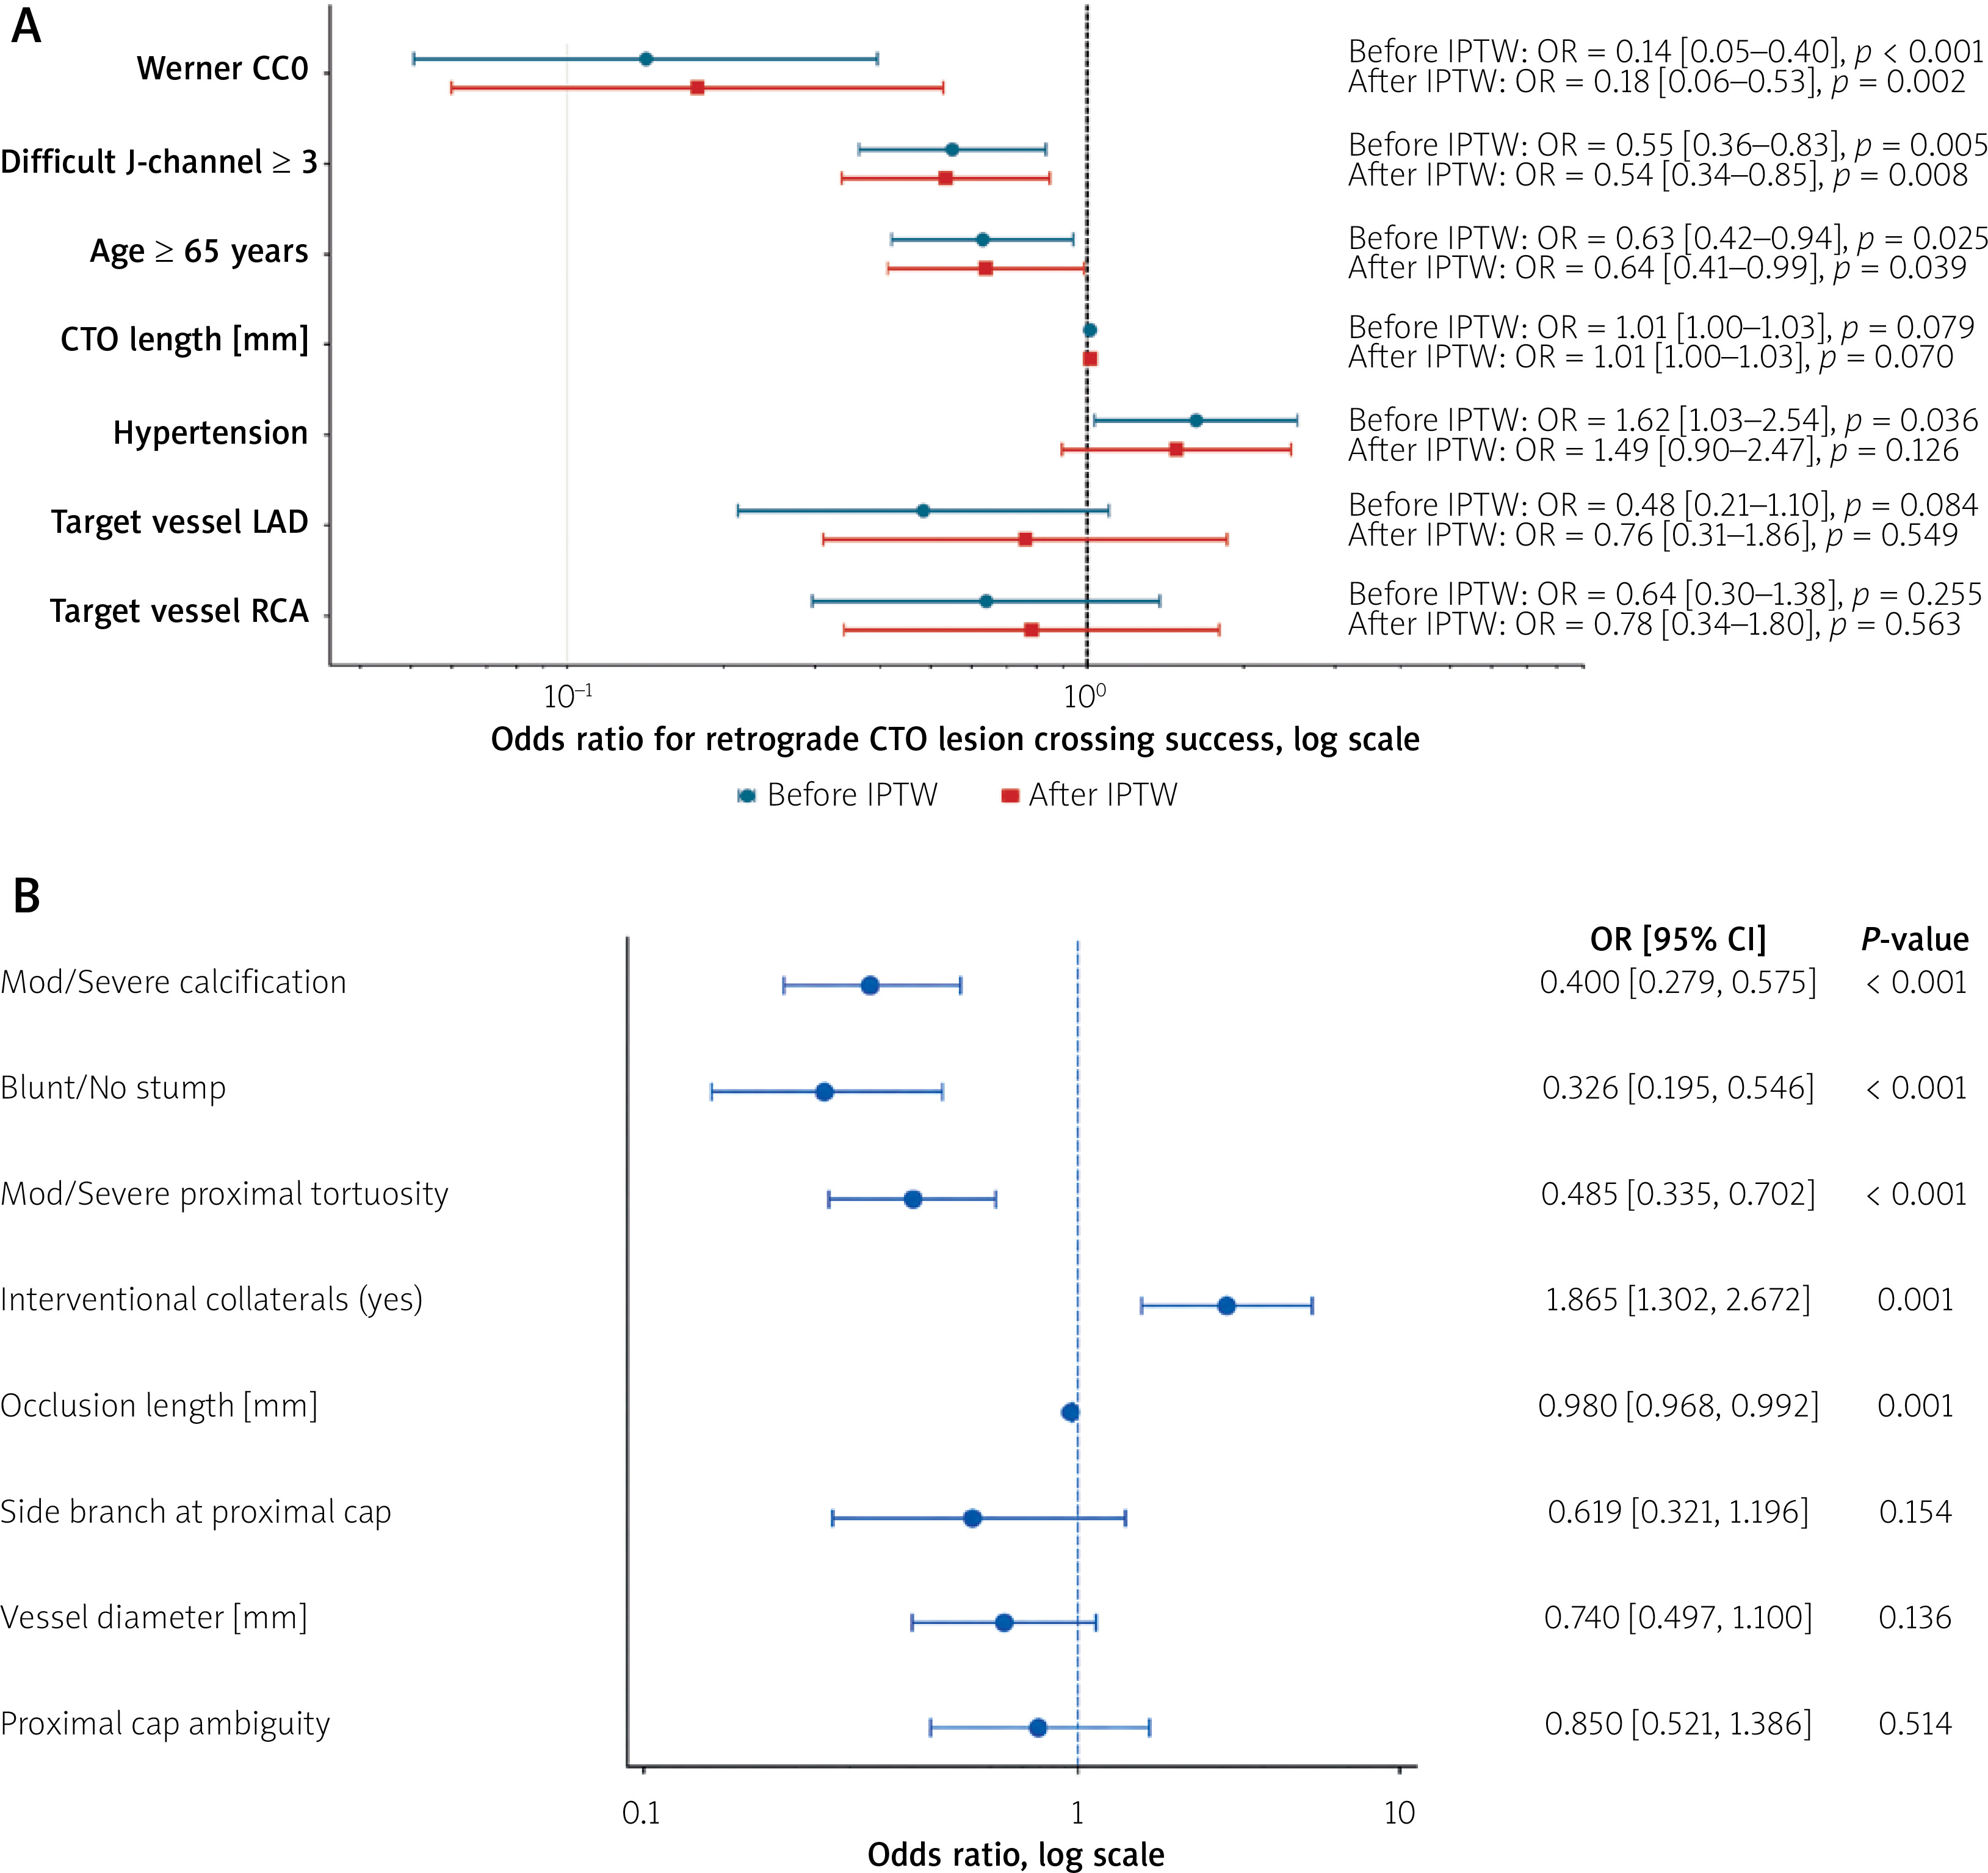
In univariable logistic regression analyses, Werner CC0 morphology (OR = 0.16, 95% CI: 0.06–0.46; p < 0.001), difficult J-channel anatomy (OR = 0.58, 95% CI: 0.40–0.85; p = 0.005), age ≥ 65 years (OR = 0.61, 95% CI: 0.42–0.89; p = 0.009), hypertension (OR = 1.52, 95% CI: 1.00–2.31; p = 0.052), target vessel LAD (OR = 0.59, 95% CI: 0.39–0.89; p = 0.012), increasing age as a continuous variable (OR = 0.97, 95% CI: 0.95–0.99; p = 0.001), and higher J-channel score (OR = 0.84, 95% CI: 0.71–1.00; p = 0.045) were identified as candidate variables for multivariable analysis (Table V). In the multivariable model, Werner CC0 remained the strongest independent predictor of reduced retrograde CTO crossing success before IPTW adjustment (OR = 0.14, 95% CI: 0.05–0.40; p < 0.001), followed by difficult J-channel anatomy (OR = 0.55, 95% CI: 0.36–0.83; p = 0.005) and age ≥ 65 years (OR = 0.63, 95% CI: 0.42–0.94; p = 0.025). Hypertension was independently associated with higher retrograde crossing success before IPTW adjustment (OR = 1.62, 95% CI: 1.03–2.54; p = 0.036), but this association was no longer statistically significant after IPTW adjustment (OR = 1.49, 95% CI: 0.90–2.47; p = 0.126). These associations remained significant after IPTW adjustment, with Werner CC0 morphology (OR = 0.18, 95% CI: 0.06–0.53; p = 0.002), difficult J-channel anatomy (OR = 0.54, 95% CI: 0.34–0.85; p = 0.008), and age ≥ 65 years (OR = 0.64, 95% CI: 0.41–0.99; p = 0.039) remaining independently associated with lower odds of successful retrograde crossing (Figure 3 A). In the multivariable analysis for technical success, moderate/severe calcification, blunt/no stump morphology, proximal tortuosity, interventional collaterals, and occlusion length were independent predictors, whereas age ≥ 65 years was not independently associated with technical success (Figure 3 B).
Table V
Univariable predictors of retrograde crossing success
Figure 3
A – Multivariable predictors of retrograde crossing success before and after IPTW. B – Multivariable predictors of final technical success. Odds ratios < 1 indicate lower technical success, whereas odds ratios > 1 indicate higher technical success
CI – confidence interval, CTO – chronic total occlusion, IPTW – inverse probability of treatment weighting, LAD – left anterior descending artery, OR – odds ratio, RCA – right coronary artery.
IPTW-adjusted and continuous age analyses
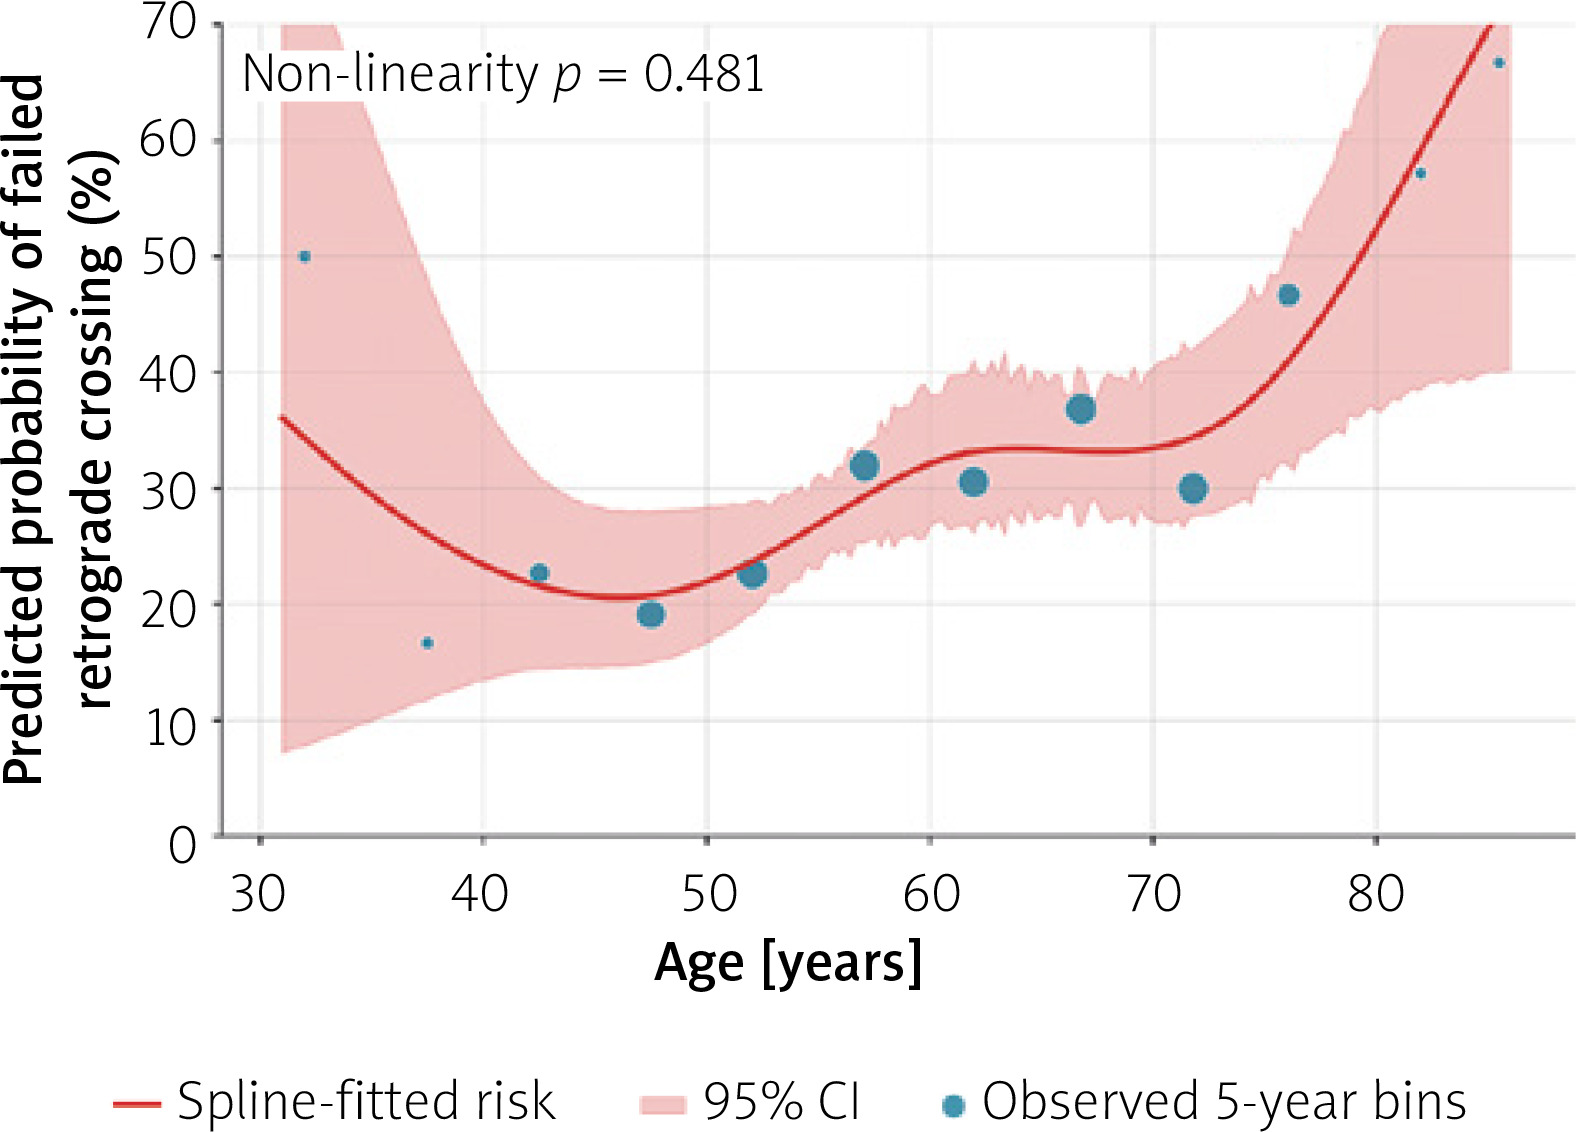
Age remained significantly associated with retrograde crossing outcomes when analyzed as a continuous variable (OR = 0.969; p = 0.001). Logistic regression analysis demonstrated a decrease in the likelihood of successful retrograde crossing with increasing age (Figure 4). Restricted cubic spline analysis did not demonstrate significant evidence of a nonlinear association (p for nonlinearity = 0.481). Although the curve visually suggested some fluctuation at the age extremes, the wide confidence intervals in these regions indicated substantial uncertainty (Figure 5).
Figure 4
Logistic trend analysis of retrograde crossing success according to age. The fitted logistic trend indicates a gradual decline in the probability of successful retrograde crossing with advancing age
CTO – chronic total occlusion, PCI – percutaneous coronary intervention.
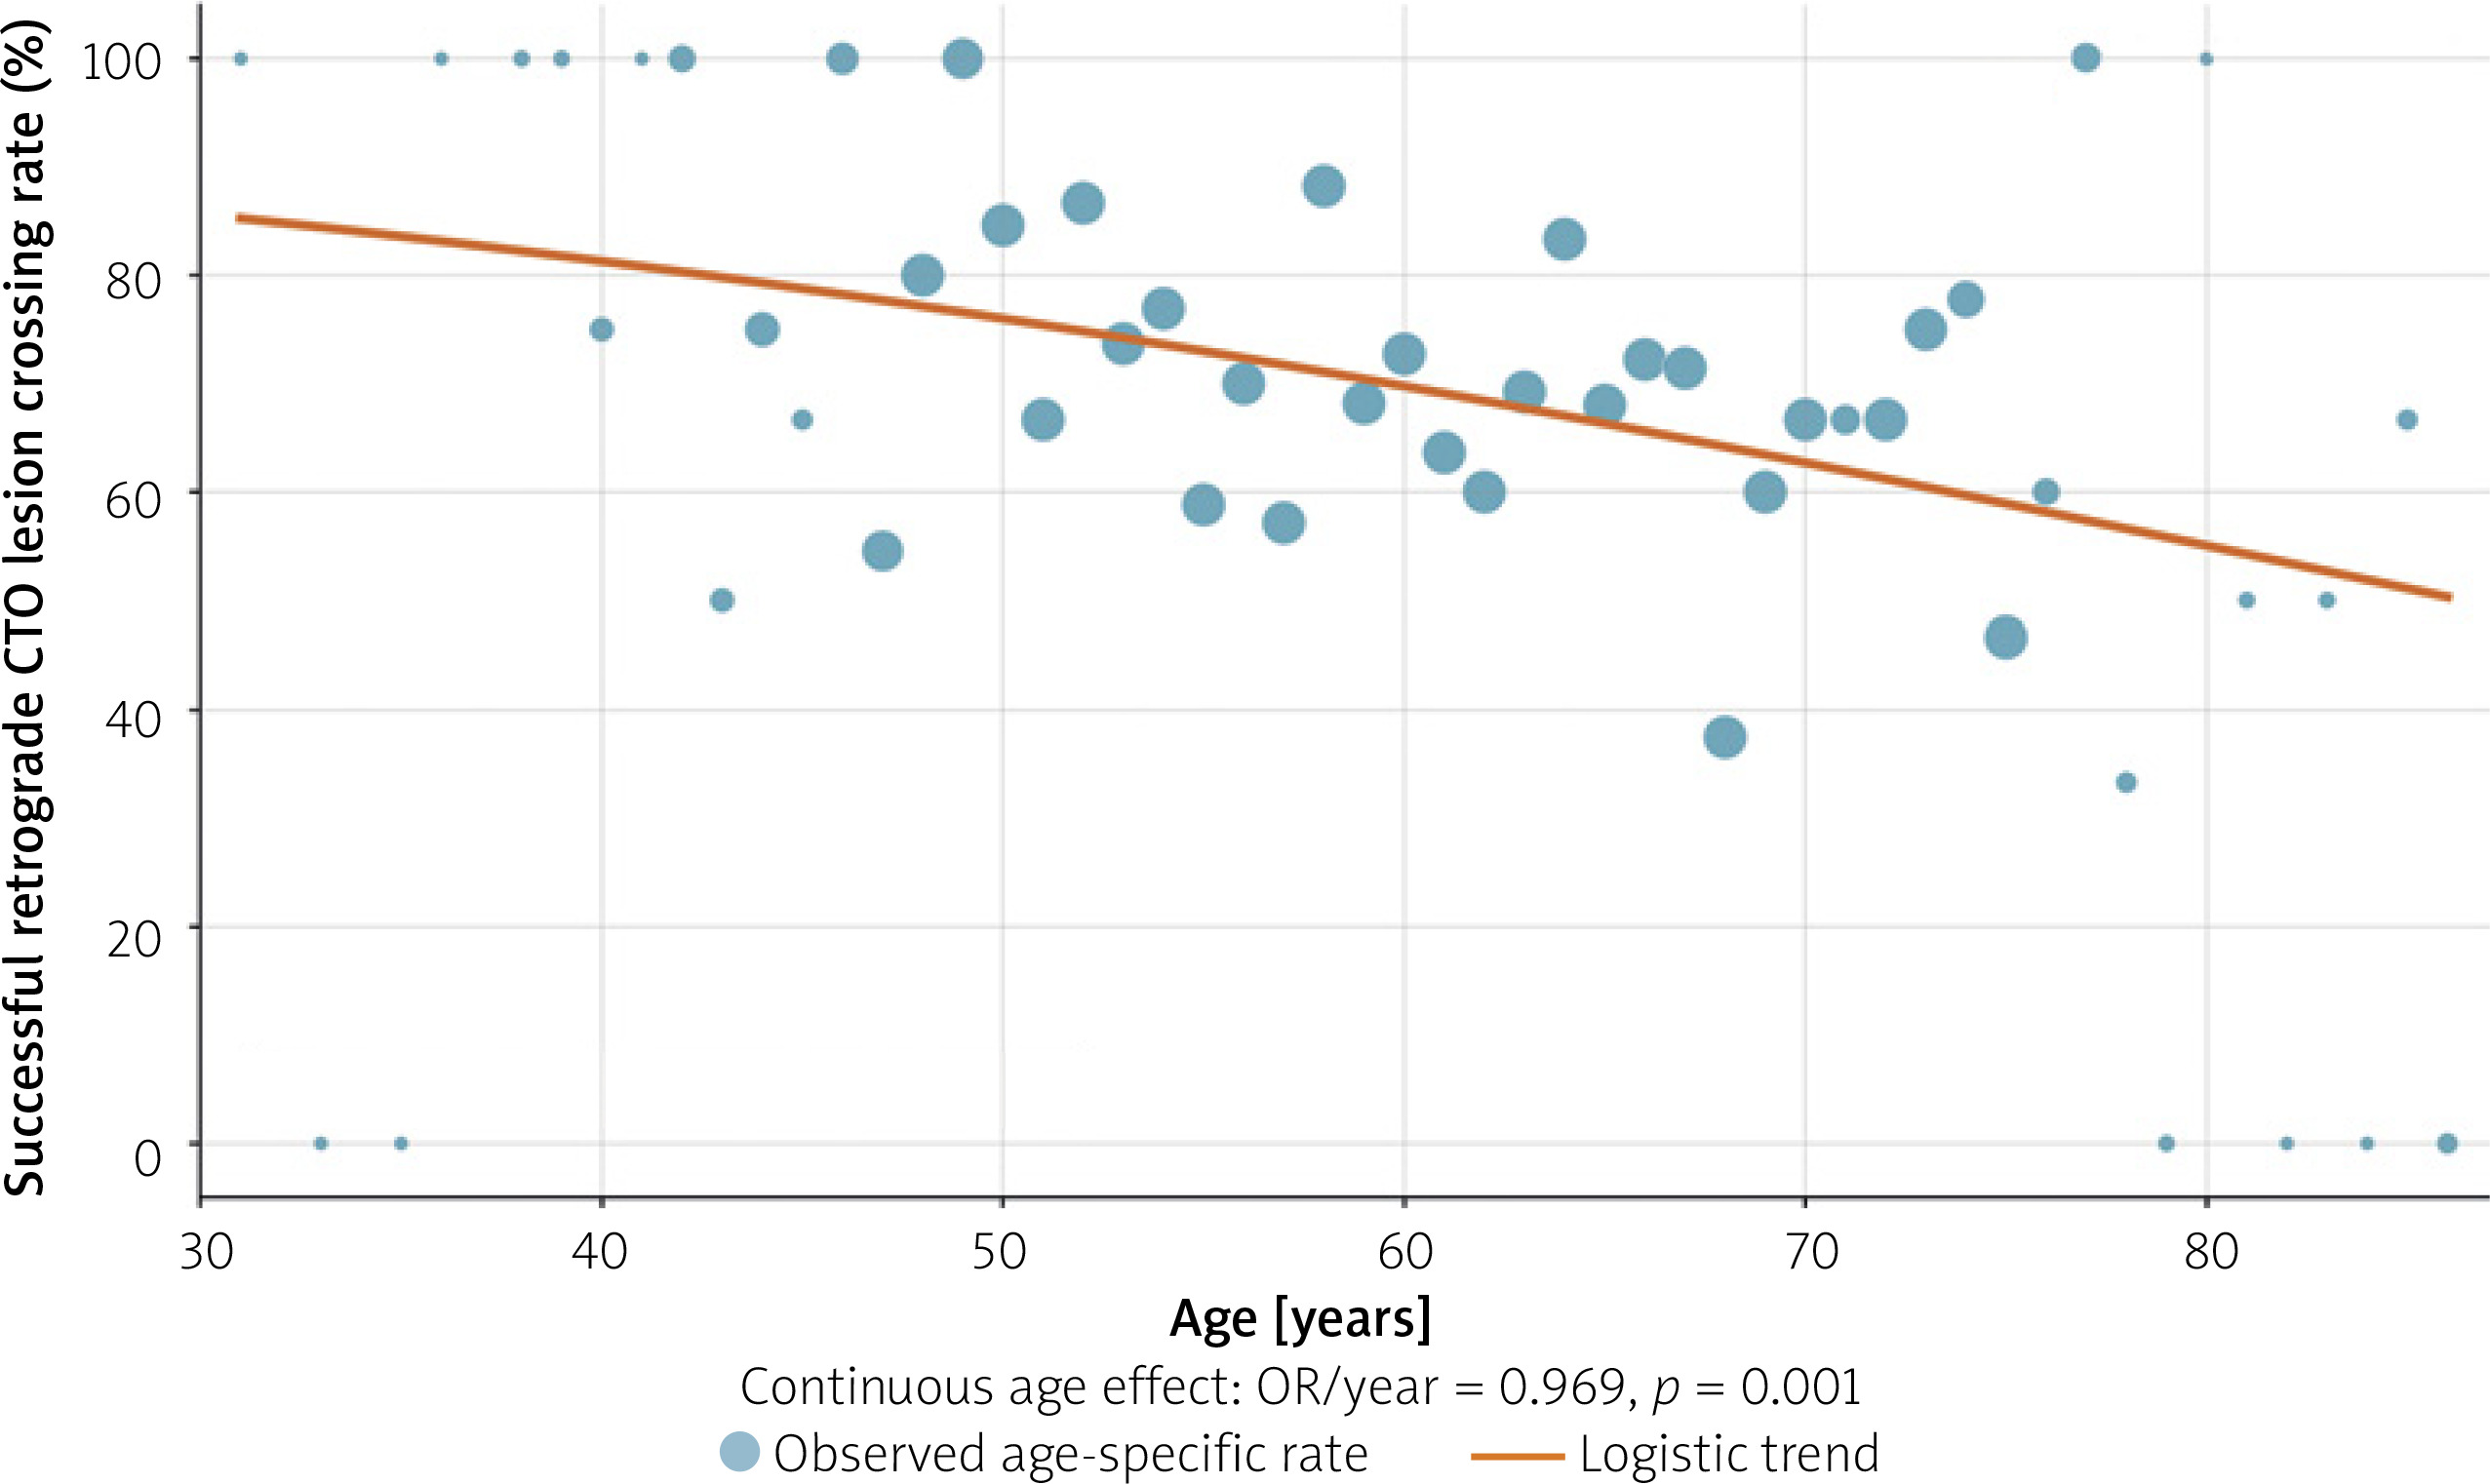
Figure 5
Restricted cubic spline analysis demonstrating the relationship between age and the predicted probability of failed retrograde chronic total occlusion (CTO) crossing. An upward trend of the spline indicates an increasing probability of retrograde crossing failure with advancing age. Shaded areas represent 95% confidence intervals (CI)
Discussion
The aim of the present study was to investigate the impact of age on the outcomes of retrograde CTO PCI. The main findings are that older age was associated with: i) more complex lesion and collateral channel anatomy; ii) lower collateral channel crossing success; iii) lower successful retrograde CTO crossing; and iv) lower technical and procedural success rates in the unadjusted analyses.
Association of older age with collateral channel anatomy and collateral crossing
In the present study, elderly patients had more complex collateral channel anatomy (higher J-Channel scores). Consistent with this finding, the success rates for wire crossing, microcatheter crossing, and overall collateral channel crossing were significantly lower in the elderly group. Although success rates during the first collateral crossing attempt were similar between groups, the difference became more pronounced during the second and especially the third attempts. This observation suggests that, following an unsuccessful initial attempt, alternative collateral options may be more limited in elderly patients, resulting in a more rapid decline in the likelihood of successful crossing.
The critical role of collateral channel morphology in retrograde CTO success was further confirmed in multivariable analyses. Werner CC0 morphology and complex J-Channel anatomy emerged among the strongest independent predictors of lower likelihood of successful retrograde crossing.
Association of older age with retrograde crossing and overall procedural success
In the present study, technical and procedural success rates among patients undergoing a retrograde approach were lower than those previously reported for CTO procedures performed exclusively using an antegrade strategy, consistent with earlier studies [5, 18, 19]. This observation may be attributable to the tendency for the retrograde strategy to be selected in cases involving greater anatomical complexity and higher procedural difficulty [20–22]. Indeed, the mean J-CTO score in our retrograde cohort was 3.1, indicating a high degree of lesion complexity. Moreover, procedures in patients aged ≥ 65 years exhibited significantly higher J-CTO scores compared with their younger counterparts and a greater prevalence of moderate-to-severe calcification than younger patients. Therefore, the lower rates of successful retrograde crossing, technical success, and procedural success observed in the elderly group in the unadjusted analyses may be partly attributable to the higher complexity of CTO lesions in this population.
However, the impact of age could not be explained solely by lesion complexity. In the present study, age ≥ 65 years remained independently associated with a lower likelihood of successful retrograde crossing in both the multivariable and IPTW-adjusted analyses.
Although older age emerged as an independent predictor of lower likelihood of successful retrograde crossing, this association did not extend to final technical success. In the multivariable analysis performed for technical success, moderate-to-severe calcification, blunt/no stump morphology, proximal tortuosity, and lesion length remained independent predictors, whereas age ≥ 65 years was no longer statistically significant (Figure 3 B). A dedicated adjusted model was not constructed for procedural success. These findings suggest that, in retrograde CTO-PCI, ultimate technical success may be driven more by lesion complexity than by age itself.
The absence of an independent association between older age and final technical success may be explained by the more frequent use of alternative crossing strategies. In our cohort, ADR techniques were employed more often in elderly patients. This observation suggests that experienced operators may be able to compensate for failed retrograde crossing by switching to alternative CTO strategies, thereby helping to preserve final technical success rates despite the lower likelihood of successful retrograde crossing in older patients.
Continuous effect of age
A notable aspect of the present study is that age was analyzed both as a categorical variable and as a continuous measure, providing complementary insights into its association with retrograde crossing success. When analyzed as a continuous variable, increasing age was associated with a gradual decline in the likelihood of successful retrograde crossing. Furthermore, the restricted cubic spline analysis did not demonstrate significant evidence of a nonlinear association. Although the curve visually suggested some fluctuation at the age extremes, the wide confidence intervals in these regions indicate substantial uncertainty, and these findings should therefore be interpreted with caution. These findings suggest that the relationship between age and retrograde CTO crossing success may not be fully captured by a predefined cutoff such as 65 years. Instead, age should be considered across a continuous spectrum. Accordingly, evaluating age as a continuous variable may provide additional information for procedural planning and risk assessment.
Safety and procedural complications
Although technical and procedural success rates were lower among elderly patients, there was no difference in the incidence of major procedural complications. Previous studies have reported an association between older age and a higher risk of complications and adverse events during CTO-PCI [7, 23]. In contrast, rates of coronary perforation, clinically significant perforation, cardiac tamponade, donor vessel injury, and pericardiocentesis were comparable between age groups in the present study. These findings indicate that no statistically significant differences were detected in most procedural complications between the age groups. Nevertheless, given the relatively low number of events, the study may have been underpowered to detect clinically meaningful differences in certain complications.
On the other hand, vascular access-site complications occurred more frequently in elderly patients. This finding may be attributable to several factors commonly observed in elderly patients, including age-related vascular fragility, the higher proportion of female patients, and elevated blood pressure levels, all of which may contribute to an increased susceptibility to access-site bleeding complications [24–27]. Accordingly, particular attention should be paid to access-site management and bleeding avoidance strategies when planning retrograde CTO-PCI in older individuals. Given the well-established association between transradial access and lower vascular complication rates [28–30], preferential use of radial access, whenever technically feasible, may represent a reasonable strategy to mitigate access-site complications in elderly patients.
Limitations
Our study has limitations. Because all procedures were performed at high-volume CTO centers, the findings may not be generalizable to institutions with less experience in complex CTO interventions. Collateral channel assessments were not adjudicated by an independent core laboratory. Furthermore, frailty was not systematically assessed and therefore could not be incorporated into the analyses, despite its potential influence on procedural complexity, treatment selection, and clinical outcomes in elderly patients. Operator-specific procedural volume data were not available in the registry and therefore could not be evaluated. In addition, no formal adjustment for multiple comparisons was applied to the exploratory secondary analyses. Accordingly, the results of these analyses should be interpreted with appropriate caution and considered hypothesis-generating. Finally, the lack of long-term follow-up data precluded evaluation of the impact of age-related differences in retrograde crossing success on subsequent clinical outcomes.
Conclusions
Older age is associated with more complex collateral anatomy, lower collateral channel crossing success, and lower retrograde crossing success. Although technical and procedural success rates were lower in the unadjusted analyses, older age remained independently associated only with a lower likelihood of successful retrograde crossing after IPTW adjustment. These findings suggest that age may represent an important determinant of retrograde crossing success and should be taken into account during procedural planning. Careful assessment of collateral channels, meticulous procedural planning, and early consideration of alternative crossing strategies may help optimize procedural outcomes in this population.










