Introduction
Patients with chronic coronary syndrome (CCS) represent a clinically stable but prognostically heterogeneous population of individuals with established or suspected coronary artery disease (CAD). Despite advances in prevention, diagnostics, and therapy, some patients experience acute coronary events, including myocardial infarction, unstable angina requiring hospitalization, urgent coronary revascularization, or cardiovascular death. As many as 15% of acute coronary events occur in individuals previously classified as clinically stable, underscoring the limitations of current risk stratification strategies [1].
CCS represents a heterogeneous population of patients with stable manifestations of CAD, including obstructive epicardial disease (up to 50% of patients), microvascular dysfunction (up to 25%), vasospastic disease, and other mechanisms contributing to myocardial ischemia [2–4]. Although guideline-based therapy aims to control symptoms and reduce long-term cardiovascular risk, patients’ individual risk of future acute events varies substantially according to demographics, socioeconomic status, comorbidities, and cardiac testing results [5].
The fundamental challenge in contemporary CCS assessment lies in the inability to reliably predict the transition from chronic, stable disease to cardiovascular event. Acute events often arise from non-obstructive plaques that cause no prior ischemia or symptoms [6]. Consequently, risk assessment strategies based solely on the degree of luminal stenosis or inducible ischemia fail to capture the complex processes underlying plaque vulnerability, vascular inflammation, and adverse coronary remodeling.
Non-invasive risk assessment may help identify high-risk CCS patients [7]. Advances in cardiac imaging, functional testing, and circulating biomarkers enable a more comprehensive evaluation of coronary atherosclerosis beyond luminal narrowing alone.
Aim of study and search strategy
The aim of this review is to summarize and critically appraise current non-invasive methods for risk assessment in patients with CCS, with particular emphasis on their ability to identify individuals at increased risk of future acute coronary events. In the available literature, this risk is frequently reported using composite endpoints such as major adverse cardiovascular events (MACE). Because definitions of MACE vary between studies, we considered studies relevant when the reported endpoint included acute coronary or clinically significant cardiovascular outcomes, such as myocardial infarction, unstable angina requiring hospitalization, urgent or unplanned coronary revascularization, cardiovascular death, or acute coronary syndrome (ACS). We conducted a structured literature search of the PubMed database to identify relevant peer-reviewed articles published between January 2014 and August 2025. The search strategy was constructed using three primary concept blocks covering: (i) CCS or stable coronary artery disease; (ii) prognosis, risk assessment, MACE, and acute cardiovascular outcomes; and (iii) specific non-invasive modalities, functional parameters, imaging-derived markers, or biomarker categories. The full search strategy is presented in Table I. The search was restricted to articles published in the English language. Articles were considered eligible if they evaluated non-invasive methods of risk assessment in patients with CCS, stable CAD, or comparable stable coronary populations, and if they reported prognostic outcomes relevant to future acute coronary events or MACE.
Table I
Search strategy
Pre-test probability and clinical likelihood models
Although originally developed to estimate the likelihood of obstructive CAD, non-invasive clinical models such as the 2019 ESC pre-test probability (PTP) model have also demonstrated utility in predicting MACE in patients with stable chest pain or suspected CCS. In patients with stable chest pain, the model stratifies the risk of MACE, with hazard ratios for MACE higher in high-risk (PTP > 15%) versus low-risk (< 5%) patients (HR = 4.23, 95% CI: 2.73–6.56) [8]. However, the PTP model shows limited ability to discriminate the risk of myocardial infarction and cardiovascular death between patients classified as low risk (< 5%) and those at intermediate risk (5–15%), as reported by investigators of the SCOT-HEART Trial [9]. The 2019 ESC PTP model has been refined by the introduction of the risk factor-weighted clinical likelihood (RF-CL) model, which incorporates additional risk factors and has demonstrated higher specificity and significant down-reclassification of patients with a low probability of CAD (< 15%) [10]. Furthermore, the RF-CL maintains good prognostic value for MACE at both clinical likelihood (CL) thresholds of 5% and 15% [9–11]. The down-reclassification of patients using RF-CL is not associated with increased myocardial infarction or mortality [9]. On the other hand, despite an overall good prognosis of low RF-CL patients, patients allocated to additional coronary CTA rather than functional testing had a lower risk of myocardial infarction or death [12].
The subsequent addition of coronary artery calcium score (CACS) acquired by non-contrast CT imaging led to the development of the CACS clinical likelihood model (CACS-CL), which further improves performance in stratifying the risk of CAD and enables additional down-reclassification of low-risk patients [10, 13]. Notably, the CACSCL model demonstrates superior prognostic value for nonfatal myocardial infarction and cardiovascular death, with significantly higher hazard ratios when comparing patients above versus below the 15% clinical likelihood cutoff [9, 13]. Furthermore, CACS-CL retains prognostic value even in patients with a CACS of zero, distinguishing between those with negligible and elevated risk of acute events [14]. Comparison of performance of risk stratification models is provided in Table II. Overall, recent studies suggest that PTP-related models may provide prognostic information for MACE in addition to the estimation of obstructive CAD probability, with the CACS-CL model emerging as the most robust model. However, the lack of direct head-to-head comparisons between PTP-derived models and established non-invasive testing strategies remains an important limitation. In addition, evidence of poorer outcomes among patients managed solely on the basis of RF-CL assessment, without additional non-invasive testing, may restrict the applicability of PTP-based models in routine clinical practice.
Table II
Comparison of hazard ratios for major adverse cardiac events across risk stratification models in patients with stable chest pain
Exercise electrocardiography (ExECG)
In patients with a low-to-intermediate pre-test likelihood of CAD (5–15%), ExECG may be considered to refine the pre-test likelihood estimate [7]. The ExECG-weighted clinical likelihood (ExECG-CL) model demonstrates sensitivity and AUC values comparable to those of the RF-CL model [15]. Additionally, the ExECG-CL model outperforms the RF-CL in reclassifying patients into lower clinical-likelihood categories. Importantly, follow-up data indicate that patients reclassified to lower-risk groups by the ExECG-CL model do not experience a higher incidence of MACE compared to those classified as low risk by the RF-CL model [15]. These findings suggest that ExECG-CL may be useful for identifying patients with a favorable prognosis, although its ability to predict future acute coronary events remains indirect and primarily dependent on its role in clinical likelihood refinement.
Coronary computed tomography angiography (CCTA)
Coronary computed tomography angiography (CCTA) is a high-resolution, non-invasive imaging modality that enables assessment of coronary stenosis, plaque presence, composition, morphology, and extent of coronary calcification. In addition to conventional luminal assessment, CCTA provides quantitative measurements, such as total plaque burden, total plaque volume, and low-attenuation plaque volume. Thus, the acquired quantitative and qualitative data help stratify the risk of MACE, including acute events, in patients with suspected CCS [16]. However, because CCTA-derived markers are interrelated and reflect overlapping aspects of coronary atherosclerosis, identifying a single superior risk stratification framework remains challenging.
Coronary artery calcium scoring (CACS)
Among CT-derived markers, CACS has emerged as an important tool for predicting cardiovascular diseases and serves as a robust risk stratification marker for MACE in both symptomatic and asymptomatic patients [17]. Non-contrast CT imaging enables quantification of coronary artery calcification, which reflects the burden of calcified atherosclerotic plaque within the coronary arteries. CACS is most commonly assessed using the Agatston method. In symptomatic patients with suspected CCS, higher Agatston scores are associated with a higher likelihood of MACE. One study indicated a positive correlation between higher CACS values and the risk of future cardiovascular events, with the most pronounced risk observed in individuals with a CACS > 400 [18]. Similarly, among patients with stable chest pain referred for invasive coronary angiography, a CACS of 0 was associated with a very low risk of MACE [19]. Supplementary data derived from CACS, particularly CAC density, may further refine individual cardiovascular risk assessment [20]. Higher calcium density appears to be inversely associated with plaque vulnerability and cardiovascular event rate after adjustment for clinical risk factors and calcium volume [21]. CACS may also support therapeutic decision-making, including the initiation or modification of antiplatelet and lipid-lowering therapies, which benefits primary prevention and lowers long-term mortality [22]. However, the absence of coronary calcification does not exclude clinically relevant CAD. In symptomatic patients younger than 60 years with CACS of 0, the presence of significant luminal stenosis was associated with increased risk of myocardial infarction and all-cause mortality [23]. This finding is particularly relevant to acute event prediction, as non-calcified plaques, which are not captured by CACS, may still be associated with plaque vulnerability and future ACS.
In conclusion, CACS provides robust and graded risk assessment of MACE and mortality risk in patients with suspected or established CCS. Its prognostic value is further enhanced by incorporating calcium density. Nevertheless, limitations include the inability to detect non-calcified high-risk plaques, the lack of dynamic functional assessment, and the possibility of adverse outcomes in younger patients with CACS of 0 and obstructive CAD.
Qualitative plaque analysis
In addition to the assessment of calcium burden, qualitative CCTA-based evaluation of plaque composition and morphology provides complementary prognostic information. This approach helps identify high-risk plaque features, commonly referred to as high-risk plaques (HRP), which are associated with plaque vulnerability and an increased risk of cardiovascular events [24]. The main CCTA features associated with HRP include low attenuation plaque, positive remodeling, spotty calcification and the napkin ring sign [24]. A brief description of HRP features that can be identified and characterized by CCTA is provided in Table III. Low attenuation plaque is thought to correlate with the presence of lipid-rich necrotic cores in rupture-prone atherosclerotic plaques [24, 25]. Significantly, patients with stable chest pain and low-attenuation plaque burden greater than 4% face nearly a fivefold higher likelihood of a fatal or nonfatal myocardial infarction, independently of luminal stenosis severity, cardiovascular risk factors, and CACS [26]. Moreover, low-attenuation plaques and the napkin ring sign have demonstrated stronger adjusted ability to predict MACE than other HRP features. The prognostic value of qualitative high-risk plaque features is summarized in Table IV [27].
Table III
Definitions of high-risk plaque features
Quantitative plaque analysis
CCTA also enables quantitative assessment of coronary atherosclerotic burden, which provides additional prognostic information and may help predict long-term outcomes [28]. Quantitative plaque analysis allows measurement of multiple parameters, including total plaque volume, low attenuation plaque volume, calcified plaque volume, and noncalcified plaque volume. A brief description of these metrics is provided in Table V. Notably, all of the above parameters positively correlate with MACE, with total plaque volume and low attenuation plaque volume demonstrating the strongest associations [29]. Additionally, the plaque burden parameter normalized to the vessel volume and reported as percent atheroma volume demonstrates superior prognostic accuracy for future mortality and non-fatal MI compared with CACS [30]. These findings suggest that quantitative CCTA plaque analysis may improve risk stratification beyond calcium scoring alone by capturing both total atherosclerotic burden and non-calcified, potentially vulnerable plaque components.
Table V
CMR modifications characteristics
Epicardial adipose tissue (EAT) and pericoronary adipose tissue (PCAT)
CCTA enables assessment not only of luminal stenosis and plaque-related risk markers, but also of extravascular imaging biomarkers, particularly epicardial adipose tissue (EAT) and pericoronary adipose tissue (PCAT). EAT is a distinct visceral fat depot located between the myocardium and the visceral layer of the pericardium. Rather than serving only as an energy reservoir, EAT is a metabolically, hormonally, and immunologically active tissue that may influence the adjacent myocardium and coronary arteries through several mechanisms, including pro-inflammatory and profibrotic signaling, neuromodulation, gene regulation, and effects on glucose and lipid metabolism [31]. Given its close anatomical relationship with the coronary arteries and its substantial biological activity, EAT has been linked to a role in the development of CAD. Accordingly, EAT has emerged as a potential imaging biomarker of CAD, cardiovascular events, and mortality [32]. Notably, EAT accumulation is associated with progression of coronary atherosclerotic plaques toward more vulnerable HRP phenotypes [32]. Moreover, EAT volume has been shown to be associated with all-cause mortality and myocardial infarction independently of other cardiovascular risk factors. In one study, patients with an EAT volume greater than 169.9 cm3 had an approximately twofold higher risk of fatal and nonfatal myocardial infarction and fivefold higher risk of all-cause mortality [33].
PCAT represents a subtype of EAT located around the coronary artery wall. Similarly to EAT, the PCAT is not only a structural support of coronary vessels, but also a metabolically and hormonally active tissue [34]. Under physiological conditions, PCAT may exert protective vascular effects. However, disruption of this homeostatic function may promote a shift toward a pro-inflammatory secretory profile, contributing to vascular dysfunction [35, 36]. Therefore, PCAT inflammation and dysfunction have been implicated in the progression of coronary atherosclerosis and development of cardiovascular diseases [37, 38].
The degree of PCAT inflammation can be assessed using the pericoronary fat attenuation index (FAI), which quantifies the attenuation of adipose tissue. FAI may be measured around the right coronary artery (RCA), left circumflex artery (LCX), or left anterior descending artery (LAD) [39]. Increased RCA pericoronary adipose tissue attenuation has been shown to predict myocardial infarction, independently of established cardiovascular risk factors and conventional CCTA interpretation [40]. Patients with elevated RCA pericoronary adipose tissue attenuation experienced an approximately sixfold higher risk of cardiac mortality and an almost fourfold higher risk of all-cause mortality. Recent meta-analyses have further supported RCA-FAI as an independent risk marker of MACE [41]. In addition, elevated RCA-FAI has been associated with lipid-rich HRP features and greater stenosis severity [42, 43]. In contrast, the prognostic value of LCX-derived PCAT attenuation has not shown a consistent association with increased MACE risk [41].
Overall, EAT and PCAT represent promising imaging biomarkers incorporating vascular inflammatory risk into the prediction of MACE, including myocardial infarction and mortality. Nevertheless, further studies are required to validate and establish PCAT-derived biomarkers across different clinical likelihood categories, scanner vendors, acquisition protocols, and patient populations before their routine implementation in clinical practice.
Fractional flow reserve derived from CCTA (FFRCT)
Besides the intravascular and extravascular factors, CCTA allows clinicians to evaluate the physiological aspects of coronary blood flow limitation associated with CAD. CT-derived fractional flow reserve (FFRCT) is a physiologic simulation technique that uses standard CCTA imaging data to model coronary blood flow, pressure, and resistance. A patient-specific three-dimensional coronary artery model is generated based on patient-specific inflow and outflow hemodynamic conditions [44]. The addition of FFRCT is important in the diagnostic assessment of CAD, since it evaluates lesion-specific ischemia. FFRCT is particularly useful in stable symptomatic patients with a low-to-intermediate clinical likelihood of obstructive CAD, especially those with moderate coronary stenosis, and may guide clinical decision-making regarding subsequent invasive coronary angiography and revascularization [7, 45].
In addition to its diagnostic role, FFRCT has emerged as a prognostic tool for MACE risk stratification in patients with suspected or stable CCS [46–48]. First, it was shown that FFRCT ≤ 0.80 serves as an independent predictor of MACE in patients with single vessel stenosis ≥ 50% [46]. Similarly, another study reported a higher incidence of MACE in patients with FFRCT ≤ 0.71 than in those with FFRCT > 0.71 [48]. In a meta-analysis including 5460 patients with suspected CCS, patients with FFRCT ≤ 0.80 experienced MACE, myocardial infarction and unplanned revascularization more often than patients with FFRCT > 0.80 [47]. Moreover, each 0.10-unit reduction of FFRCT was associated with greater risk of cardiovascular death or myocardial infarction. FFRCT also appears to provide prognostic value for clinical outcomes comparable to that of invasive FFR and may improve long-term risk stratification [49].
The FFRCT model may be further improved by incorporating the FFRCT gradient, which evaluates the pressure drop between proximal and distal points of a stenosis within a selected coronary vessel. In this manner, FFRCT gradient may enhance risk stratification of future coronary events in patients with multivessel CAD [50]. Furthermore, multiparameter risk models incorporating patient comorbidities, coronary stenosis severity, quantitative and qualitative plaque characterization, and FFRCT demonstrate superior predictive performance for MACE than any individual risk factor alone [51].
Some recent studies suggest that, among patients with stable CAD and intermediate stenosis, FFRCT testing instead of point-of-care invasive coronary angiography does not reduce MACE, despite reducing revascularization within 90 days [52]. Similarly, another study found no significant difference in the incidence of MACE, nonfatal MI, or all-cause mortality over 1 year among patients undergoing FFRCT compared with those undergoing other non-invasive testing strategies, including PTP assessment, exercise electrocardiography, perfusion imaging, or stress cardiovascular magnetic resonance [53].
In summary, FFRCT is an important non-invasive functional marker that improves diagnostic assessment and provides independent prognostic information in patients with suspected or stable CAD. Its value for predicting MACE appears strongest when integrated into multiparametric CCTA-based models that combine anatomical, plaque-related, functional, and clinical data. Nevertheless, whether FFRCT-guided management reduces MACE compared with other non-invasive diagnostic strategies remains uncertain and requires further investigation.
Cardiac magnetic resonance (CMR)
Cardiac magnetic resonance (CMR) is a non-invasive and non-ionizing imaging modality that provides information on cardiac anatomy ventricular function, myocardial perfusion, viability, and tissue characterization [54]. CMR implements additional functional modifications such as vasodilator stress CMR [55], inotropic stress CMR, late gadolinium enhancement (LGE) [56], and T1 pre- and post-contrast mapping [56, 57]. A short overview of these modifications can be found in Table V. Stress CMR provides information on inducible myocardial ischemia. A study of 2,210 patients referred for stress CMR after positive CCTA diagnosis of CAD found that inducible ischemia and LGE are significantly associated with MACE and cardiac mortality [58]. Similarly, a meta-analysis including 74,470 patients from 64 studies identified stress CMR and LGE as independent risk factors of MACE [59]. Stress-inducible ischemia and LGE were both associated with approximately twofold higher all-cause mortality, sixfold higher cardiovascular mortality, and fivefold higher likelihood of MACE.
Stress CMR can also provide information on myocardial perfusion reserve index (MPRI), which evaluates the ability of coronary vessels to increase blood flow in response to stress. A study of 218 patients with coronary microvascular disease identified an optimal MPRI cutoff of ≤ 1.47 for predicting MACE. Patients with MPRI ≤ 1.47 had a threefold increased risk of MACE compared to those with MPRI > 1.47 [60].
In summary, stress CMR myocardial perfusion imaging has demonstrated strong prognostic value for MACE and mortality in patients with known or suspected CCS. Inducible ischemia and LGE are independently associated with increased risk of MACE. Importantly, stress CMR provides incremental prognostic information beyond anatomical CCTA findings, although randomized comparisons with other non-invasive modalities such as FFRCT or stress perfusion imaging are still limited. A comprehensive summary of all modalities, techniques, and their association with MACE and mortality in CCS patients can be found in Table VI.
Table VI
CCTA and CMR modalities and their association with cardiovascular risk and MACE
| Study | Conclusion | Measurement | 95% CI | Reference |
|---|---|---|---|---|
| Lo-Kioeng-Shioe et al. | Risk of future cardiovascular events was significantly higher in patients with CAC score greater than 400. | HR = 4.88 | 2.44–9.76 | [18] |
| Williams et al. | Patients with stable chest pain and low-attenuation plaque burden (> 4%) had a higher likelihood of a fatal or nonfatal myocardial infarction independently of other cardiovascular factors . | HR = 4.65 | 2.06–10.5 | [26] |
| Bell et al. | Risk of MACE was strongly associated with TPV and LAPV. | adjHR = 3.93 adjHR = 2.81 | 2.10–7.34 (I
2 = 62%) 2.01–3.93 (I 2 = 0%) | [29] |
| West et al. | Patients with EAT volume of more than 169.9 cm3 had twofold higher risk for fatal and nonfatal MI and fivefold higher all-cause mortality risk. | adjHR = 1.93 adjHR = 5.02 | 1.31–4.01 2.93–9.34 | [33] |
| Oikonomou et al. | Patients with elevated RCA-PCATA (above –70.1 HU) had roughly sixfold higher risk of cardiac mortality and almost fourfold higher risk of all-cause mortality. | adjHR = 5.62 adjHR = 3.69 | 2.90–10.88 2.26–6.02 | [40] |
| Jin et al. | FFRCT ≤ 0.80 was independently associated with MACE in patients with single vessel stenosis (≥ 50%). | adjOR = 1.63 | 1.1–2.43 | [46] |
| Wada et al. | Each 0.10-unit reduction of FFRCT was associated with greater risk of acute myocardial death or MI. | RR = 1.67 | 1.47–1.87 | [48] |
| Pezel et al. | In patients referred for stress CMR after positive CCTA CAD diagnosis, inducible ischemia and LGE were significantly associated with MACE and cardiac mortality. | HR = 4.51 HR = 3.32 | 3.55–5.74 2.55–4.32 | [58] |
| Zhou et al. | Patients with MPRI ≤ 1.47 had a threefold increased risk of MACE compared to those with MPRI > 1.47. | HR = 3.14 | 1.58–6.25 | [60] |
[i] adjHR – adjusted hazard ratio, adjOR – adjusted odds ratio, CAC – coronary artery calcium, CAD – coronary artery disease, CCTA – coronary computed tomography angiography, CMR – cardiovascular magnetic resonance, EAT – epicardial adipose tissue, FFRCT – fractional flow reserve derived from computed tomography, HR – hazard ratio, I² – I-squared statistic, LAPV – low-attenuation plaque volume, LGE – late gadolinium enhancement, MACE – major adverse cardiovascular events, MPRI – myocardial perfusion reserve index, MI – myocardial infarction, OR – odds ratio, PCATA – pericoronary adipose tissue attenuation, RCA – right coronary artery, RR – risk ratio, TPV – total plaque volume.
Positron emission tomography (PET) and single-photon emission computed tomography (SPECT) imaging
Positron emission tomography (PET) and single-photon emission computed tomography (SPECT) are non-invasive nuclear imaging modalities used for functional assessment of myocardial perfusion and ischemia. PET offers higher image resolution, shorter acquisition times, and better prognostic value than SPECT [61]. Despite these advantages, the comparison of PET and SPECT showed no significant difference in downstream management and diagnostic failure defined as unnecessary angiography or additional non-invasive testing within 60 days after the first myocardial perfusion imaging (MPI) [62]. The strength of PET lies in its flow-based parameters, which may serve as predictors of cardiac events. Quantification of myocardial flow reserve (MFR) significantly enhances prognostic performance of PET by helping identify patients at increased risk of cardiac events and by reclassifying patients with preserved flow reserve into lower-risk groups [63]. Furthermore, PET MPI enables early diagnosis of ischemia with non-obstructive arteries (INOCA). INOCA is very common in patients with coronary disease and was present in 13% of patients with moderate or severe ischemia enrolled in the ISCHEMIA trial [64]. INOCA is associated with an elevated risk of MACE and PET-derived MFR is an important discriminator of patients at highest risk of cardiac events [65].
In addition to perfusion imaging, 18F-fluoride PET can also serve as a tool for atherosclerotic plaque evaluation. Increased 18F-fluoride uptake is associated with a more rapid progression of coronary calcification in patients with CCS [66]. This provides an opportunity for non-invasive identification of plaques likely to induce ACS in the future. Nonetheless, due to PET’s high costs and limited availability, it is mainly used in academic centers.
The main well-known limitation of SPECT is underestimation of the extent of ischemia in patients with balanced multi-vessel CAD or microcirculatory disorders because of relative rather than absolute perfusion assessment [67]. However, its wide availability and lower cost make SPECT more useful in everyday practice than PET. Using a high-sensitivity dedicated cardiac cadmium-zinc-telluride (CZT) SPECT camera enables the calculation of the total myocardial blood flow and MFR and avoids the underestimation of the level of ischemia in patients with balanced CAD [68]. The WATERDAY study proved that dynamic 99mTc SPECT provides similar global and regional MFR compared to 15O-water PET [69]. The limitation of SPECT MFR quantification is that the segmental count statistics are insufficient to analyze per-segment MFR in the 17-segment model [69]. The advantages of CZT-SPECT cameras are faster image acquisition and lower radiation doses than conventional SPECT [70]. Recent meta-analyses demonstrated that stress MPI using CZT-SPECT is a valuable indicator of adverse cardiovascular events in patients with known or suspected CCS [71].
Several studies have also compared functional assessment by SPECT and anatomical assessment with CCTA. CCTA remains a better predictor of MACE and revascularization. However, there was no difference between CCTA and SPECT as the first imaging test in directing patients toward optimal treatment [72]. CCTA may be more cost-effective than SPECT and is associated with a lower rate of subsequent invasive coronary angiography, with no difference in the outcome [73].
Biomarkers in risk stratification
Cardiac biomarkers are often classified into pathophysiological groups, such as inflammation, atherogenic metabolic, plaque instability, or myocardial ischemia biomarkers. A number of studies and reviews describe the role and prognostic value of biomarkers such as lipoprotein (a), IL-6, hsCRP, and IL-1β and risk models incorporating multiple biomarkers to predict cardiovascular events. This section will provide insights from recent studies regarding biomarkers that could be useful for predicting ACS before symptom onset and stratifying the risk of future cardiac events.
Inflammation biomarkers
Inflammatory biomarkers are promising markers associated with the prediction of cardiovascular events. They may also be targets for therapies aimed at decreasing the risk of MACE. Colchicine was approved in the US as the first anti-inflammatory therapy reducing the risk of cardiovascular events [74]. Canakinumab, an anti-inflammatory therapy targeting IL-1β, was also shown to reduce the risk of MACE in CCS patients [75]. However, due to higher risk of deadly infections, it was not approved for long-term treatment [74]. Other clinical trials, such as the ZEUS trial, will show whether direct inhibition of IL-6 by ziltivekimab decreases the incidence of cardiovascular events among patients with cardiovascular disease [76].
Another emerging group of biomarkers related to inflammation comprises markers related to NETosis, a process involving the formation of neutrophil extracellular traps (NETs). NETosis-related biomarkers, including circulating double-stranded or cell-free DNA, nucleosomes, citrullinated histone H3, and myeloperoxidase–DNA complexes, have been investigated as indicators of residual thrombo-inflammatory risk in CCS [77]. Their main advantage is strong biological plausibility: NETs may promote endothelial injury, plaque destabilization, tissue-factor-dependent thrombin generation, platelet activation, and coronary thrombus propagation, thereby linking inflammation with atherothrombosis [78]. In patients with angiographically verified stable CAD, elevated double-stranded DNA was associated with adverse outcomes including unstable angina, myocardial infarction, stroke, or death, whereas MPO–DNA complexes were not independently prognostic, highlighting both the potential and inconsistency of these markers [77]. Circulating DNA and chromatin markers have also been associated with severe coronary atherosclerosis and a prothrombotic phenotype [79]. However, major limitations include limited specificity, because cell-free DNA and nucleosomes may also reflect apoptosis, necrosis, or tissue injury, and limited assay standardization, particularly for MPO–DNA ELISA-based measurements [80]. At present, no NETosis biomarker is established for routine risk stratification in CCS. Therapeutically, NETosis is an attractive target, with experimental approaches including PAD4 inhibition, DNase-mediated NET degradation, and broader anti-inflammatory strategies such as colchicine, but these are not yet guided by NET biomarker testing [81]. Overall, NETosis biomarkers are promising investigational tools for identifying thrombo-inflammatory residual risk, but further standardized prospective studies are needed before they can be used to predict cardiovascular events in routine CCS care.
Atherogenic metabolic biomarkers
Oxidative-stress-related biomarkers have been investigated as indicators of residual cardiovascular risk in patients with CCS, particularly markers of oxidized lipids, redox imbalance, and oxidative protein damage. Oxidized phospholipids carried by apoB or Lp(a) appear among the most clinically relevant candidates: OxPL-apoB predicted secondary MACE in patients with CCS in the TNT substudy [82], while Lp(a)-associated OxPL-apoB and OxPL-apo(a) were associated with CAD severity and cardiovascular outcomes in the CASABLANCA cohort [83]. Other markers, including d-ROMs and aminothiol redox indices such as cystine, glutathione, and the cystine/glutathione ratio, have also been linked to future cardiovascular events or mortality in patients undergoing coronary angiography, supporting the role of systemic redox imbalance in CAD prognosis [84, 85]. More specific markers of oxidative damage, such as malondialdehyde-modified LDL (MDA-LDL) and protein carbonyls, may reflect plaque vulnerability, impaired fibrinolysis, and a prothrombotic phenotype. Recent studies suggest that MDA-LDL may predict cardiac events after PCI and improve risk prediction when combined with T1-weighted MRI detection of coronary high-intensity plaque [86]. Furthermore, elevated carbonylated proteins were associated with an HR 4.9 of MACE in patients with CCS [87].
The main advantages of these biomarkers are their ability to capture residual oxidative, inflammatory, and thrombotic risk not fully reflected by conventional lipid markers. However, their clinical utility is limited by heterogeneous assays, insufficient standardization and limited specificity. At present, oxidative-stress biomarkers are not routinely used to guide therapy, although the OxPL/Lp(a) axis is increasingly relevant because intensive lipid-lowering may attenuate OxPL-associated risk and emerging Lp(a)-lowering therapies may reduce the Lp(a)-associated oxidized phospholipid burden. Novel diagnostic approaches may also combine circulating oxidative biomarkers, such as MDA-LDL, with plaque imaging, but further prospective validation is required before these markers can be implemented in routine CAD risk stratification.
Factor XI – atherothrombotic biomarker
Factor XI (FXI), particularly its activated form FXIa, is an emerging coagulation-related biomarker that may reflect residual atherothrombotic risk in patients with CCS. FXIa links the contact and tissue factor-dependent coagulation pathways, amplifies thrombin generation, promotes fibrin formation, and may also contribute to vascular inflammation, endothelial permeability, platelet activation, and impaired fibrinolysis, making it biologically plausible as a marker of plaque-related thrombotic risk rather than myocardial injury itself [88, 89]. In stable or advanced CAD, elevated FXI/FXIa has been associated with greater coronary atherosclerotic burden and adverse outcomes. Circulating FXIa was reported in patients with ischemic cardiomyopathy and, in a long-term cohort of stable advanced CAD, was associated with an over six-fold higher MACE risk [90].
The major advantage of FXI as a biomarker is that it represents a therapeutically targetable thrombo-inflammatory pathway, potentially useful for identifying patients with high ischemic but also high bleeding risk who may benefit from FXI/FXIa-directed strategies. However, available clinical data are heterogeneous, and in some studies, associations appear stronger and more consistent for ischemic stroke than for myocardial infarction [91]. New trials target FXIa to investigate the association of FXIa inhibition and MACE risk. In the phase 2 PACIFIC-AMI trial, asundexian added to dual antiplatelet therapy after acute myocardial infarction produced dose-dependent FXIa inhibition, and did not significantly increase bleeding risk, but it also did not reduce the MACE rate [92]. More recently, the phase 3 LIBREXIA ACS trial of milvexian after recent ACS was discontinued because it was unlikely to meet its primary MACE efficacy endpoint [93]. Overall, FXI/FXIa is a biologically attractive and promising investigational biomarker of atherothrombotic risk in CCS, especially for refining residual thrombotic risk and selecting patients for future FXI-targeted therapies, but current evidence is insufficient to support its routine use as an independent predictor of cardiovascular events in CCS.
MicroRNA
Circulating miRNAs are promising biomarkers for risk stratification in stable CAD because they integrate information from several pathways involved in atherosclerosis, including endothelial dysfunction, inflammation, platelet activation, myocardial ischemia, angiogenesis, and vascular remodeling. In the AtheroGene cohort, selected circulating miRNAs, particularly miR-132, miR-140-3p, and miR-210, predicted cardiovascular death in patients with documented CCS and improved model discrimination beyond established clinical risk factors [94]. A more recent prospective study in stable CAD showed that adding miR-223-3p to traditional risk factors improved prediction of MACE [95]. The advantages of miRNAs include their relative stability in plasma or serum, detectability using qPCR, droplet digital PCR or sequencing-based platforms, and their potential to reflect disease mechanisms rather than only downstream myocardial injury. However, their clinical translation is limited by heterogeneous study populations, small validation cohorts, different biological sources of miRNAs (plasma, serum, platelets, extracellular vesicles), and lack of standardized normalization procedures. Some studies also reported negative or inconsistent findings, for example droplet digital PCR measurement of miR-499, miR-21, and miR-208a did not clearly predict long-term MACE or mortality in patients evaluated for functionally relevant CAD [96].
There is also growing interest in miRNA profiles as markers of treatment response: platelet-related miRNAs such as miR-223, miR-126, miR-21, miR-221, and miR-150 have been linked to platelet reactivity and responsiveness to antiplatelet therapy, while the randomized AFFECT miRNA trial suggested that ticagrelor downregulates the proatherogenic and proinflammatory miR-125b compared with clopidogrel after myocardial infarction [97]. Overall, miRNAs are biologically plausible and potentially useful biomarkers for identifying residual cardiovascular risk in stable CAD, but further prospective, standardized and externally validated studies are needed before they can guide clinical decisions or therapy selection.
Limitations
The primary limitation of this review stems from the lack of a single, universally accepted method for tracking the progression of CCS or identifying the transition from stable disease to acute coronary syndrome. Physiological and anatomical progression of coronary obstruction or further changes in plaque characteristics do not always correlate predictably with increased risk of ACS [98]. Furthermore, tracking CAD progression driven by microvascular dysfunction or vasospastic mechanisms introduces an even greater challenge [99]. MACE is a widely established, but imperfect, endpoint for evaluating prognosis of patients with CCS. It captures clinically meaningful downstream outcomes, including myocardial infarction, death, stroke, and coronary revascularization, depending on the definition used in individual studies. However, its use has important limitations, particularly the lack of a standardized definition across studies and the inability to directly capture the biological transition from stable plaque to acute plaque disruption [100].
In this review, we used MACE as clinically relevant and widely recognized composite outcome reflecting the risk of adverse cardiovascular events in patients with CCS. To address heterogeneity in endpoint definitions and improve comparability across studies, we extracted and organized the specific criteria used to define MACE in the cited studies. The definitions are summarized in Table VII.
Table VII
Heterogeneity of MACE definition across the studies
| MACE category | MACE components | Study reference |
|---|---|---|
| Two-point MACE | All-cause death and nonfatal MI | [8, 9, 12, 15, 23, 26, 30, 33, 40, 47, 58] |
| Three-point MACE | MI, stroke and cardiovascular death | [19, 75, 76, 93] |
| Nonfatal MI, all-cause death, and late coronary revascularization | [49] | |
| Four or more point MACE | Late coronary revascularization, hospitalization for unstable angina or heart failure, nonfatal myocardial infarction, and cardiac death or all-cause mortality | [18, 28, 32, 48, 60] |
| MI, stroke, systemic thromboembolism, cardiovascular death | [87, 90] | |
| Non-fatal MI, stroke, stent thrombosis, cardiovascular death | [92, 95] | |
| Non-fatal MI, stroke, resuscitation after cardiac arrest, cardiovascular death | [82] | |
| Coronary revascularization, nonfatal myocardial infarction, nonfatal stroke, and cardiovascular death | [83] | |
| MACE definition not specified | The research provided no specified definition of MACE | [10, 11, 13, 14, 16, 51, 52] |
| Variable definition (meta-analyses, systematic reviews) | MACE definitions varied across studies included in the meta-analysis or systematic review | [17, 20-22, 24, 25, 27, 29, 31, 34, 35, 39, 41, 45, 59, 74] |
Outlook and conclusions
The risk of future MACE or acute coronary events in patients with CCS depends on several complementary factors, including clinical risk, atherosclerotic burden, plaque vulnerability, vascular inflammation, and the functional significance of coronary stenoses. Therefore, no single non-invasive modality can fully capture cardiovascular risk, and different modalities may need to be combined in a stepwise clinical pathway.
First, clinical likelihood models, preferably incorporating cardiovascular risk factors and coronary artery calcium scoring when available, may identify patients with very low likelihood of obstructive CAD and a favorable prognosis, in whom further testing can often be avoided. However, patients with persistent symptoms, intermediate clinical likelihood, or discordant findings usually require imaging-based assessment.
Second, CCTA provides the most comprehensive first-line anatomical evaluation by assessing stenosis, coronary calcium, plaque burden, non-calcified plaque, and high-risk plaque features. Patients with extensive plaque burden or adverse plaque morphology may require intensified preventive therapy and closer follow-up. However, advanced plaque quantification, EAT, PCAT, and FAI remain insufficiently standardized and should currently be interpreted as complementary rather than standalone risk markers, as they are currently not recommended for risk stratification by the ESC guidelines [7].
Third, when stenosis severity is intermediate or functional significance remains uncertain, FFRCT, stress CMR, PET, or SPECT may be used to assess lesion-specific ischemia, inducible ischemia, myocardial perfusion reserve, scar, or microvascular dysfunction. These methods can help guide decisions regarding invasive angiography, revascularization, and treatment intensification.
Circulating biomarkers may add information on systemic inflammation, thrombosis, myocardial injury, or atherosclerotic activity, but they currently lack widely validated cutoffs and spatial specificity, and there is limited evidence that biomarker-guided strategies improve outcomes. They should therefore be regarded mainly as complementary or investigational tools.
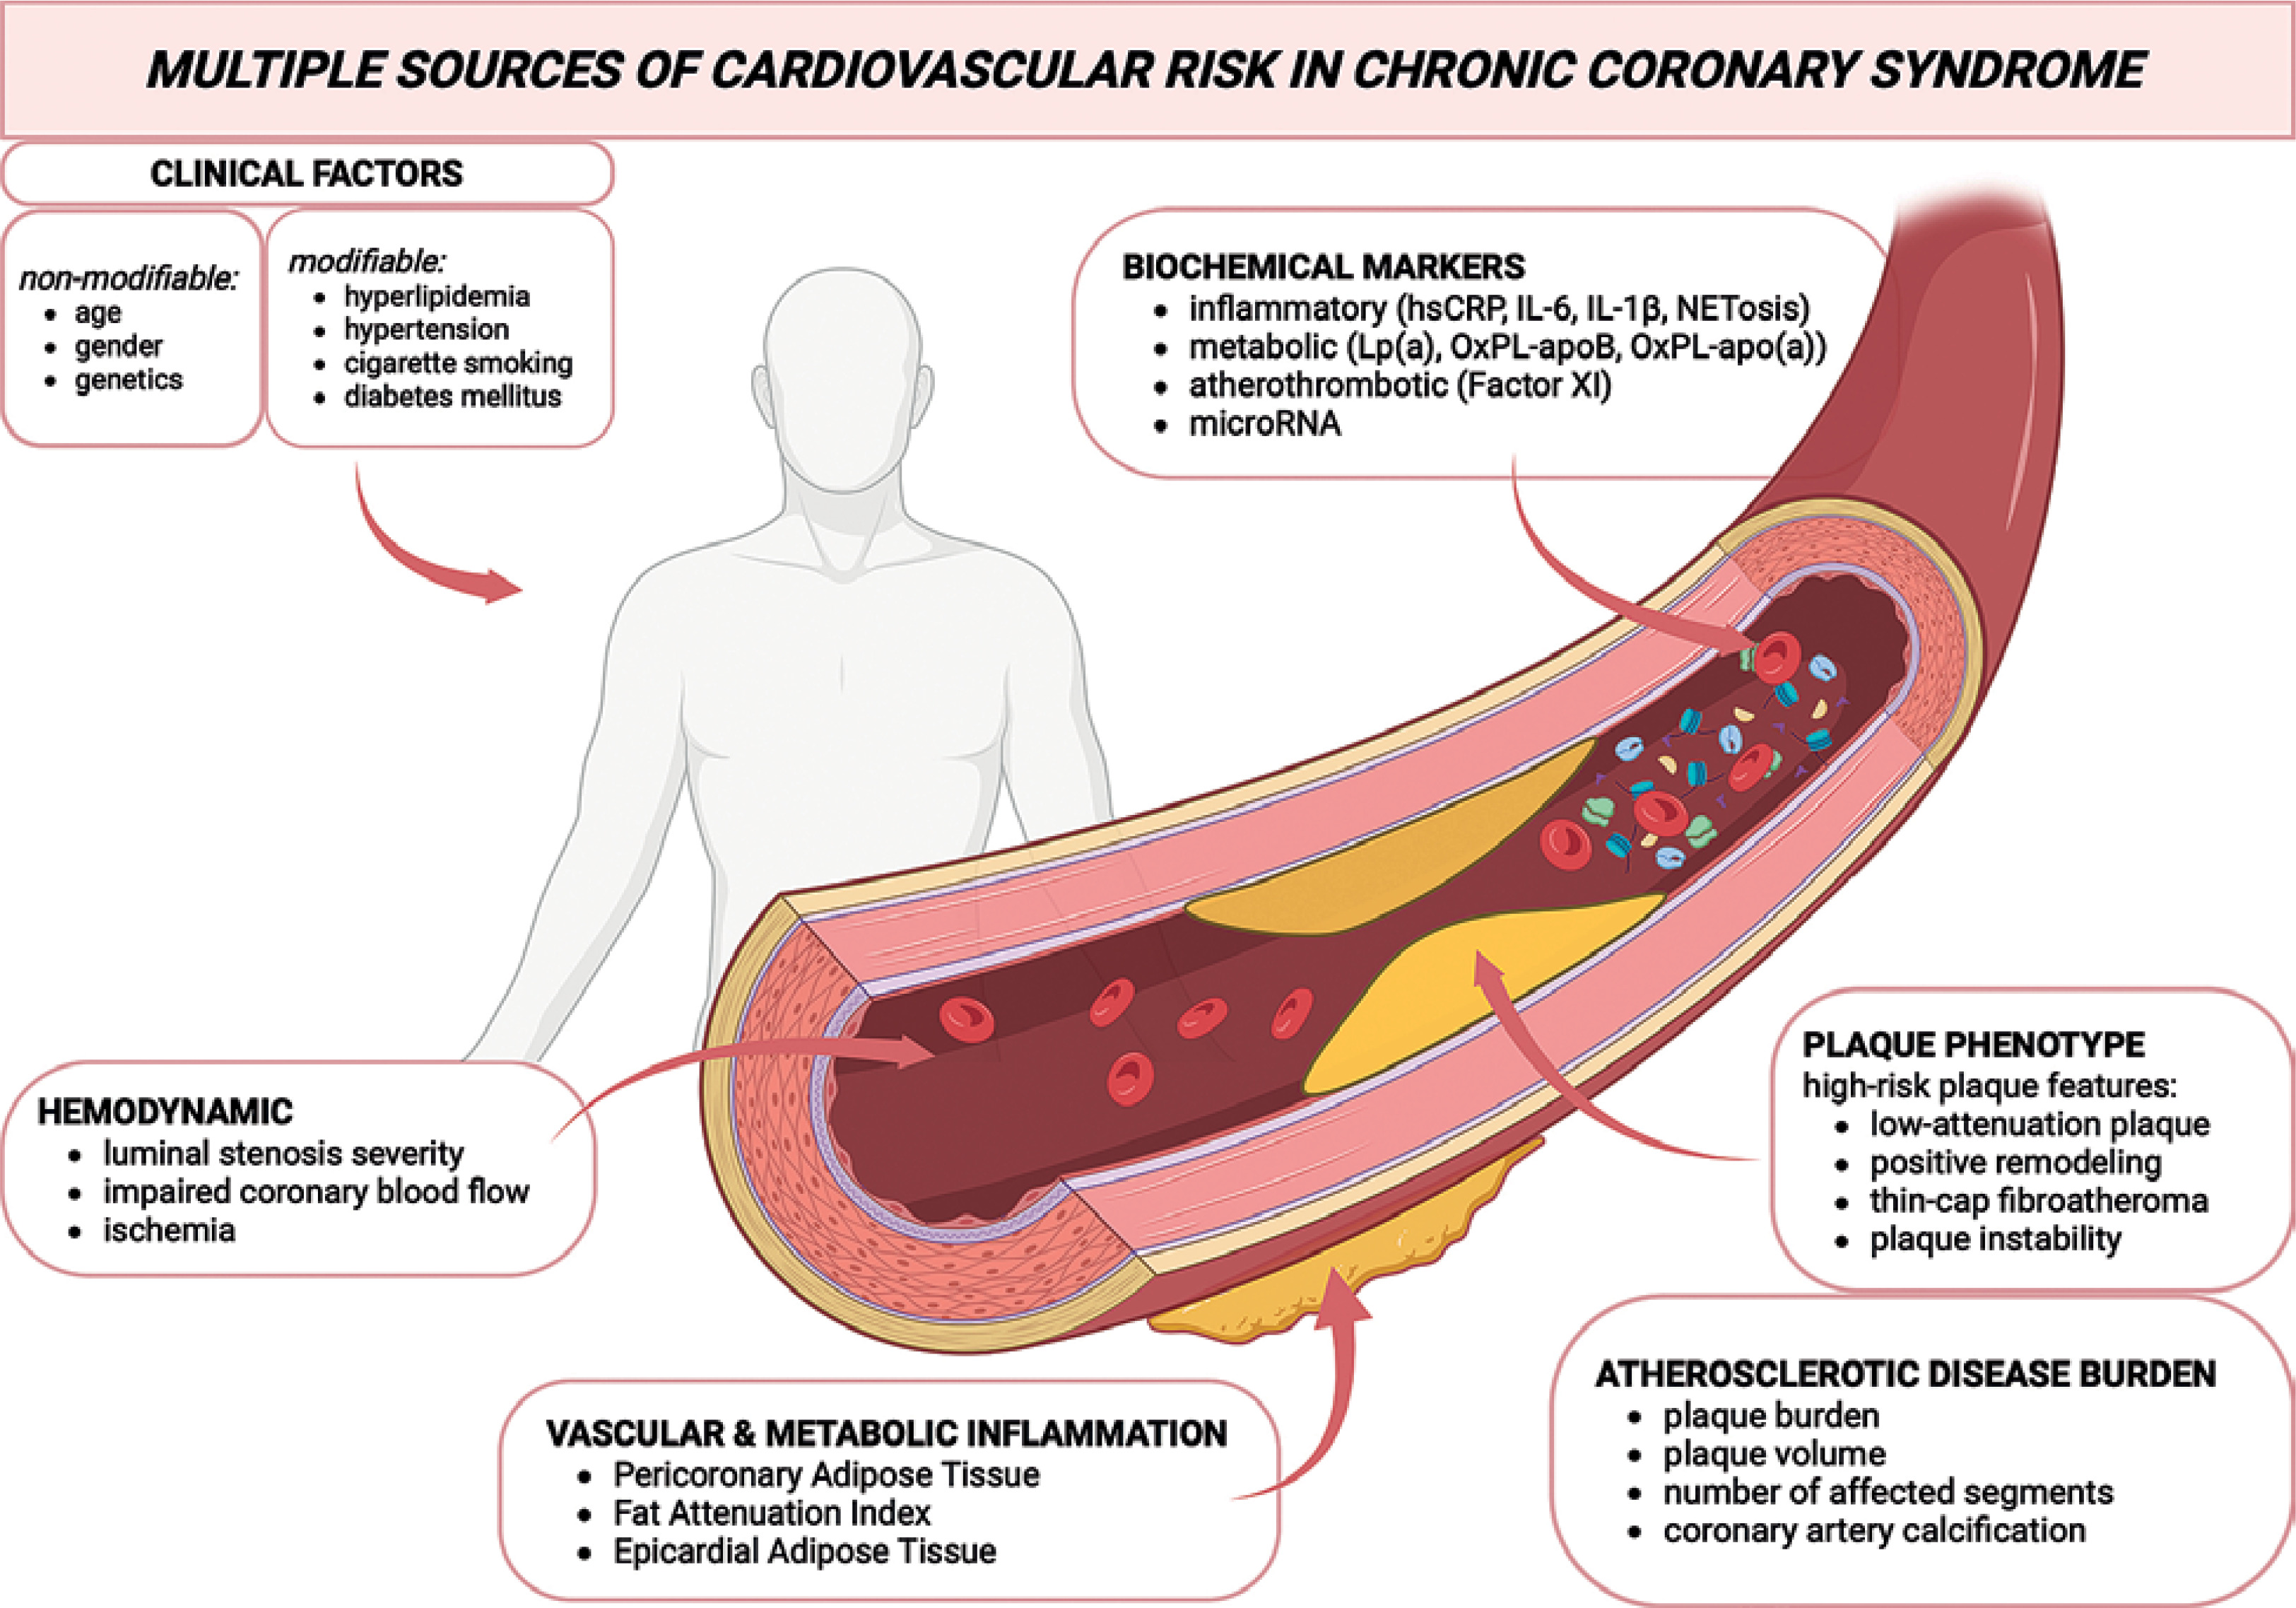
In conclusion, non-invasive risk assessment in CCS should be viewed as an integrated pathway: clinical likelihood models define baseline risk, CCTA characterizes anatomical and plaque-related risk, functional imaging or FFRCT clarifies the ischemic significance of coronary lesions, and emerging inflammatory or circulating biomarkers may refine residual risk. This approach may help clinicians identify patients who need no further testing, intensified prevention, closer surveillance, or referral for invasive evaluation. However, broader implementation remains limited by endpoint heterogeneity, lack of standardization, cost, availability, vendor dependence, and limited randomized evidence demonstrating improved clinical outcomes (Figures 1, 2).
Figure 1
Graphical abstract: Integrated MACE risk stratification in chronic coronary syndrome
CACS – coronary artery calcium score, CACS-CL – coronary artery calcium score-clinical likelihood, CCS – chronic coronary syndrome, CCTA – coronary computed tomography angiography, CMR – cardiac magnetic resonance, ECG – electrocardiography, FFRCT – fractional flow reserve derived from computed tomography, IL-6 – interleukin-6, Lp(a) – lipoprotein(a), MACE – major adverse cardiovascular events, MPRI – myocardial perfusion reserve index, PET – positron emission tomography, PVAT – perivascular adipose tissue, SPECT – single-photon emission computed tomography.
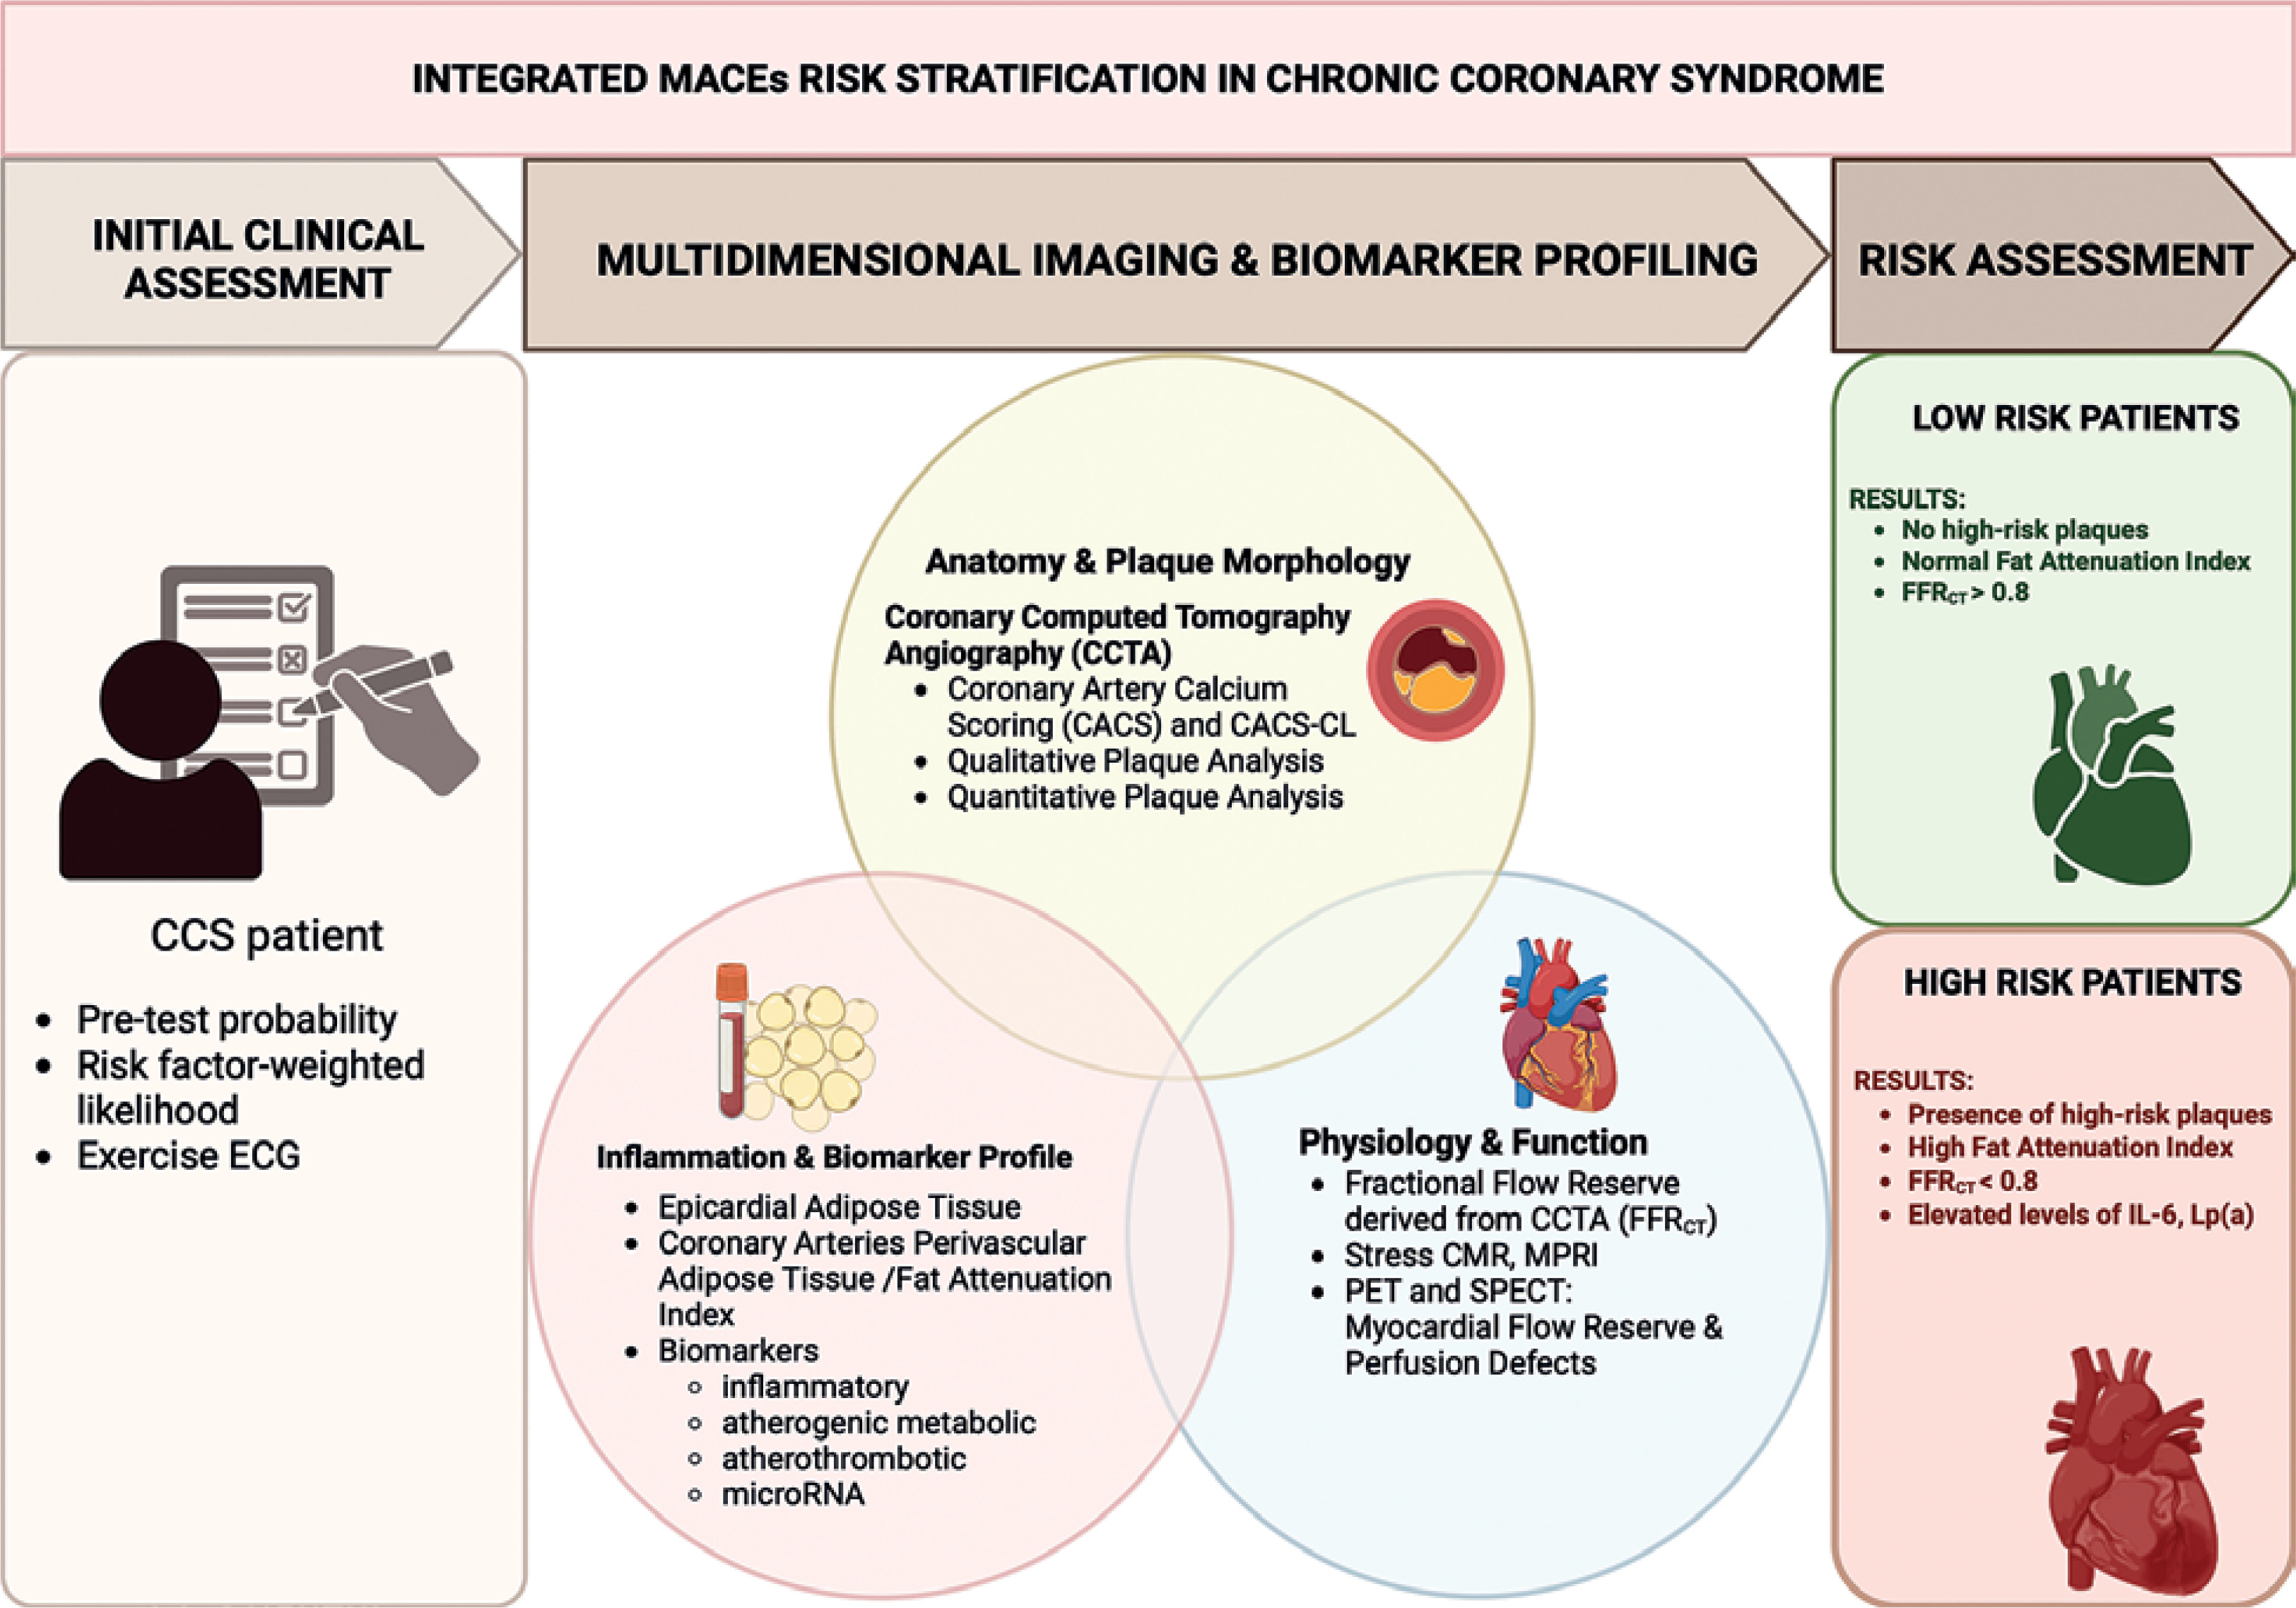
Figure 2
Multiple sources of cardiovascular risk in chronic coronary syndrome
hsCRP – high-sensitivity C-reactive protein, IL-1β – interleukin-1 beta, IL-6 – interleukin-6, Lp(a) – lipoprotein(a), microRNA – micro ribonucleic acid, NETosis – neutrophil extracellular trap (NET) formation, OxPL-apo(a) – oxidized phospholipids on apolipoprotein(a), OxPL-apoB – oxidized phospholipids on apolipoprotein B.