
Summary
This analysis of the DCB-DRAGON registry examined whether sex modifies long-term outcomes after treatment of coronary in-stent restenosis with a drug-coated balloon or a thin-strut, second-generation drug-eluting stent. It is a retrospective analysis of 1,317 patients. No sex-related heterogeneity of treatment effect was detectable on the composite endpoint (sex difference –0.083 years, 95% confidence interval –0.661 to +0.495; p = 0.78) or on any component, whether measured as a difference in restricted mean survival time, an absolute risk difference or a hazard ratio. These data provide no support for sex-based device selection; given the width of the confidence intervals and the differential follow-up, they establish the absence of detectable heterogeneity rather than equivalence.
Introduction
One of the main limitations of percutaneous coronary revascularisation with stenting is the risk of in-stent restenosis (ISR) during follow-up [1]. According to current guidelines, ISR is defined as a luminal narrowing within the stent or within the in-segment region of ≥ 50% of the vessel diameter on angiographic assessment [2]. The time from percutaneous coronary intervention (PCI) to ISR occurrence is influenced by several factors, including the type of PCI, the implanted stent, the antiplatelet drug regimen and treatment duration, target-lesion and target-vessel characteristics, and the control and burden of modifiable atherosclerosis risk factors, including the use of plaque-stabilizing therapy, as well as nonmodifiable factors such as sex, genetic predisposition, congenital metabolic diseases, and environmental exposures [3–5]. Despite improved control of modifiable risk factors and substantial advances in stent technology, ISR still occurs at an annual rate of approximately 1–2% with contemporary DES platforms [6]. These lesions are frequently encountered in clinical practice and, compared with de novo lesions, are associated with a higher incidence of adverse cardiac events, regardless of the interventional strategy used [1, 7, 8]. Registry data show that PCI for ISR is performed in approximately 10% of all PCI procedures [9, 10]. Drug-eluting stents (DES) and drug-coated balloons (DCB) are currently recommended as treatment modalities for ISR, with DES recommended as a first-line treatment strategy [11, 12]. Data comparing treatment outcomes after ISR treatment with DCB versus DES according to sex remain very limited, and no clear recommendations are available regarding the optimal treatment strategy for these patient subgroups [13].
Aim
Therefore, in this study, we assessed the long-term safety and efficacy of DCB versus thin-strut DES in men and women.
Material and methods
Study objectives
The analysed registry examined whether sex modifies the comparative effectiveness of DCB angioplasty versus thin-strut DES implantation in patients undergoing PCI for ISR, a clinical question raised by recent guidelines assigning a Class I recommendation favouring DES over DCB [14] and by the persistent underrepresentation of women in interventional trials [15]. The analysis is retrospective and was conducted on a closed registry; no dated protocol, registration identifier or archived statistical analysis plan governs it, and the present revision is post hoc relative to the original submission. Three questions were addressed: whether the sex-specific treatment effect on the device-oriented composite endpoint (DOCE) differs between women and men; whether any such difference emerges at the level of the individual components of the composite; and whether the findings withstand a competing-risk formulation, a complete-case analysis and an alternative time horizon. The endpoint hierarchy and the sensitivity analyses were defined by the analysts before the revised estimation but after the data were available.
Study design and data structure
Source registry
This retrospective analysis of the DCB-DRAGON registry comprised consecutive patients who underwent PCI for angiographically confirmed ISR between February 2008 and October 2021 at high-volume Polish tertiary centres. Reporting follows the STROBE statement [16], with the RECORD extension for routinely collected health data [17]. The primary estimand is the difference in restricted mean survival time over the 3-year window [18, 19], adopted because 57.6% of the cohort was censored before that horizon, so that the independent-censoring assumption required by a fixed-horizon absolute risk cannot be sustained. Balancing weights were obtained by entropy balancing within each sex stratum [20]; uncertainty was quantified by nonparametric bootstrap with re-estimation of the weights within every resample, pooled by Rubin’s rules across 20 imputations [21].
Eligibility and analytic cohort
Inclusion required PCI for confirmed ISR, treatment with DCB or thin-strut second-generation DES (everolimus-, zotarolimus-, biolimus-, or sirolimus-eluting platforms), and age ≥ 18 years at the index procedure. The closed registry yielded n = 1,317 patients with complete index-procedure data and at least one structured follow-up contact; no analytic exclusions were applied during cohort assembly (refer to Figure 1).
Figure 1
Cohort derivation and analysis flow in the DCB-DRAGON registry. Cohort assembly diagram prepared according to the STROBE statement for cohort studies [16] and the RECORD extension for routinely collected health data [17]. The diagram traces eligibility from screening of the DCB-DRAGON registry – consecutive patients who underwent percutaneous coronary intervention for angiographically confirmed in-stent restenosis between February 2008 and October 2021 across high-volume Polish tertiary centres – to the final analytic cohort (n = 1,317). Data quality control is reported explicitly: 5 records (0.38%) carrying a target-lesion revascularisation without the corresponding target-vessel revascularisation were corrected under the ARC-2 anatomical hierarchy, and the complete repair log appears in Supplementary Methods S§1. Six covariates had missing values and were imputed by chained equations with 20 imputations (Supplementary Table SIII). Sex stratification yielded 395 women (30.0%) and 922 men (70.0%); within-sex treatment allocation produced four cells: female-DCB (n = 207), female-DES (n = 188), male-DCB (n = 525), male-DES (n = 397). Event counts at the terminal nodes are totals accrued over the whole observation period and not risks at the 3-year horizon, and median observation is the reverse Kaplan–Meier estimate within each treatment arm, which makes the near-twofold disparity between arms visible. No analytic exclusions were applied at cohort assembly; the closed registry was used in its entirety. The diagram was redrawn for the present revision
ARC-2 – Academic Research Consortium-2, DCB – drug-coated balloon, DES – drug-eluting stent, ISR – in-stent restenosis, PCI – percutaneous coronary intervention, RECORD – REporting of studies Conducted using Observational Routinely-collected health Data, STROBE – Strengthening the Reporting of Observational Studies in Epidemiology.
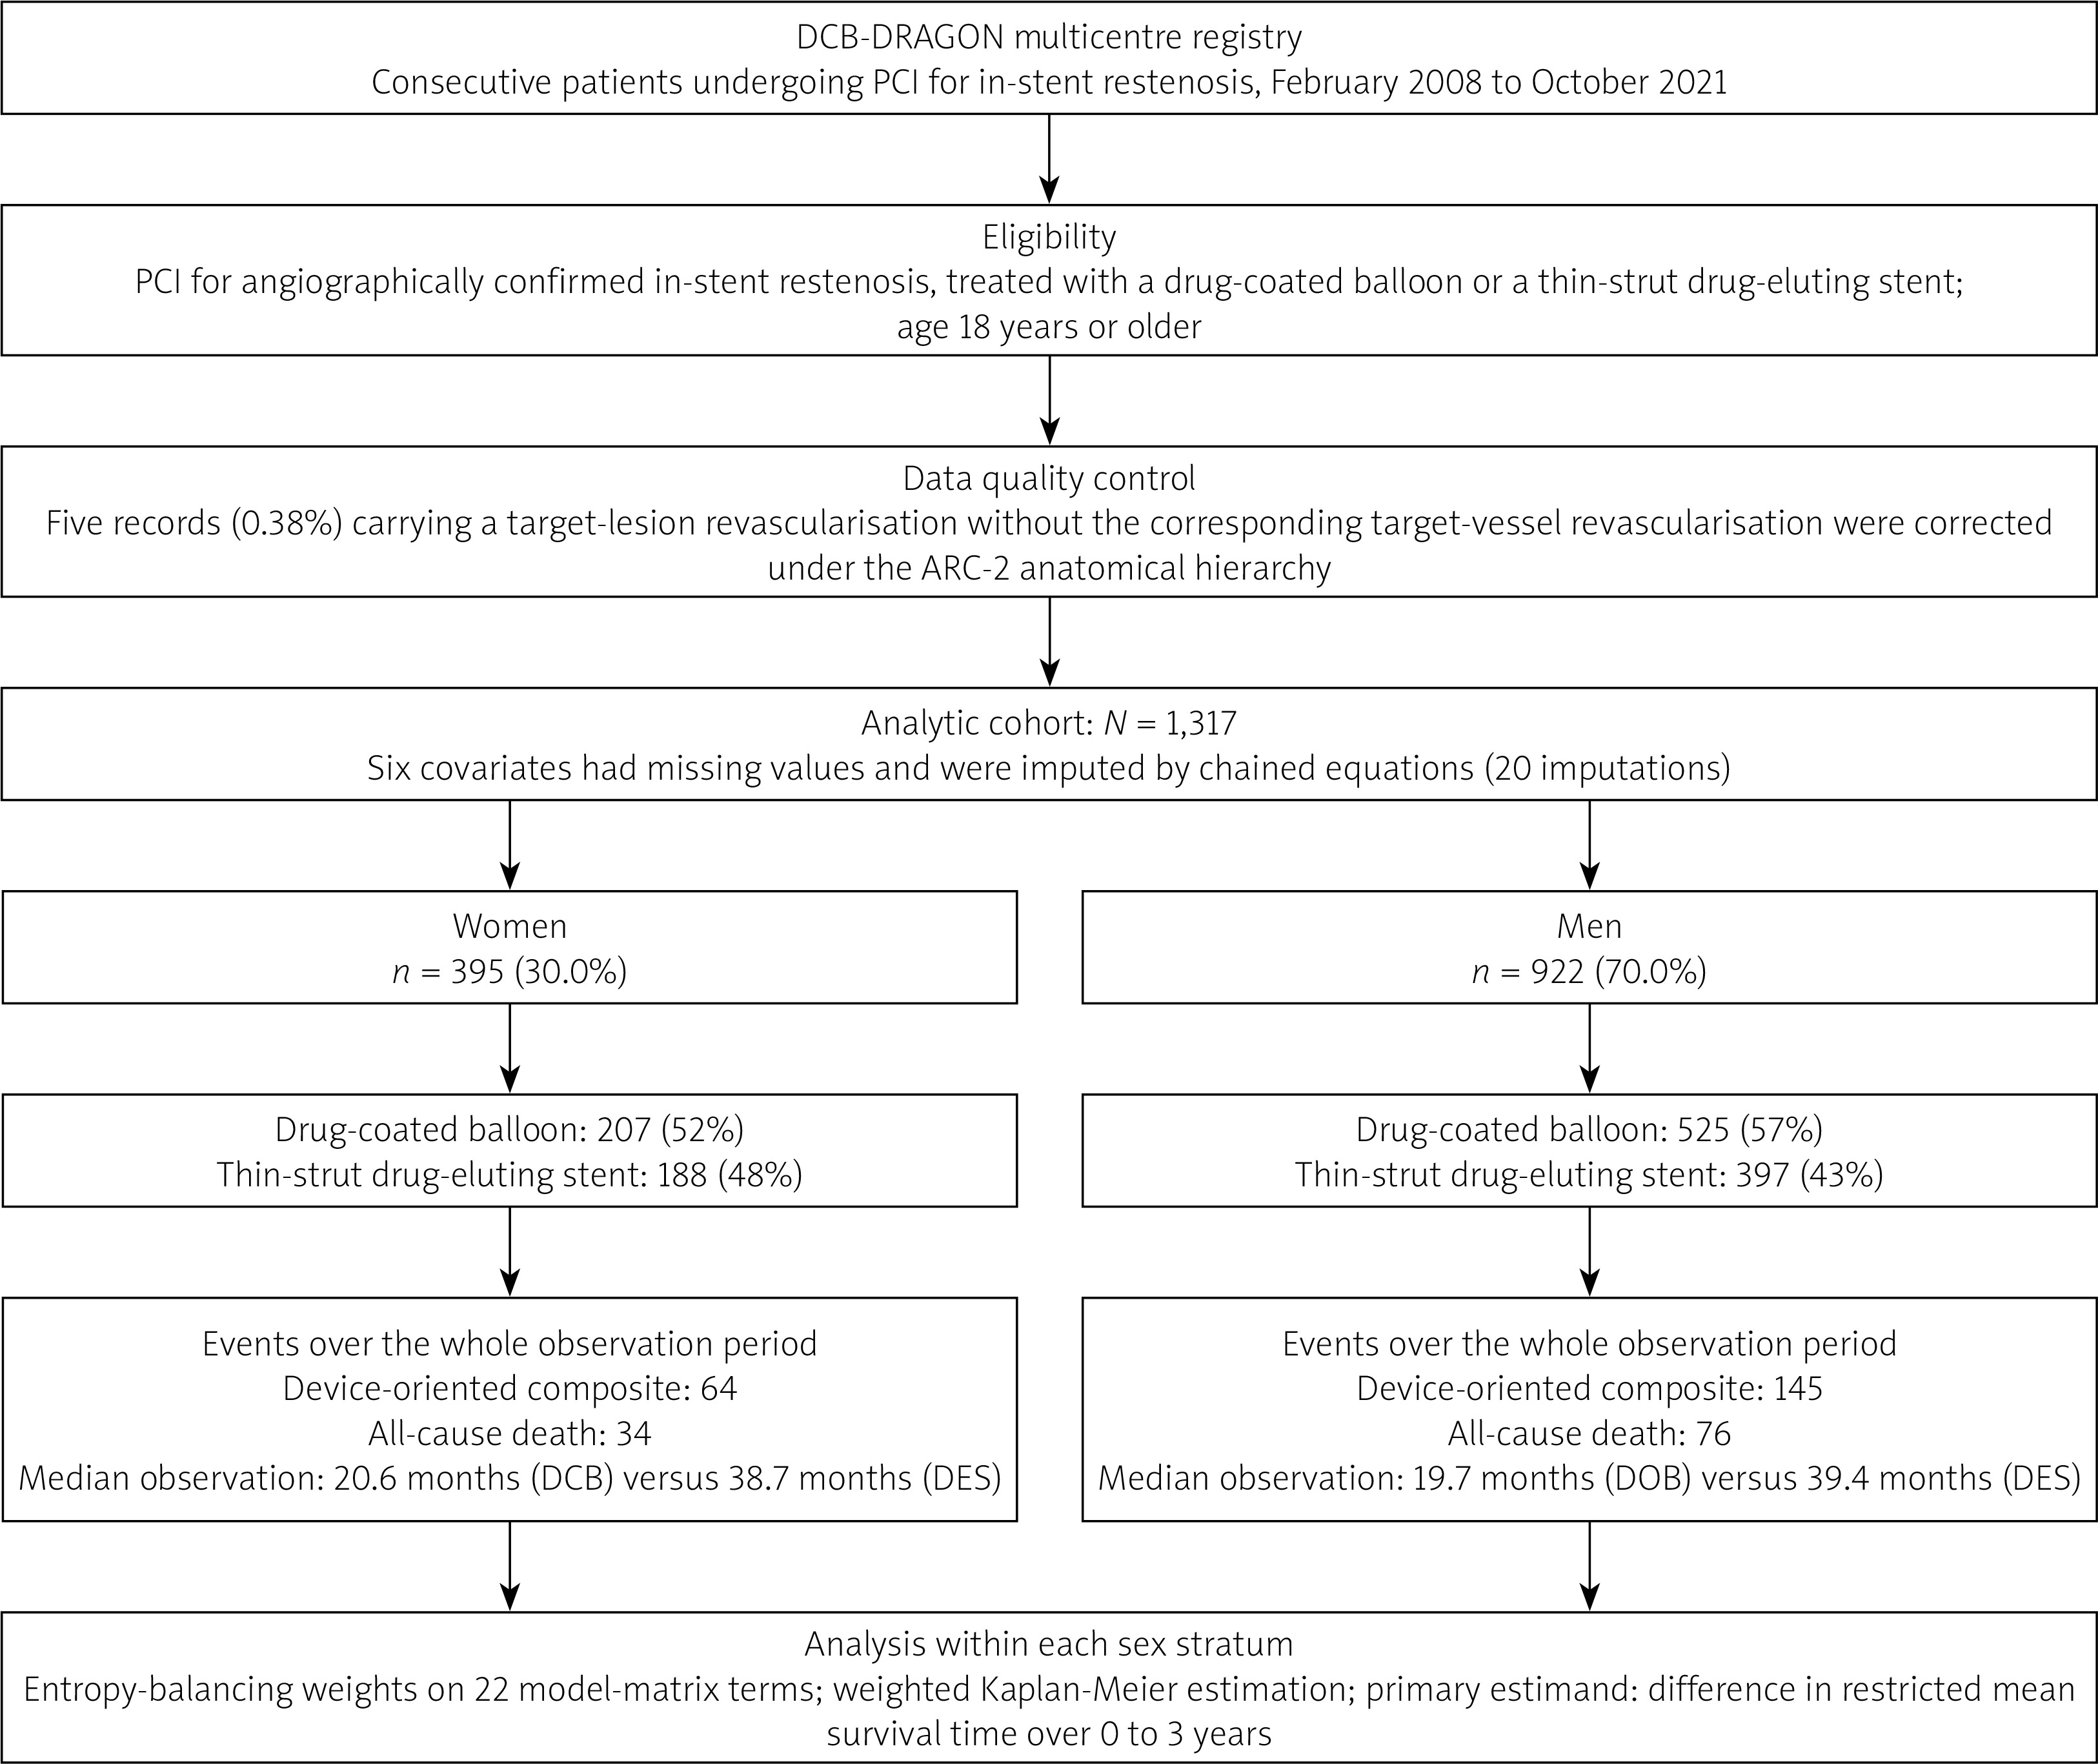
Five (0.38%) records with a target-lesion revascularisation without the corresponding target-vessel revascularisation were corrected under the anatomical hierarchy of the Academic Research Consortium-2 (ARC-2) [22], leaving the primary endpoint mathematically invariant; the data quality procedures and the complete repair log are detailed in Supplementary Methods S§1.
Variables and endpoints
Twenty conceptual baseline covariates were selected as confounders for the balancing model. One of them, in-stent restenosis morphology, is a four-level categorical variable expanded into three indicator terms with the occlusive pattern as reference, giving 22 model-matrix columns; the conceptual and model-matrix counts are distinguished throughout. Visible thrombus is retained in the balancing constraints but excluded from outcome models owing to quasi-separation in the female stratum, where 4 patients had the indicator and none experienced the primary event (Supplementary Methods S§2). The definitive numbered list appears in Supplementary Table SI and in the reproducibility repository. The device-oriented composite endpoint comprises cardiovascular death, target-vessel myocardial infarction or target-lesion revascularisation, whichever occurs first. Non-fatal MACE is programmed as the composite of target-vessel revascularisation or myocardial infarction, whichever occurs first; target-lesion revascularisation is contained within target-vessel revascularisation under the ARC-2 anatomical hierarchy [22] and is therefore not counted as a separate component. Endpoint definitions, event counts and the feasibility screen applied before estimation are given in Supplementary Table SII.
Statistical analysis
Descriptive statistics
The two-sided significance level was α = 0.05 throughout, with no adjustment of α beyond the multiplicity-control procedure applied to the secondary endpoints [23]. Continuous baseline variables are summarised as median [first, third quartile] with range, and categorical variables as counts (column percentages), with percentages calculated on the valid cases. Preweighting between-group comparisons in the descriptive Tables I and II employed the Mann–Whitney U test for continuous variables and Pearson’s χ² or Fisher’s exact test for categorical variables, with the choice driven by expected cell counts. These comparisons are descriptive, are not corrected for multiplicity and bear no inferential weight in the treatment-effect analysis.
Table I
Baseline demographic and clinical characteristics of the DCB-DRAGON cohort, stratified by patient sex (n = 1,317)
| Characteristic | Men (n = 922) | Women (n = 395) | P-value |
|---|---|---|---|
| Age [years] | – | – | < 0.001 |
| Median [Q1, Q3] | 66.0 [60.0, 73.2] | 69.0 [63.0, 76.0] | – |
| Range | 31.0–95.0 | 35.0–93.0 | – |
| Body mass index [kg/m²] | – | – | 0.61 |
| Median [Q1, Q3] | 28.4 [26.0, 31.3] | 28.1 [25.6, 31.3] | – |
| Range | 17.2–46.8 | 19.0–46.5 | – |
| Missing, n | 240 | 87 | – |
| Diabetes mellitus, n (%) | 374 (40.6) | 173 (43.8) | 0.30 |
| Insulin-treated diabetes, n (%) | 122 (13.2) | 61 (15.4) | 0.33 |
| Arterial hypertension, n (%) | 814 (88.3) | 361 (91.4) | 0.12 |
| Hyperlipidaemia, n (%) | 785 (85.1) | 336 (85.1) | 1.00 |
| Current smoker, n (%) | 191 (20.7) | 73 (18.5) | 0.39 |
| Atrial fibrillation, n (%) | 148 (16.1) | 62 (15.7) | 0.94 |
| Chronic kidney disease, n (%) | 181 (19.6) | 105 (26.6) | 0.006* |
| Dialysis dependence, n (%) | 14 (1.5) | 9 (2.3) | 0.46 |
| Previous myocardial infarction, n (%) | 584 (63.3) | 239 (60.5) | 0.36 |
| Previous CABG, n (%) | 199 (21.6) | 44 (11.1) | < 0.001* |
| Peripheral artery disease, n (%) | 167 (18.1) | 64 (16.2) | 0.45 |
| Family history of CAD, n (%) | 266 (29.9) | 136 (35.1) | 0.07 |
| Missing, n | 31 | 8 | – |
| Pulmonary disease, n (%) | 83 (9.0) | 35 (8.9) | 1.00 |
| LVEF, % | – | – | 0.010* |
| Median [Q1, Q3] | 50.0 [40.0, 55.0] | 50.0 [41.0, 58.0] | – |
| Range | 12.0–70.0 | 20.0–75.0 | – |
| Missing, n | 6 | 2 | – |
| Clinical presentation, n (%) | – | – | 0.003* |
| CCS | 444 (48.2) | 176 (44.6) | – |
| UA | 262 (28.4) | 142 (35.9) | – |
| NSTEMI | 187 (20.3) | 75 (19.0) | – |
| STEMI | 29 (3.1) | 2 (0.5) | – |
| Multivessel disease, n (%) | – | – | 0.011* |
| Single-vessel | 488 (53.2) | 244 (61.9) | – |
| Two-vessel | 293 (32.0) | 97 (24.6) | – |
| Three-vessel | 136 (14.8) | 53 (13.5) | – |
| Missing, n | 5 | 1 | – |
| Treatment strategy, n (%) | – | – | 0.15 |
| DCB | 525 (56.9) | 207 (52.4) | – |
| Thin-strut DES | 397 (43.1) | 188 (47.6) | – |
Continuous variables are summarised as median [first, third quartile] with range; categorical variables as counts (column percentage), with percentages calculated on the valid cases. P-values are from the Mann–Whitney U test for continuous variables and from Pearson’s χ² or Fisher’s exact test for categorical variables, the choice driven by expected cell counts; these comparisons are descriptive and are not corrected for multiplicity. Missing data: body mass index, n = 327 (24.8%); family history of coronary artery disease, n = 39 (3.0%); left ventricular ejection fraction, n = 8 (0.6%); multivessel disease classification, n = 6 (0.5%). CABG – coronary artery bypass grafting, CAD – coronary artery disease, CCS – chronic coronary syndrome, DCB – drug-coated balloon, DES – drug-eluting stent, LVEF – left ventricular ejection fraction, NSTEMI – non-ST-segment-elevation myocardial infarction, STEMI – ST-segment-elevation myocardial infarction, UA – unstable angina.
Table II
Angiographic and procedural characteristics of the index PCI for in-stent restenosis, stratified by patient sex (n = 1,317)
[i] Note. Continuous variables are summarised as median [first, third quartile] with range; categorical variables as counts (column percentage), with percentages calculated on the valid cases. P-values are from the Mann–Whitney U test for continuous variables and from Pearson’s χ² or Fisher’s exact test for categorical variables, the choice driven by expected cell counts; these comparisons are descriptive and are not corrected for multiplicity. No comparison in this table reached the conventional threshold of 0.05. Missing data: pre-procedural stenosis, n = 1 (0.1%); dual antiplatelet therapy duration, n = 12 (0.9%). DAPT – dual antiplatelet therapy, GP – glycoprotein, ISR – in-stent restenosis, IVUS – intravascular ultrasound, OCT – optical coherence tomography, PCI – percutaneous coronary intervention, TIMI – Thrombolysis In Myocardial Infarction.
Missing data treatment
Missing values were addressed by multiple imputation by chained equations under a missing-at-random assumption [24], with m = 20 imputed datasets and 20 iterations. The imputation model comprised the 22 model-matrix terms together with sex, treatment allocation, the event indicator and the Nelson–Aalen estimate of the cumulative hazard, the last two ensuring congeniality with the analysis model [25]; predictive mean matching was used for continuous terms and logistic regression for binary terms. Two variables audited for completeness – recorded follow-up duration and duration of dual antiplatelet therapy – enter neither the imputation model nor any analytical model and were not imputed. Little’s test rejects a completely random mechanism (p < 0.001); the test discriminates missingness completely at random from the alternatives but does not distinguish missingness at random from missingness not at random, so the missing-at-random assumption is stated rather than tested. Fractions of missing information for the pooled primary quantities lie below 0.01, so that m = 20 exceeds by a wide margin the heuristic that m should approximate 100 times the fraction of missing information. Per-variable missingness, the imputation method assigned to each variable and the convergence specification are reported in Supplementary Table SIII and Supplementary Methods S§3. Estimates and standard errors were pooled across imputations by Rubin’s combination rules [21]. A complete-case sensitivity analysis was performed and did not alter any conclusion.
Balancing weights and covariate balance assessment
Balancing weights were estimated independently within the female and male strata. Weights were obtained by entropy balancing in the sense of Hainmueller [20], that is, by maximising the entropy of the weight distribution subject to exact equality of the first moments of all 22 model-matrix terms between arms. The target estimand is the average treatment effect in the stratum population. Entropy balancing is a covariate-moment balancing procedure and is not equivalent to overlap weighting; no overlap-type weighting function was used, and no propensity score enters the estimator or any denominator. Weights were normalised to sum to the stratum size within each arm; no truncation or trimming was applied, and none was required, since the effective sample sizes retain between 79% and 86% of the nominal counts.
Inferential framework
Counterfactual survival was estimated by weighted Kaplan–Meier estimation, with the entropy-balancing weights entering the estimator directly. From the weighted curves we derived, within a single fit, the difference in restricted mean survival time over the 3-year window (primary estimand) [18, 19], the absolute risk difference at 3 and at 2 years (sensitivity), and the weighted hazard ratio, so that all measures are mutually consistent by construction. Uncertainty was quantified by nonparametric bootstrap with re-estimation of the entropy-balancing weights within every resample, 40 resamples being drawn within each of the 20 imputed datasets. The bootstrap serves to estimate the within-imputation variance; estimates and variances are combined by Rubin’s rules, and confidence intervals derive from the t distribution with Barnard–Rubin degrees of freedom rather than from bootstrap percentiles. Contrasts between the sexes are formed from the pooled stratum-specific estimates under a normal approximation. The estimator and the pooling rules are specified in full in Supplementary Methods S§4.
Sensitivity analyses
Robustness was assessed by: (i) Fine–Gray sub-distribution hazards regression with death as a competing event [26], fitted without covariate adjustment and reported together with Aalen–Johansen cumulative incidence at 3 years; (ii) a complete-case analysis; (iii) a 2-year horizon; and (iv) a feasibility screen excluding from inference any endpoint with fewer than ten events in any sex-by-treatment cell. The competing-risk analysis is unadjusted, so that its divergence from the principal analysis reflects both the change of estimand and the absence of balancing; this is stated wherever the two are compared. E-value analysis has been removed, since the bound governs confounding of an exposure–outcome association and does not transfer to a difference between two such associations. Implementation details appear in Supplementary Methods S§5.
Software and reproducibility
All analyses were performed in R version 4.6.1 [27]. The analytical packages, with their versions and their roles in the pipeline, are listed in Supplementary Table SX, and the corresponding software citations follow that table. The complete pipeline, structured as a sequenced collection of versioned scripts producing immutable intermediate artefacts under a single global random seed, is described in Supplementary Methods S§6. Numerical results follow the journal convention: p-values above 0.05 are reported to two decimal places, p-values at or below 0.05 to three decimal places, and p < 0.001 replaces values below the third-decimal precision; risk differences and percentages are given to two decimal places and differences in restricted mean survival time to three.
Results
Cohort characteristics
The DCB-DRAGON cohort comprised 1,317 patients (922 men [70.0%], 395 women [30.0%]) treated for ISR between February 2008 and October 2021 across high-volume Polish tertiary centres (Figure 1). Women were older than men (median 69.0 [Q1–Q3: 63.0–76.0] vs. 66.0 [60.0–73.2] years; p < 0.001), more frequently affected by chronic kidney disease (26.6% vs. 19.6%; p = 0.006), and presented less often with prior coronary artery bypass grafting (11.1% vs. 21.6%; p < 0.001) or ST-segment elevation myocardial infarction (0.5% vs. 3.1%) but more frequently with unstable angina (35.9% vs. 28.4%; presentation overall p = 0.003) (Table I). Multivessel disease distribution differed modestly between sexes (p = 0.011), with women more frequently presenting with single-vessel disease (61.9% vs. 53.2%). Body mass index, diabetes prevalence, smoking status, hypertension, hyperlipidaemia, atrial fibrillation, and family history of coronary disease were comparable between strata.
Angiographic and procedural characteristics were broadly similar between sexes (Table II). Mehran ISR morphology distributions were closely aligned (p = 0.93), as were preprocedural stenosis severity (median 80% [75–90] in both strata; p = 0.97), bifurcation involvement, calcification burden, treated coronary territory distribution, intracoronary imaging utilisation, postprocedural residual stenosis, TIMI 3 flow attainment (98.8% vs. 99.7%), periprocedural complications, and dual antiplatelet therapy duration (median 12.0 months in both strata; p = 0.20). Treatment allocation between DCB and thin-strut DES did not differ by sex (DCB: 56.9% men vs. 52.4% women; p = 0.15). Within-stratum baseline characteristics by treatment arm and per-variable missingness summaries are reported in Supplementary Tables SVa–SVb and S3, respectively.
Covariate balance and analytic framework
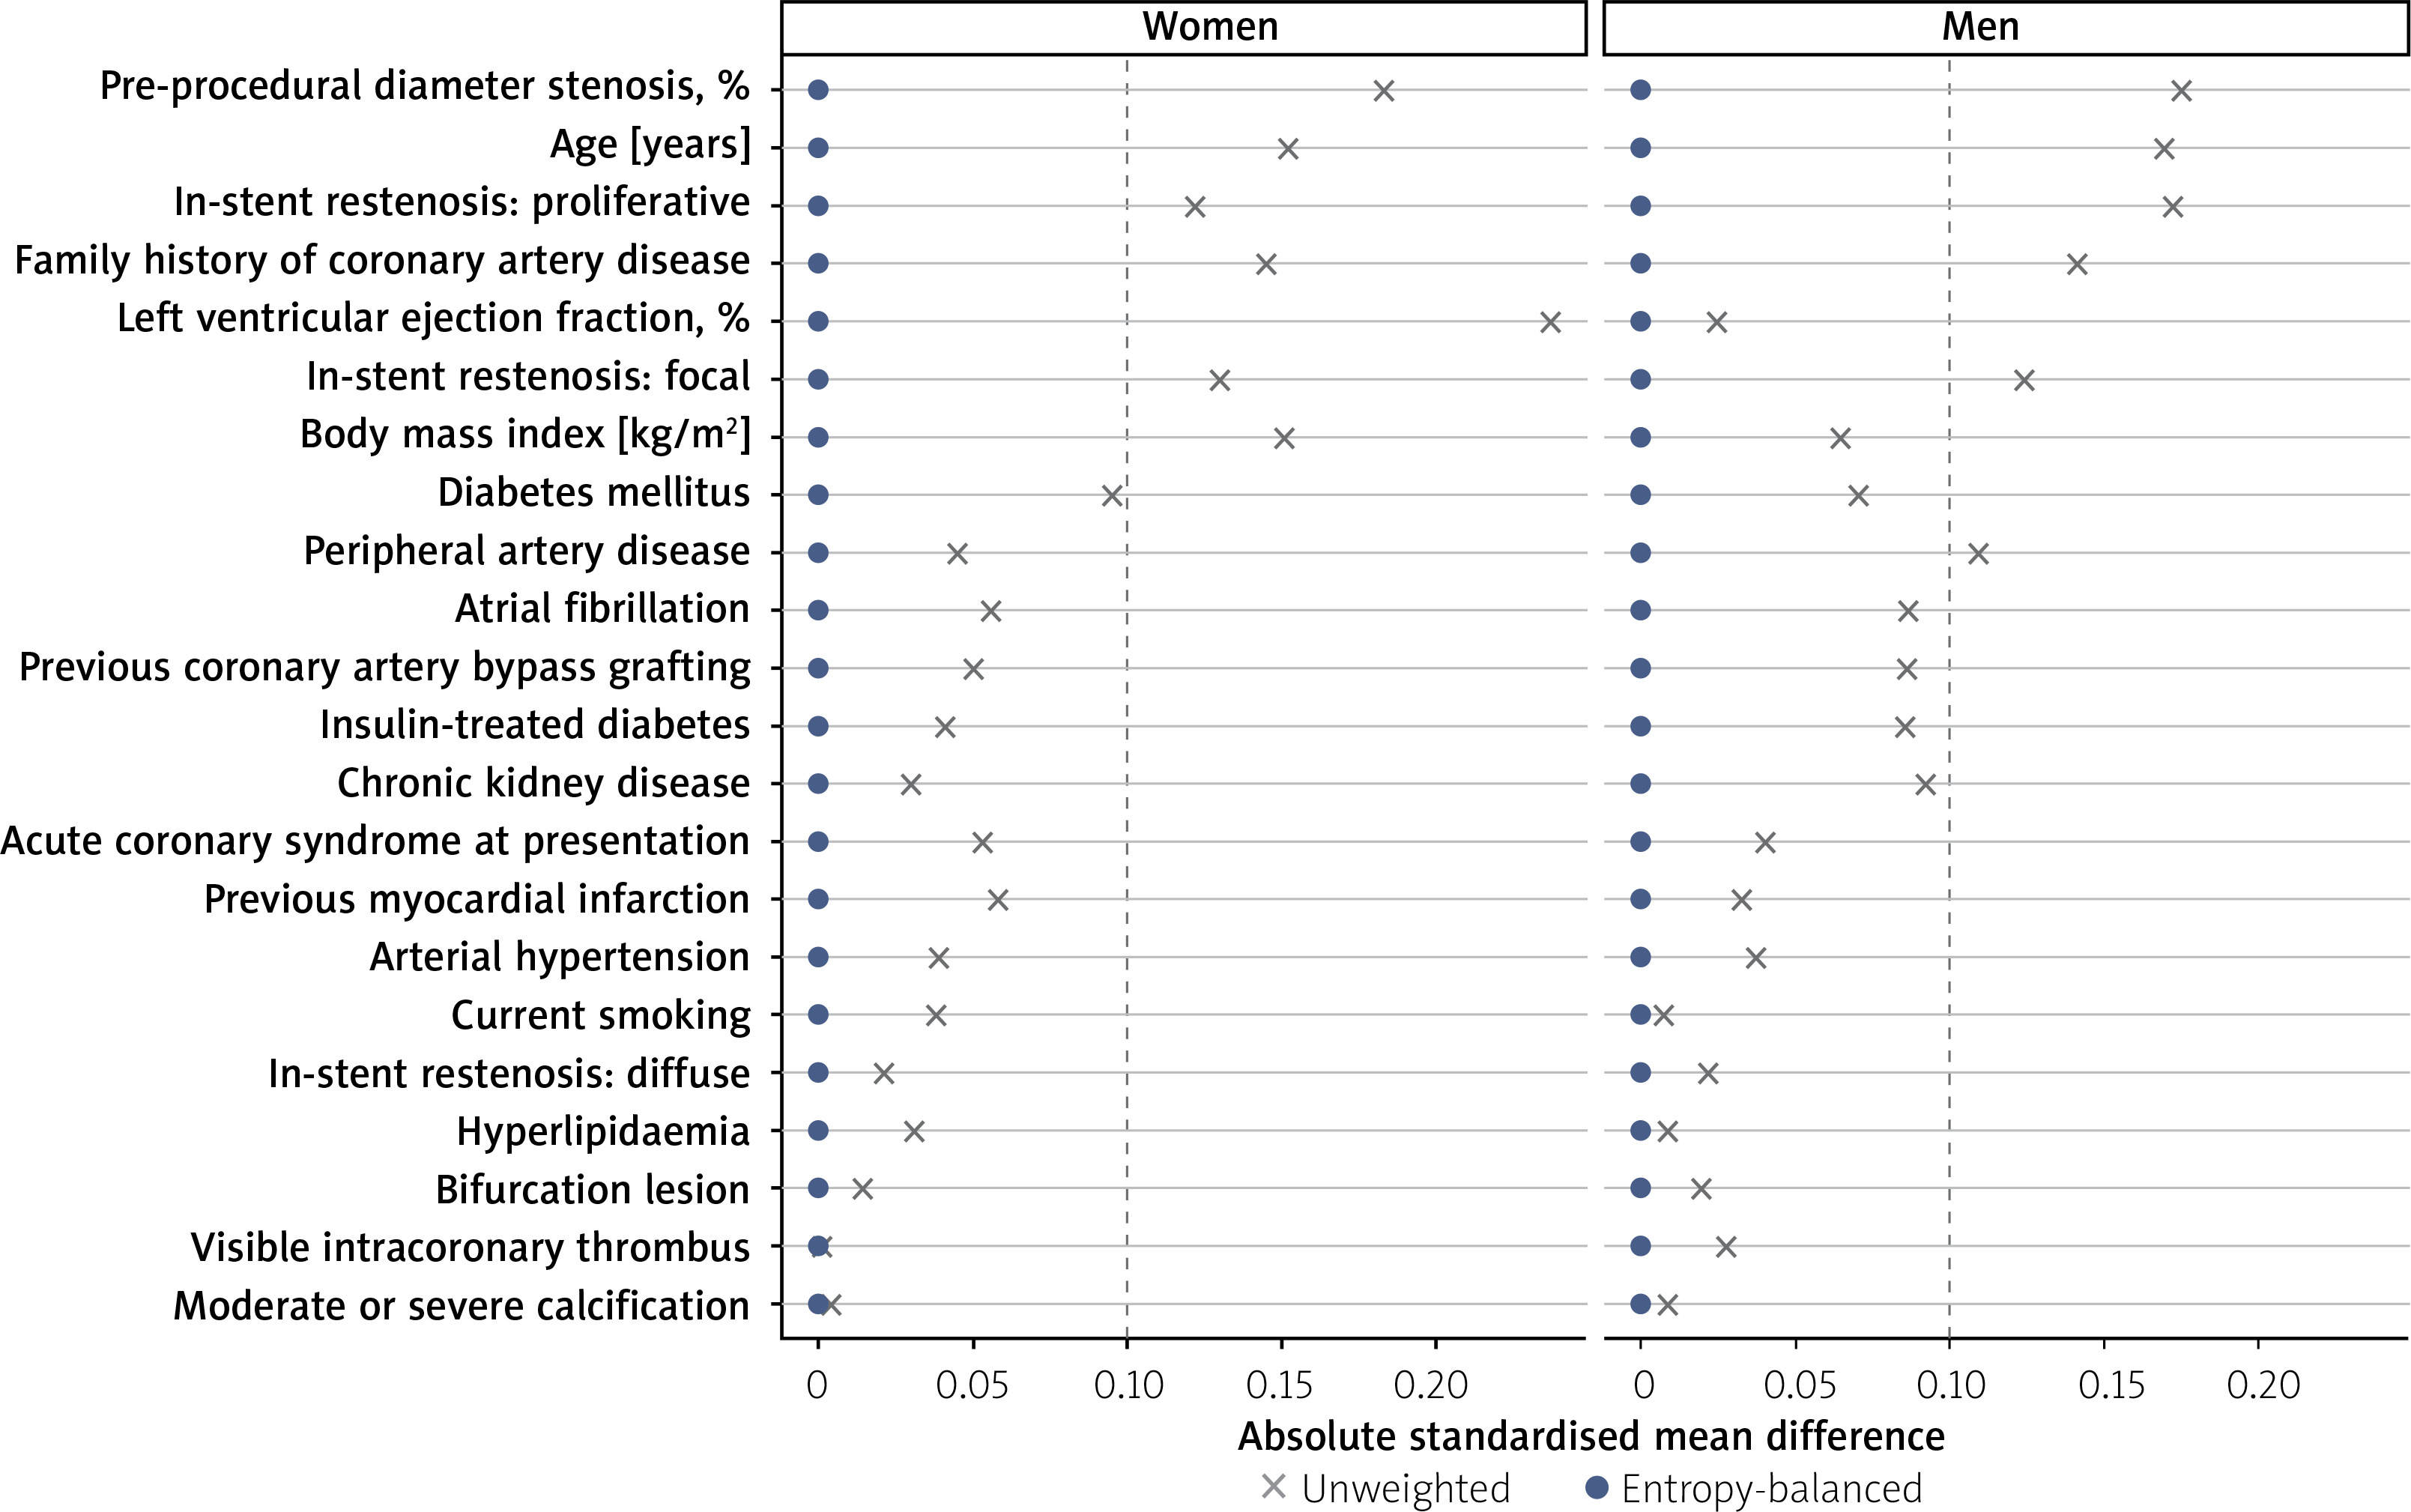
Entropy-balancing weighting on the 22 model-matrix terms achieved exact first-moment balance in both strata (Figure 2, Supplementary Table SIV). Before weighting, seven terms in women and six in men exceeded the conventional threshold of 0.10 [28], with maximum absolute standardised mean differences of 0.237 and 0.176 respectively. Effective sample sizes after weighting retain between 79% and 86% of the nominal counts: 161.4 of 188 and 178.9 of 207 in women, 312.4 of 397 and 433.6 of 525 in men.
Figure 2
Covariate balance before and after entropy-balancing weighting, by sex stratum. Absolute standardised mean differences for all 22 model-matrix terms, shown before and after entropy-balancing weighting and separately for the female stratum (n = 395) and the male stratum (n = 922). The dashed line marks the conventional threshold of 0.10 [28]. Before weighting, seven terms in women and six in men exceeded that threshold, with maxima of 0.237 and 0.176, respectively. Entropy balancing enforces exact equality of first moments, so weighted differences are zero by construction; this is a property of the method rather than evidence of unusually good balance. The tabulated values appear in Supplementary Table SIV
SMD = standardised mean difference.
Primary endpoint: device-oriented composite outcome
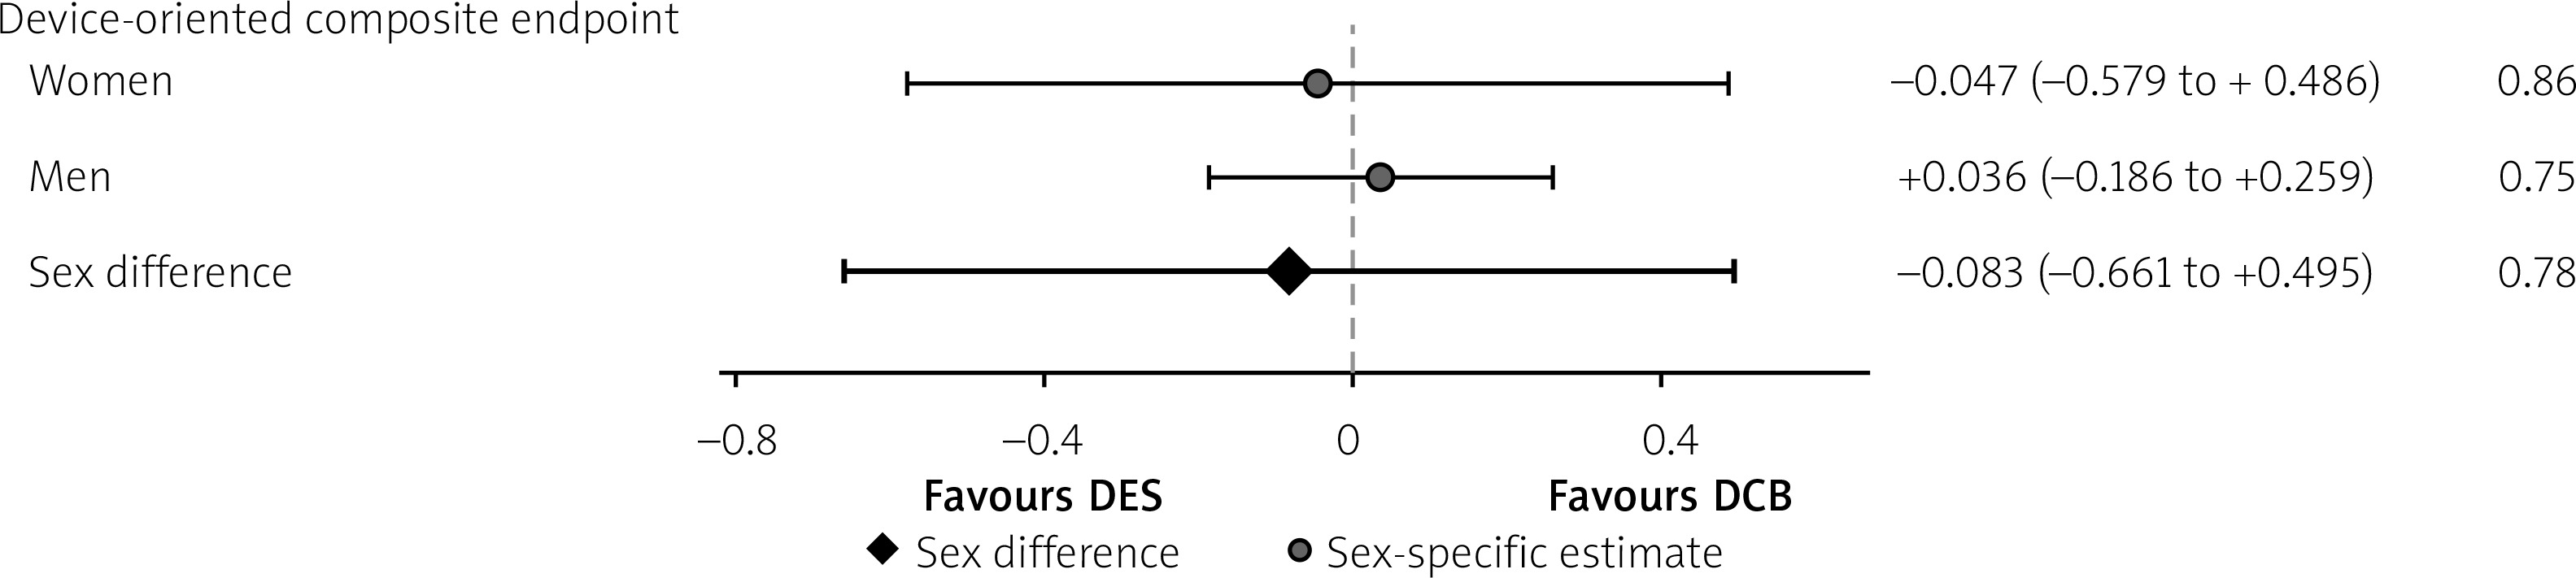
Median observation time differed markedly between treatment arms: by reverse Kaplan–Meier [29] it was 20.6 months for women treated with a drug-coated balloon versus 38.7 months for those treated with a drug-eluting stent, and 19.7 versus 39.4 months among men (Table III, Figure 3). Endpoint status at 3 years was known for 24.2% and 57.4% of women and for 31.0% and 59.7% of men. Over the whole observation period, 209 device-oriented composite events accrued (women 64 of 395; men 145 of 922). The difference in restricted mean survival time over the 3-year window was –0.047 years (95% CI: –0.579 to +0.486) in women and +0.036 years (–0.186 to +0.259) in men, giving a sex difference of –0.083 years (–0.661 to +0.495; p = 0.78). Weighted 3-year risks were 21.2% versus 26.0% in women and 17.5% versus 21.6% in men, with weighted hazard ratios of 0.76 (0.43–1.34) and 0.73 (0.50–1.07). No sex-related heterogeneity was detectable for the primary endpoint (Table IV, Figures 4 and 5). Weighted hazard ratios for every endpoint, together with the Rubin variance components and the effective sample sizes, are reported in Supplementary Table SIX.
Table III
Follow-up completeness by sex and treatment: reverse Kaplan–Meier median observation and the proportion of patients with known endpoint status at each horizon
[i] Note. Reverse Kaplan–Meier estimation follows Schemper and Smith [29], reversing the censoring indicator so that the estimated median describes observation rather than event-free survival. Median observation differs approximately twofold between treatment arms in both sexes, and 57.6% of the whole cohort (759 of 1,317 patients) is censored before the 3-year horizon. This disparity precludes reliance on fixed-horizon absolute risks and motivated adoption of the difference in restricted mean survival time as the primary estimand. The characteristics of patients with and without known status at 3 years are compared in Supplementary Table SVIII. DCB – drug-coated balloon, DES – drug-eluting stent, KM – Kaplan–Meier.
Table IV
Sex-specific treatment effect on the primary device-oriented composite endpoint, expressed as the difference in restricted mean survival time over the 3-year window, with weighted absolute risks and hazard ratios from the same fit
[i] Note. Estimates from weighted Kaplan–Meier fits with entropy-balancing weights targeting the average treatment effect within each sex stratum, pooled across 20 imputed datasets by Rubin’s rules; standard errors from nonparametric bootstrap with re-estimation of the weights within every resample, 40 resamples per imputed dataset, and confidence intervals from the t distribution with Barnard–Rubin degrees of freedom. Negative values of the restricted mean survival time difference favour the drug-eluting stent. Events are counts accrued over the whole observation period. The p-values in the final column refer to the stratum-specific contrast in the first two rows and to the sex contrast in the third. These estimates replace those of the original submission, which were produced by an estimator whose augmentation term was identically zero. Variance components and effective sample sizes are reported in Supplementary Table SIX. CI – confidence interval, DCB – drug-coated balloon, DES – drug-eluting stent, HR – hazard ratio, RMST – restricted mean survival time.
Figure 3
Follow-up completeness by sex and treatment, estimated by reverse Kaplan–Meier. Reverse Kaplan–Meier estimates of follow-up completeness [29], obtained by reversing the censoring indicator so that the estimated median describes observation rather than event-free survival. Median observation is 20.6 months for women treated with a drug-coated balloon versus 38.7 months for those treated with a drug-eluting stent, and 19.7 versus 39.4 months among men; the corresponding values are tabulated in Table III. Shaded bands are pointwise 95% confidence intervals, and the dotted line marks the 3-year primary horizon. Reverse Kaplan–Meier describes the observed data rather than a population parameter, so the intervals are supplied for completeness rather than for inference. The horizontal axis is labelled in years, whereas follow-up is reported in months in the text and tables
DCB – drug-coated balloon, DES – drug-eluting stent.
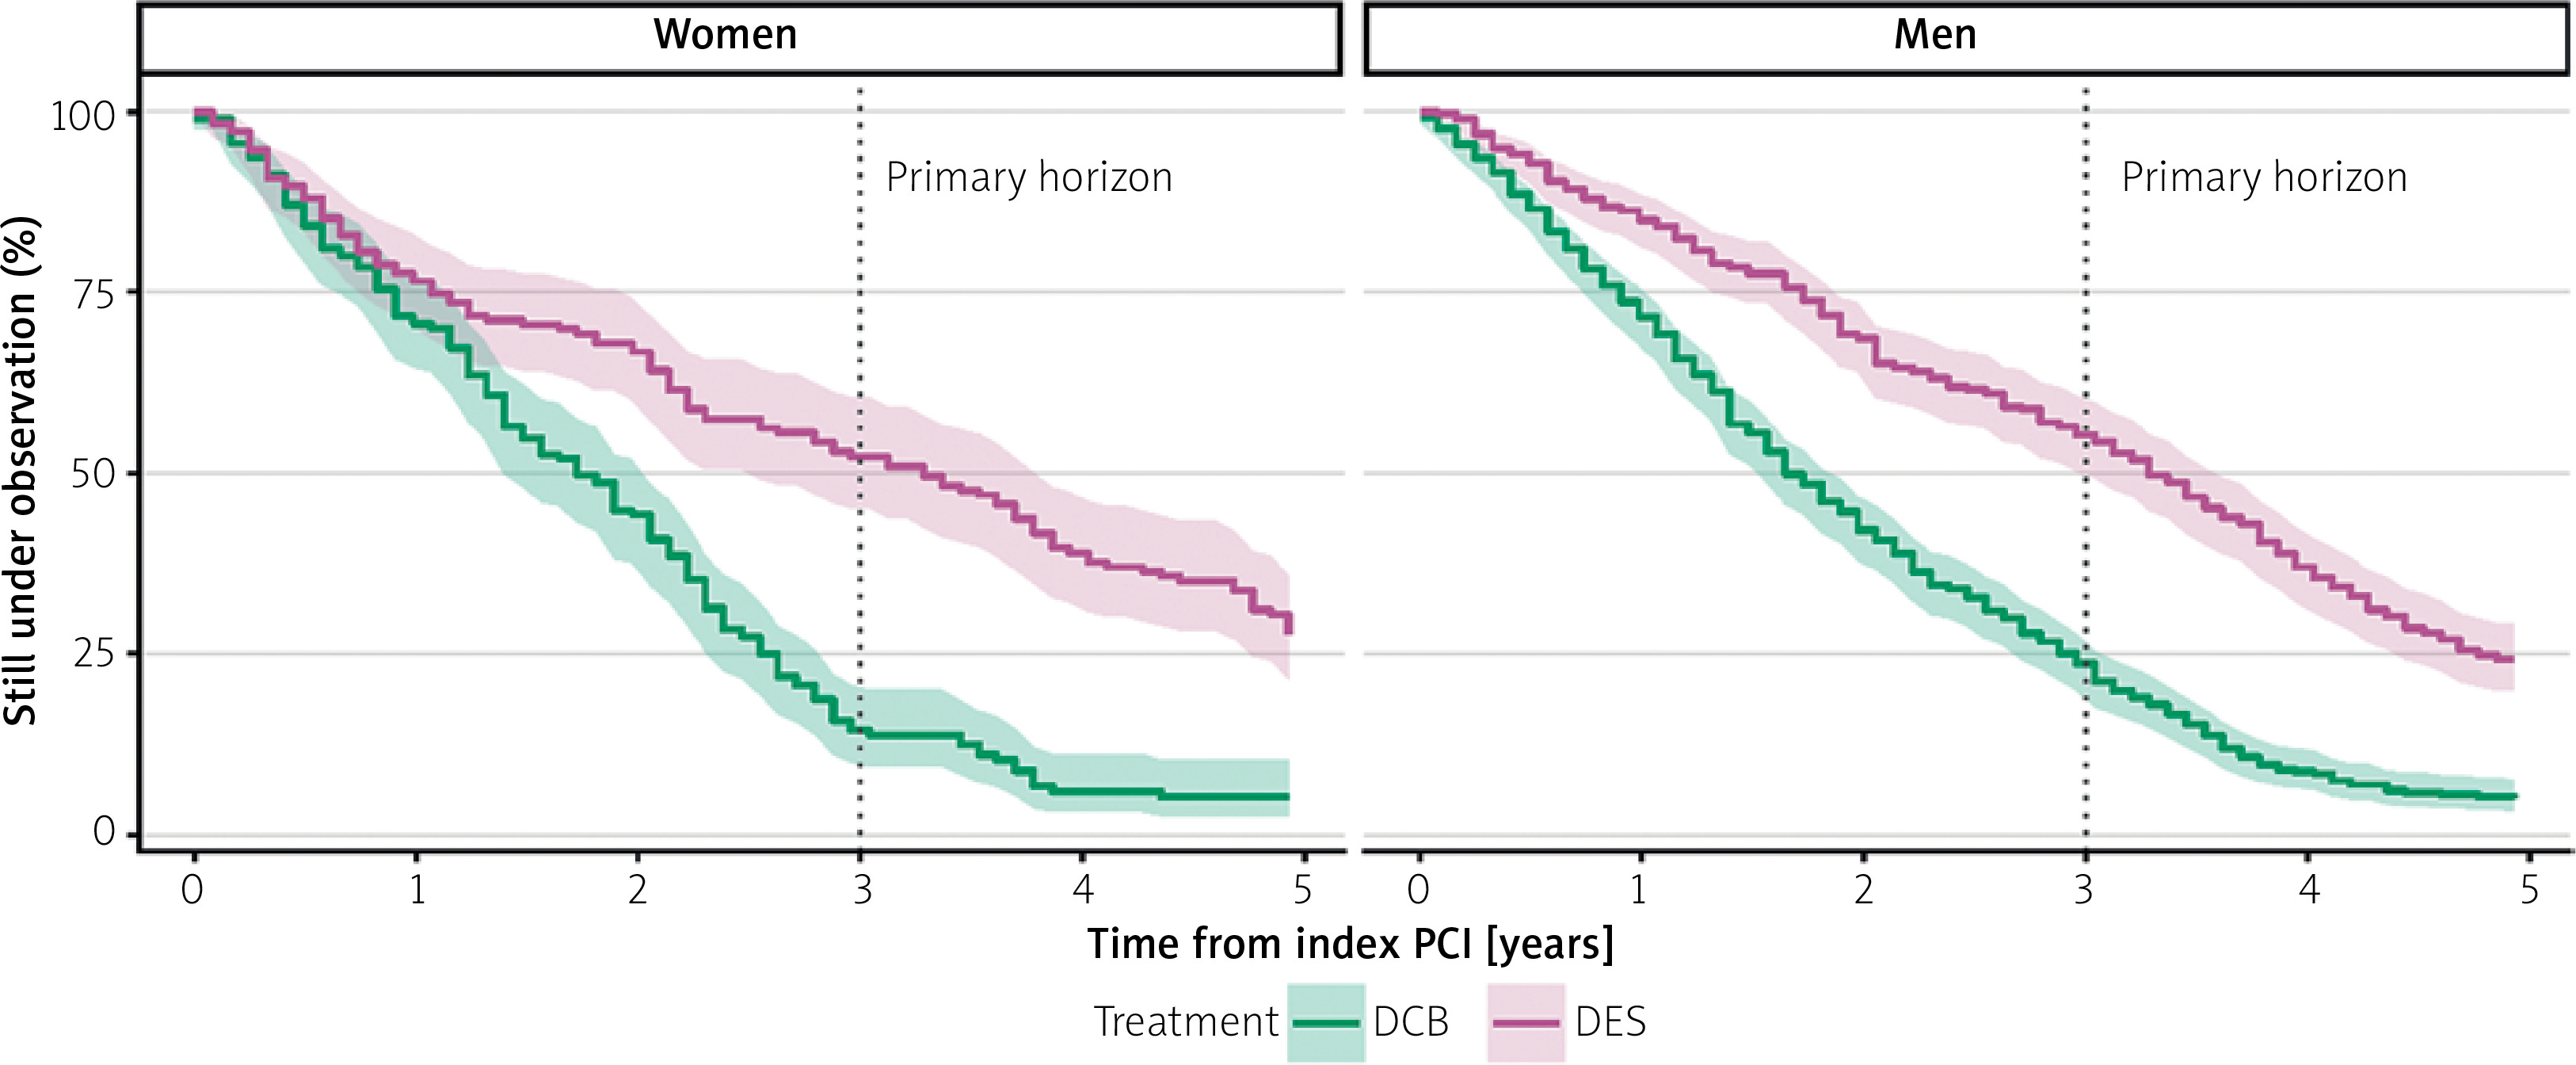
Figure 4
Weighted survival free from the device-oriented composite endpoint, by sex and treatment. Weighted Kaplan–Meier estimator of survival free from the device-oriented composite endpoint, with entropy-balancing weights targeting the average treatment effect within each sex stratum, pooled across 20 imputed datasets. No overlap-type weighting function is used. Counts beneath the curves are unweighted numbers remaining under observation. Each panel carries the weighted hazard ratio with its confidence interval and p-value from the weighted Cox model fitted to the same weighted sample, with robust variance; a conventional log-rank test is not reported because its nominal level is not preserved under balancing weights. The curves derive from the same weighted fit that produces the probabilities tabulated in Table II, so that figure and table agree by construction. The horizontal axis is labelled in years, whereas follow-up is reported in months in the text and tables
DCB – drug-coated balloon, DES – drug-eluting stent, DOCE – device-oriented composite endpoint, HR – hazard ratio, PCI – percutaneous coronary intervention.
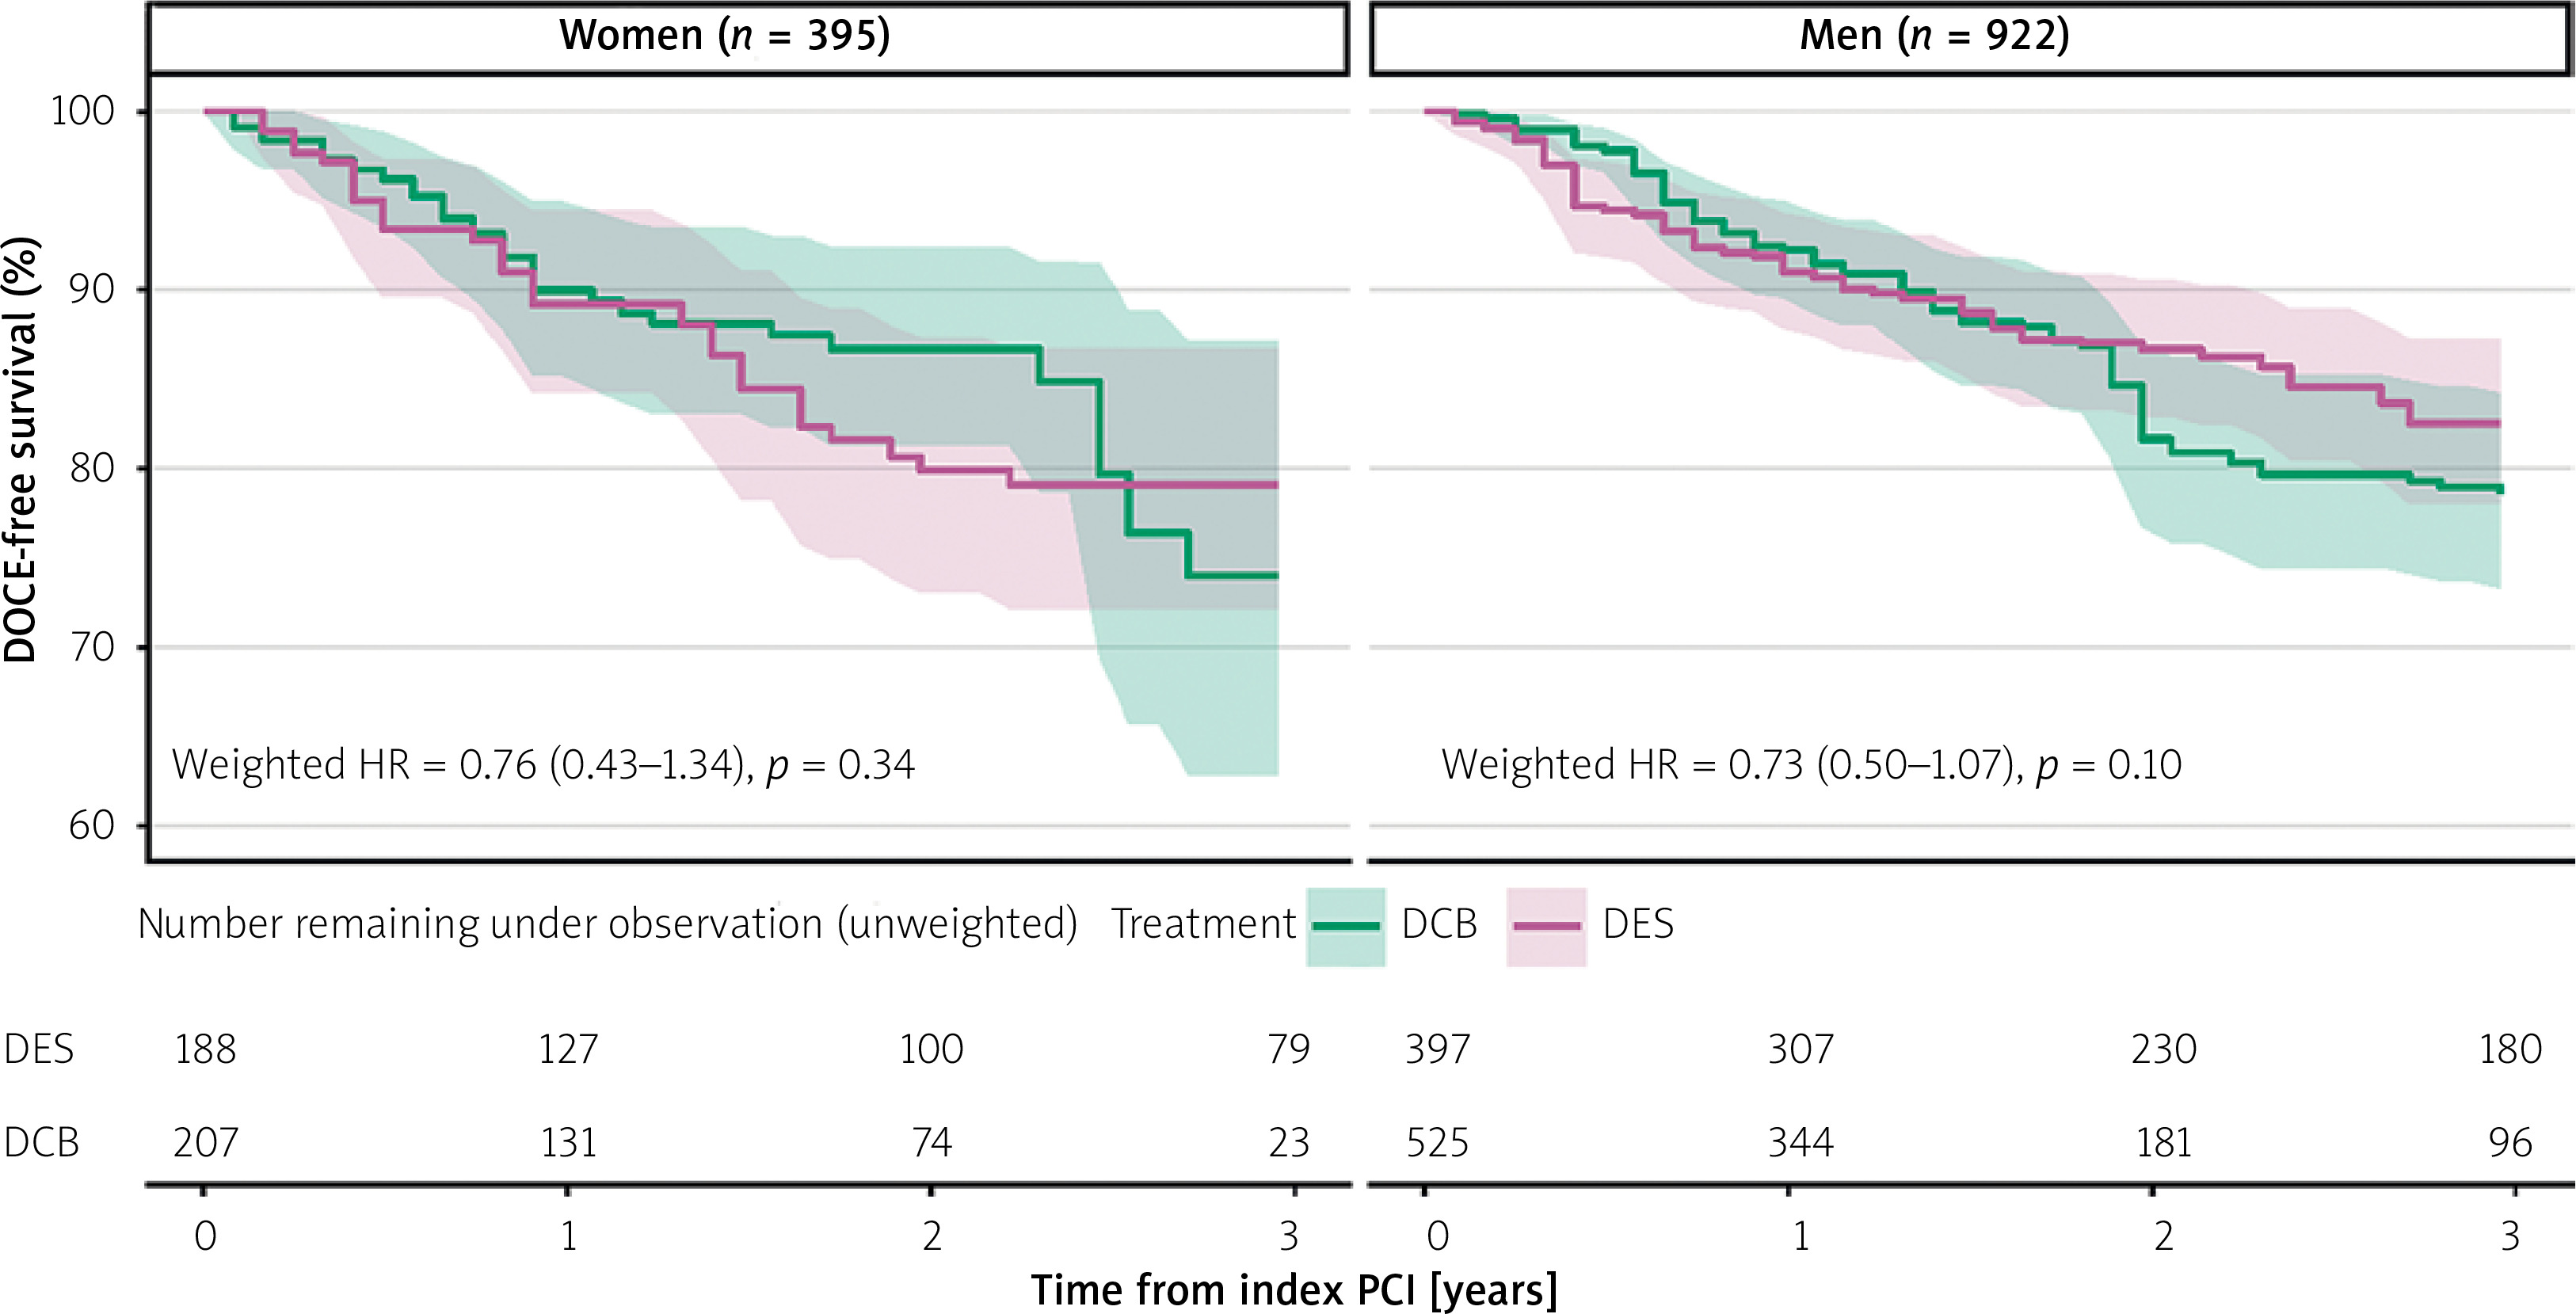
Figure 5
Sex-specific difference in restricted mean survival time for the primary endpoint. Forest plot of the sex-specific difference in restricted mean survival time over 0–3 years for the device-oriented composite endpoint, with the sex contrast shown in bold. Negative values favour the drug-eluting stent. Estimates derive from weighted Kaplan–Meier fits with entropy-balancing weights targeting the average treatment effect within each sex stratum; standard errors derive from nonparametric bootstrap with re-estimation of the weights within every resample, 40 resamples per imputed dataset, pooled across the 20 imputed datasets by Rubin’s rules; the sex contrast is formed under a normal approximation. The plot replaces the forest plot of 3-year risk differences presented in the original submission; the corresponding values are tabulated in Table IV. The horizontal axis is scaled in years
CI – confidence interval, DCB – drug-coated balloon, DES – drug-eluting stent, RMST – restricted mean survival time.
Secondary endpoints: component-level decomposition
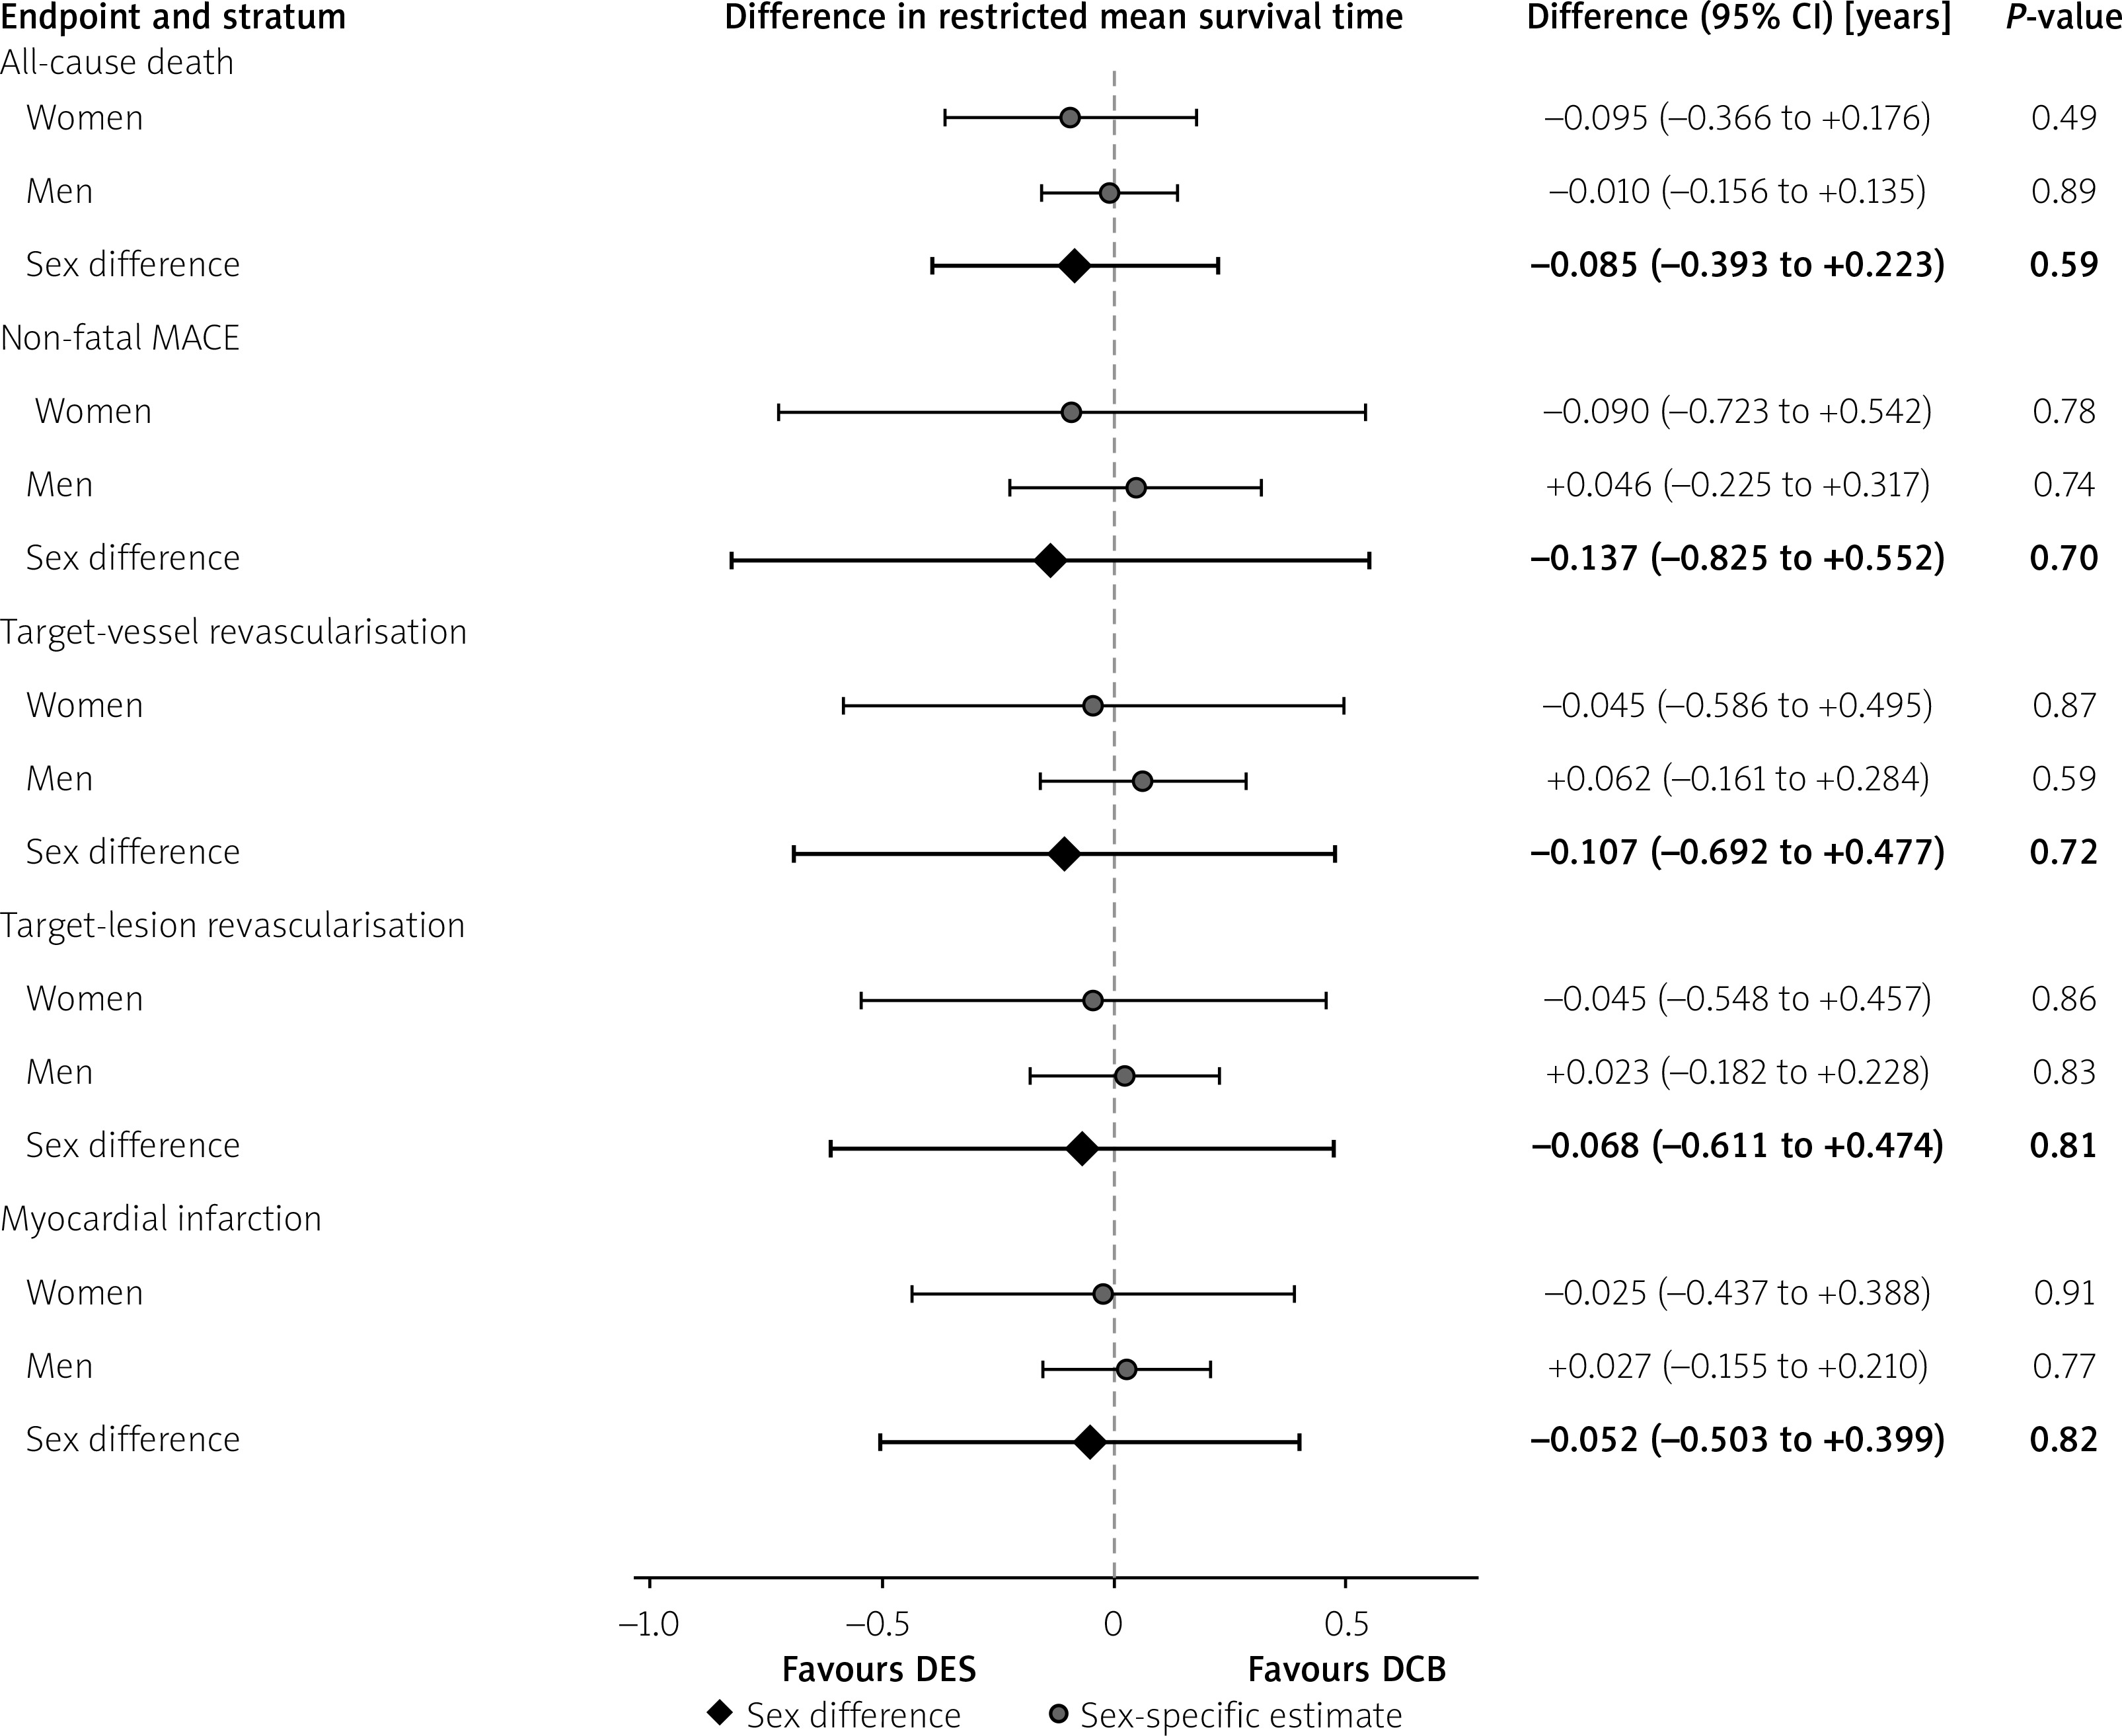
Disaggregation of the device-oriented composite into its clinically distinct components reveals no sex-related heterogeneity for any endpoint (Table V, Figure 6). The component-level signals reported in the original submission do not survive correction of the estimator; the counts and estimates below supersede them.
Table V
Sex-specific treatment effects across the primary endpoint and all secondary endpoints, expressed as differences in restricted mean survival time over the 3-year window
[i] Note. Values are differences in restricted mean survival time in years with 95% confidence intervals; negative values favour the drug-eluting stent. A feasibility screen excluded from inference any endpoint with fewer than ten events in any sex-by-treatment cell; cardiovascular death (minimum cell count 5) and target-vessel myocardial infarction (minimum cell count 9) are therefore reported descriptively only, as raw counts in Supplementary Table SVI. The P column reports uncorrected values for the sex contrast; false-discovery-rate correction follows the Benjamini–Hochberg procedure across the five estimable secondary endpoints, the primary endpoint being excluded from that family. No contrast approaches significance on either the raw or the corrected scale. FDR – false discovery rate, MACE – major adverse cardiac events, RMST – restricted mean survival time.
Figure 6
Sex-specific differences in restricted mean survival time for secondary endpoints. Forest plot of sex-specific differences in restricted mean survival time over 0–3 years for the five estimable secondary endpoints, with the sex contrast shown in bold for each endpoint. Negative values favour the drug-eluting stent. Estimation and interval construction are as in Figure 5. The p-values displayed are uncorrected; Benjamini–Hochberg false-discovery-rate correction across the five secondary contrasts yields an adjusted value of 0.82 for every endpoint and is reported in Table IV. Cardiovascular death (41 events; minimum cell count 5) and target-vessel myocardial infarction (61 events; minimum cell count 9) are omitted because they failed the pre-estimation feasibility screen and are reported descriptively only (Supplementary Tables SII and SVI)
CI – confidence interval, DCB – drug-coated balloon, DES – drug-eluting stent, MACE – major adverse cardiac events, RMST – restricted mean survival time.
All-cause mortality (110 events)
Deaths numbered 11 of 207 and 23 of 188 among women treated with a drug-coated balloon and a drug-eluting stent, respectively, and 36 of 525 and 40 of 397 among men. Cardiovascular deaths were similar between arms in both sexes (5 versus 5 in women; 16 versus 15 in men); the entire excess consisted of non-cardiovascular and unascertained deaths (Table VI). On the hazard scale, which is insensitive to the twofold difference in observation duration between arms, the weighted hazard ratio for death was 1.03 (95% CI: 0.39–2.72) in women and 0.78 (0.42–1.46) in men. The mortality difference reported in the original submission was an artefact of differential follow-up and was not observed after correction.
Table VI
Deaths by sex, treatment, cause and timing, with hazard-scale treatment effects
[i] Note. Cardiovascular deaths are identical between treatment arms in both sexes; the entire excess in the drug-eluting stent arm consists of non-cardiovascular and unascertained deaths, a pattern not predicted by a device-mediated mechanism. Cause of death was assigned by the local investigator from source documentation without central adjudication, which bears on the high proportion of unascertained causes. Hazard ratios derive from weighted Cox models with robust variance and are insensitive to the twofold difference in observation duration between arms; the unadjusted cause-specific hazard ratios for all-cause death are 0.93 (95% CI: 0.43–2.02) in women and 0.73 (0.45–1.18) in men. Cardiovascular death was not estimable under the feasibility screen, and the counts in the third column are descriptive only. CI – confidence interval, HR – hazard ratio.
Non-fatal MACE (300 events)
Crude counts favour the drug-coated balloon in both sexes: non-fatal MACE occurred in 44 of 207 women treated with a drug-coated balloon (21.3%) versus 55 of 188 treated with a drug-eluting stent (29.3%), and in 108 of 525 men (20.6%) versus 93 of 397 (23.4%). After accounting for the differential follow-up, the ordering reverses, with weighted 3-year risks of 29.6% versus 31.8% in women and 23.3% versus 29.5% in men. Neither the crude nor the adjusted comparison approaches reached significance, and the sex difference in restricted mean survival time was –0.137 years (–0.825 to +0.552; p = 0.70). The direction of the non-fatal MACE effect cannot be established from these data. Raw event counts for every component, by sex and treatment, are given in Supplementary Table SVI.
Target-vessel revascularisation (218 events)
Target-vessel revascularisation showed no sex-related heterogeneity after correction: the difference in restricted mean survival time was –0.045 years (95% CI: –0.586 to +0.495) in women and +0.062 years (–0.161 to +0.284) in men, giving a sex difference of –0.107 years (−0.692 to +0.477; p = 0.72). Weighted hazard ratios were 0.79 (0.45–1.39) and 0.66 (0.45–0.97) respectively; the latter is one comparison among twelve and does not remain statistically significant after correction for multiplicity.
After correction, no endpoint shows sex-related heterogeneity. Differences in restricted mean survival time for the sex contrast were −0.085 years for all-cause death, –0.137 for non-fatal MACE, –0.107 for target-vessel revascularisation, –0.068 for target-lesion revascularisation and –0.052 for myocardial infarction, with all raw p-values above 0.5 and all false-discovery-rate-adjusted values equal to 0.82 (Table V, Figure 6). Cardiovascular death and target-vessel myocardial infarction were non-estimable under the feasibility screen and are reported descriptively only.
Sensitivity analyses
Sensitivity analyses were consistent with the principal result. Unadjusted Fine–Gray regression gave sub-distribution hazard ratios for non-fatal MACE of 0.96 (95% CI: 0.63–1.45) in women and 0.78 (0.58–1.04) in men, with 3-year cumulative incidence of 29.2% versus 28.0% and 21.5% versus 27.0% respectively, and near-identical competing mortality (Supplementary Table SVII); being unadjusted, these estimates differ from the principal analysis in adjustment as well as in estimand. The risk-difference analyses showed no heterogeneity at either horizon, with intervals so wide as to be uninformative: –4.81 percentage points (95% CI: –34.64 to +25.02) in women and –4.15 (–17.31 to +9.01) in men at 3 years, versus +7.05 (–17.07 to +31.18) and –5.13 (–15.44 to +5.19) at 2 years, giving sex contrasts of –0.66 (–33.26 to +31.95) and +12.18 (–14.05 to +38.42). The sign of the female estimate reverses between the two horizons, which is a further consequence of the differential observation rather than a change of effect. A complete-case analysis did not alter any conclusion.
Discussion
This analysis of 1,317 patients treated for in-stent restenosis yields three findings. First, no sex-related heterogeneity of treatment effect is detectable for the device-oriented composite endpoint: the difference in restricted mean survival time between women and men was –0.083 years (95% CI: –0.661 to +0.495; p = 0.78), with weighted hazard ratios of 0.76 (0.43–1.34) and 0.73 (0.50–1.07) in the two strata. Second, the same null result holds for every estimable component, with all uncorrected p-values above 0.5 and every false-discovery-rate-adjusted value equal to 0.82. Third, the excess mortality among women treated with a drug-eluting stent reported in the original submission was no longer observed after correction: it appears to have resulted from a near-twofold difference in observation duration between the treatment arms, and on the hazard scale, which is less affected by differences in observation duration, the effect was not statistically significant.
The management of ISR remains challenging despite advances in contemporary PCI technology. Recent evidence increasingly supports DES implantation as the preferred strategy for many ISR scenarios, particularly following the 2024 ESC Chronic Coronary Syndromes Guidelines, which strengthened the position of DES in ISR management [14]. Nevertheless, DCB therapy remains an attractive option in selected patients, because it avoids implantation of an additional metallic layer and may reduce the burden of repeated stenting in complex restenotic lesions [30]. Large registry analyses from this research programme demonstrated broadly comparable long-term outcomes between DCB and thin-strut DES overall [8], while subsequent studies indicated that outcomes may differ according to lesion complexity, vessel size, recurrent restenosis patterns, stent design characteristics and device technology [12, 31–33]. These observations support the view that ISR treatment should be increasingly individualised rather than based solely on lesion-level characteristics.
A neutral composite endpoint invites the objection that opposing component-level effects may cancel within it. That objection does not apply here: after correction of the estimator, no component moves in a direction opposite to the composite, and the confidence interval for every component-level contrast comfortably spans zero. The methodological lesson of these data lies elsewhere. An augmented estimator whose correction term evaluates to zero for every patient effectively reduces to outcome-model standardisation: the balancing weights never enter the computation, and the quantity reported as a standard error measures the dispersion of predicted individual effects rather than the uncertainty of the estimate. In the original analysis, this underestimated the standard error approximately 25-fold and produced intervals the data do not support. Two diagnostics would have exposed the defect immediately: verification that the augmentation term is non-zero for at least some patients, and confirmation that the point estimate changes when the balancing weights are replaced by unit weights.
Mechanistic explanations for a sex-specific device effect can be offered but cannot be evaluated from these data. Women undergoing PCI more often exhibit smaller coronary vessel dimensions, a greater diffuse disease burden and altered vascular healing responses, so that an additional metallic layer might impose a disproportionate biological burden; conversely, a drug-coated balloon preserves vessel architecture while delivering antiproliferative therapy homogeneously to the vessel wall. Contemporary ISR studies report that outcomes worsen with increasing numbers of metallic layers and recurrent restenosis episodes [12, 31]. Emerging technologies such as the bioadaptor platform, which provides transient scaffolding with subsequent restoration of vascular adaptability, could modify this paradigm, although clinical experience remains limited and cost considerations could restrict widespread use [34]. Every statement in this paragraph is speculative: reference vessel diameter was not recorded, intracoronary imaging was not systematic, and the present analysis detected no sex-related difference that such mechanisms would be required to explain.
The mortality signal reported in the original submission warrants explicit dismissal rather than reinterpretation, and three lines of evidence indicate that it was an artefact of the original analysis. Cardiovascular deaths were similar between arms in both sexes, 5 versus 5 among women and 16 versus 15 among men, so that the entire excess in the drug-eluting stent arm consisted of non-cardiovascular and unascertained deaths – a pattern no device-mediated mechanism predicts. Median observation differed approximately twofold between arms, and a comparison of proportions at a fixed horizon reads that difference in observation as a difference in risk. On the hazard scale the weighted estimates were 1.03 (95% CI 0.39–2.72) in women and 0.78 (0.42–1.46) in men, and the unadjusted cause-specific hazard ratios were 0.93 (0.43–2.02) and 0.73 (0.45–1.18). The E-value analysis that accompanied the original mortality claim has been withdrawn, since the bound governs confounding of a single exposure–outcome association and does not transfer to a difference between two such associations; a robustness bound for a null finding would in any case convey nothing. Cause of death was assigned by the local investigator from source documentation without a central events committee, which bears directly on the high proportion of unascertained causes.
Contemporary ISR treatment algorithms are predominantly lesion-oriented, focusing on restenosis morphology, lesion preparation and the characteristics of the previously implanted device. Recent analyses from the same investigators demonstrated that treatment effects may vary according to clinical context, including recurrent restenosis, vessel calibre, stent architecture and the type of antiproliferative device used [32–34]. In a previous analysis of the EASTBOURNE prospective registry, which enrolled patients treated with a sirolimus-coated balloon, female patients showed a higher 2-year rate of MACE than male patients (24% vs 14%; p = 0.002), driven mainly by target-lesion revascularisation and myocardial infarction [35]. The present data do not extend that observation. Within a cohort of 1,317 patients, of whom 395 were women, and with 209 primary events, no contrast between the sexes approached significance on any scale. What these data establish is the absence of detectable heterogeneity, not the presence of equivalence.
Two constraints govern how far the present null result can be carried. The cohort provides 209 primary events, and the confidence interval for the sex contrast in restricted mean survival time spans –0.661 to +0.495 years, so that effects of clinical consequence remain compatible with these data. The differential follow-up further compounds this limitation, because it limits the interpretability of fixed-horizon absolute risk estimates as a reliable summary and confines the comparison to estimands that use the whole observed curve. Progress on sex differences in ISR treatment will therefore require prospective, balanced follow-up rather than larger retrospective series: additional patients observed for unequal periods do not remedy the problem identified here. These findings do not support a universal sex-based preference for either DCB or DES, and they underscore the value of sex-stratified, component-level outcome reporting in future ISR trials and registries.
Several limitations should be acknowledged. First, this was a non-randomised registry analysis, and residual confounding cannot be excluded. Body mass index was missing for 327 (24.8%) patients; a covariate absent in a quarter of the cohort contributes materially to residual confounding whatever the imputation model. Second, and most consequentially, follow-up was markedly differential between treatment arms, with median observation times of roughly 20 months under drug-coated balloon versus roughly 39 months under drug-eluting stent, and 57.6% of the cohort was censored before the 3-year horizon. Patients censored early carried a systematically worse risk profile, so that censoring is related to both treatment arm and prognosis; the independent-censoring assumption required to estimate fixed-horizon absolute risk cannot be sustained, which is why the primary estimand is the difference in restricted mean survival time. Third, centre identifiers were not available in the analytical export, so sensitivity to centre and calendar period could not be assessed. Fourth, cause of death was assigned by the local investigator without central adjudication. Fifth, reference vessel diameter was not recorded and intracoronary imaging was not systematic, so mechanistic explanations invoking vessel size or metallic burden are speculative. Sixth, recorded follow-up duration was missing for 49 (3.7%) patients. That field is used to reconcile implausible or absent event times against the observed observation period; for those 49 records the reconciliation could not be applied, so their event and censoring times rest on the registry entry alone. Seventh, the original submission reported estimates produced by a defective estimator; the present analysis supersedes those estimates. The full comparison of patients with and without known 3-year status is given in Supplementary Table SVIII.
Conclusions
Among patients undergoing PCI for in-stent restenosis, we found no evidence that sex modifies the comparative effectiveness of drug-coated balloons versus thin-strut drug-eluting stents. No sex-related heterogeneity was detectable for the primary endpoint or for any secondary endpoint, whether measured as a difference in restricted mean survival time, an absolute risk difference or a hazard ratio. These data do not support sex-based device selection. The analysis also illustrates two hazards for comparative-effectiveness work in registries: an estimator whose correction term is inoperative can produce apparent precision the data do not contain, and a difference in observation duration between arms can be read as a difference in risk when outcomes are compared at a fixed horizon.
Impact on daily practice
In patients undergoing PCI for coronary in-stent restenosis, the choice between a drug-coated balloon and repeat drug-eluting stent implantation is guided by lesion characteristics and procedural considerations. The present findings provide no support for sex-based device selection: no endpoint showed sex-related heterogeneity of treatment effect, and the direction of the non-fatal MACE effect cannot be established from these data. Device selection should therefore continue to rest on established procedural and lesion-related determinants – restenosis morphology, vessel size, the number of previously implanted metallic layers, lesion preparation strategy, bleeding risk and the anticipated duration of dual antiplatelet therapy – with sex carrying no independent weight on the present evidence.










