
Summary
This study evaluated the prognostic value of the triglyceride-glucose (TyG) index in 757 patients with ST-segment elevation myocardial infarction (STEMI) undergoing primary percutaneous coronary intervention. Patients with higher TyG levels had a significantly increased incidence of major adverse cardiovascular events (MACE) at 1 year. Multivariable analysis confirmed that a high TyG index was independently associated with MACE, alongside other established risk factors. Although the TyG index demonstrated statistically significant predictive value, its overall discriminatory performance was limited. These findings suggest that the TyG index may serve as a simple and accessible marker for risk stratification in STEMI patients.
Introduction
ST-elevation myocardial infarction (STEMI) remains a major cause of cardiovascular morbidity and mortality worldwide, despite substantial advances in reperfusion strategies and contemporary secondary prevention. Early risk stratification is therefore essential to guide clinical decision-making and improve outcomes in this high-risk population. In this context, insulin resistance (IR) has emerged as an important pathophysiological mechanism associated with atherosclerotic progression, plaque vulnerability, and adverse outcomes after myocardial infarction [1, 2].
Although the hyperinsulinaemic-euglycaemic clamp is considered the gold standard for the assessment of IR, its routine clinical use is limited by its complexity, cost, and poor feasibility in daily practice [3]. Similarly, alternative methods such as the Homeostasis Model Assessment of Insulin Resistance (HOMA-IR) are not always readily applicable, particularly in acute clinical settings. As a simple and accessible alternative, the triglyceride-glucose (TyG) index, derived from fasting triglyceride and glucose levels, has emerged as a practical and reproducible surrogate marker of IR [4, 5].
Growing evidence has shown that an elevated TyG index is associated with several cardiovascular diseases, including coronary artery calcification and arterial stiffness, and both the presence and severity of coronary artery disease [5, 6]. More importantly, the TyG index has also been linked to adverse cardiovascular outcomes in patients with acute coronary syndromes, including both non-ST-elevation myocardial infarction (NSTEMI) and STEMI [7–11]. In patients with STEMI, higher TyG index values have been associated with increased thrombus burden, impaired coronary microvascular perfusion, a greater likelihood of the no-reflow phenomenon, and ultimately less favourable clinical outcomes in STEMI populations [12–15].
Bilgin et al. demonstrated that the TyG index independently predicted mortality and thrombus burden in STEMI patients undergoing percutaneous coronary intervention (PCI), highlighting its potential prognostic relevance [12]. Likewise, Zhang et al. reported that higher TyG index values were associated with increased all-cause mortality, cardiovascular mortality, and repeat revascularisation in patients with acute myocardial infarction during long-term follow-up [9]. In addition, elevated TyG index has been associated with post-PCI physiological impairment, such as lower quantitative flow ratio (QFR), further supporting its possible role in post-infarction risk stratification [14].
Recent investigations have continued to evaluate novel biomarkers for risk stratification after STEMI. For example, circulating cardiomyocyte-specific cell-free DNA has been shown to predict subsequent heart failure risk following acute STEMI, highlighting the ongoing need for reliable prognostic markers in this population [15, 16].
Despite these findings, the prognostic significance of the TyG index for major adverse cardiovascular events (MACE) in STEMI patients undergoing primary PCI has not been fully clarified, particularly in real-world clinical cohorts. In addition, whether the TyG index provides prognostic information beyond conventional cardiovascular risk factors and angiographic characteristics remains an area of ongoing interest.
Aim
The present study aimed to evaluate the prognostic value of the TyG index for predicting 1-year MACE in patients with STEMI undergoing primary PCI.
Material and methods
Study population
This study was conducted as a retrospective, two-centre observational cohort study to evaluate the prognostic value of the TyG index over a 1-year follow-up in patients presenting with STEMI who underwent primary PCI. All consecutive patients admitted to the coronary care units of two tertiary cardiovascular centres between January 2019 and December 2023 were screened for eligibility. Both centres are high-volume PCI facilities with 24/7 primary PCI capability and standardised post-PCI follow-up protocols, supporting consistency of management across study sites. The diagnosis of STEMI was established according to contemporary European Society of Cardiology guideline criteria for acute coronary syndromes with ST-segment elevation [17].
The selection of the study population followed predefined inclusion and exclusion criteria to ensure data reliability and minimise potential confounding factors affecting TyG index measurement or cardiovascular outcomes. Inclusion criteria were as follows: patients aged ≥ 18 years, symptom onset ≤ 12 h prior to first medical contact, a confirmed diagnosis of STEMI based on the above ESC criteria, and those who underwent successful primary PCI during the index hospitalisation. Only patients with available fasting laboratory measurements of triglycerides and glucose obtained after overnight fasting within the first 24 h of admission were considered eligible, as these values were required for TyG index calculation.
Patients were excluded if they had conditions that could substantially influence the TyG index or interfere with outcome assessment, including cardiogenic shock on admission, the need for mechanical circulatory support (intra-aortic balloon pump or extracorporeal membrane oxygenation), prior coronary artery bypass grafting (CABG), recent PCI within 30 days, severe valvular heart disease, active systemic infection, autoimmune disease, haematological disorder, malignancy, or severe renal (estimated glomerular filtration rate [eGFR] < 30 ml/min/1.73 m²) or hepatic dysfunction. Patients with incomplete clinical or angiographic data or those lost to follow-up were also excluded. After applying these criteria, a total of 757 patients were included in the final analysis.
Clinical and laboratory data collection
Baseline demographic and clinical data, including age, sex, cardiovascular risk factors (hypertension, diabetes mellitus, dyslipidaemia, and smoking status), and past medical history, were retrieved from the electronic medical record systems of the participating centres.
Laboratory testing was performed on fasting blood samples obtained within the first 24 h of hospital admission. Measurements included fasting plasma glucose, triglycerides, total cholesterol, high-density lipoprotein cholesterol (HDL-C), low-density lipoprotein cholesterol (LDL-C), serum creatinine, and cardiac biomarkers (troponin I/T and creatine kinase-MB [CK-MB]).
The TyG index, a validated surrogate marker of insulin resistance, was calculated using the following formula: TyG index = ln [fasting triglycerides (mg/dl) × fasting plasma glucose (mg/dl)/2] [18, 19].
For analytical purposes, the TyG index was evaluated both as a continuous variable and as a categorical variable. To facilitate internal risk stratification and between-group comparisons, patients were dichotomised according to the median TyG index value of the study population (9.24). Patients with TyG index values below the median were classified as the low TyG group, whereas those with values equal to or above the median were classified as the high TyG group. This median-based categorisation was preferred to avoid the use of arbitrary threshold values and to provide a balanced internal comparison within the study cohort. Similar categorisation strategies have been used in previous cardiovascular studies evaluating the prognostic significance of the TyG index over follow-up [20, 21].
Echocardiographic and angiographic data were also collected, including left ventricular ejection fraction (LVEF), number of diseased vessels, TIMI flow grade before and after PCI, and the presence of multivessel disease, defined as ≥ 50% diameter stenosis in at least two major epicardial coronary arteries. The no-reflow phenomenon was defined as post-PCI TIMI flow ≤ 2 despite successful epicardial artery opening.
Follow-up and study endpoints
Follow-up data and MACE were obtained from hospital medical records and structured telephone interviews. All patients were followed for 1 year after the index hospitalisation. The primary outcome of the study was the occurrence of MACE during 1-year follow-up, defined as a composite of cardiovascular-related hospitalisation, stroke, non-fatal myocardial infarction, and all-cause mortality.
This study was conducted in accordance with the principles of the Declaration of Helsinki and was approved by the Ethics Committee of one of the participating centres. Owing to the retrospective design of the study, the requirement for written informed consent was waived.
Statistical analysis
Continuous variables were assessed for normality using the Kolmogorov–Smirnov and Shapiro–Wilk tests. Normally distributed variables are presented as mean and standard deviation (SD), whereas non-normally distributed variables are expressed as median with interquartile range (IQR). Categorical variables are presented as counts and percentages. Between-group comparisons were performed using the independent samples t-test or the Mann–Whitney U test for continuous variables, as appropriate, and the χ2 test or Fisher’s exact test for categorical variables. In accordance with editorial guidelines, all calculated p-values greater than 0.05 have been rounded to exactly two decimal places, whereas values less than or equal to 0.05 retain three-decimal precision.
The triglyceride-glucose index was calculated using the established formula: ln [fasting triglycerides (mg/dl) × fasting plasma glucose (mg/dl)/2]. Patients were stratified into two groups according to the median TyG index value of the study cohort (9.24), defined as the low-TyG group (TyG < 9.24) and the high-TyG group (TyG ≥ 9.24).
The association between the TyG index and MACE was initially evaluated using univariable logistic regression analysis. Variables demonstrating a p-value < 0.05 in univariable analysis, along with clinically relevant covariates, were subsequently entered into multivariable logistic regression models. Two sequential multivariable models were constructed. Model 1 included age, sex, hypertension, diabetes mellitus, multivessel disease, and LDL cholesterol. Model 2 included all variables from Model 1 with the addition of the TyG index group (high vs. low).
Regression analyses were performed using a complete-case approach. Due to missing data on LDL cholesterol or multivessel disease, 120 patients were excluded, resulting in a final analytic sample of 637 patients for both models. To assess potential selection bias, baseline demographic and metabolic characteristics were compared between the 637 included patients and the 120 excluded patients, and no significant differences were observed. Model calibration was assessed using the Hosmer–Lemeshow goodness-of-fit test, and model explanatory performance was evaluated using the Nagelkerke R² statistic. We acknowledge that logistic regression evaluates fixed follow-up outcomes without accounting for precise time-to-event information, which represents a limitation inherent to the retrospective design of the study.
The discriminative ability of the TyG index for predicting MACE was further assessed using receiver operating characteristic (ROC) curve analysis. The area under the curve (AUC) was calculated and compared against the null hypothesis of AUC = 0.50 using the DeLong method. The optimal cut-off value was determined using the Youden index (sensitivity + specificity – 1).
The median-based grouping threshold (TyG ≥ 9.24) and the ROC-derived cut-off value (9.38) were used for different analytical purposes and were not expected to coincide. The median value was used for internal cohort stratification, whereas the ROC-derived threshold was used to evaluate discriminative performance.
Sensitivity, specificity, positive predictive value, negative predictive value, and likelihood ratios were calculated at the optimal cut-off value.
All statistical analyses were performed using IBM SPSS Statistics, version 23.0 (IBM Corp., Armonk, NY, USA). A two-sided p-value < 0.05 was considered statistically significant.
Results
Baseline characteristics
A total of 757 patients were included in the final analysis and stratified into two groups according to the median TyG index value of the study cohort (9.24). Of these, 379 patients were classified into the low-TyG group and 378 into the high-TyG group.
Baseline characteristics of the study population are presented in Table I. Patients in the high-TyG group had a greater prevalence of hypertension (51.9% vs. 43.8%, p = 0.021) and diabetes mellitus (40.7% vs. 30.3%, p = 0.001). Male sex was more frequent in the low-TyG group (79.4% vs. 73.5%, p = 0.04).
Table I
Baseline characteristics by TyG index group
| Parameter | Low TyG (n = 379) | High TyG (n = 378) | P-value |
|---|---|---|---|
| Demographics | |||
| Age [years] | 64.2 ±10.9 | 63.5 ±10.8 | 0.36 |
| Male sex, n (%) | 301 (79.4) | 278 (73.5) | 0.040 |
| Risk factors, n (%) | |||
| Smoking | 195 (51.5) | 199 (52.6) | 0.74 |
| Hypertension | 166 (43.8) | 196 (51.9) | 0.021 |
| Diabetes mellitus | 115 (30.3) | 154 (40.7) | 0.001 |
| Prior CAD history | 94 (24.8) | 89 (23.5) | 0.65 |
| Heart failure | 26 (6.9) | 29 (7.7) | 0.67 |
| Atrial fibrillation | 6 (1.6) | 7 (1.9) | 0.80 |
| Complete blood count | |||
| WBC [× 10³/µl] | 10.90 (8.50–11.50) | 10.94 (9.00–13.50) | 0.025 |
| Haemoglobin [g/dl] | 13.00 (11.40–14.90) | 14.10 (12.57–15.55) | < 0.001 |
| Platelets [× 10³/µl] | 242 (161–315) | 242 (194–299) | 0.32 |
| Neutrophils [× 10³/µl] | 6.64 (5.89–8.72) | 6.88 (5.53–9.85) | 0.48 |
| Biochemistry | |||
| Creatinine [mg/dl] | 0.99 (0.84–1.40) | 1.37 (0.91–1.54) | < 0.001 |
| Glucose [mg/dl] | 96 (88–111) | 164 (132–239) | < 0.001 |
| Sodium [mEq/l] | 136 (134–138) | 137 (135–139) | 0.002 |
| Potassium [mEq/l] | 4.40 (4.10–4.50) | 4.30 (4.00–4.50) | 0.08 |
| AST [U/l] | 35 (19–43) | 25 (19–43) | 0.25 |
| ALT [U/l] | 24 (15–38) | 21 (15–32) | 0.06 |
| Albumin [g/l] | 40.6 ±3.8 | 39.9 ±4.3 | 0.017 |
| Lipid profile [mg/dl] | |||
| LDL-C | 91 (84–130) | 112 (89–141) | < 0.001 |
| Total cholesterol | 142 (112–187) | 175 (134–204) | < 0.001 |
| Triglycerides | 154 (149–167) | 172 (152–240) | < 0.001 |
| HDL-C | 42.1 ±7.1 | 40.9 ±7.9 | 0.044 |
| Cardiac enzymes | |||
| Initial troponin [ng/l] | 71.5 (22.0–1515.6) | 145.0 (31.6–2459.0) | 0.004 |
| Angiographic & procedural findings, n (%)a | |||
| Multivessel disease | 187 (60.1) | 171 (50.0) | 0.005 |
| No-reflow phenomenon | 41 (14.1) | 21 (8.5) | 0.039 |
| Outcomes, n (%) | |||
| MACE | 121 (31.9) | 158 (41.8) | 0.003 |
| All-cause mortality | 33 (8.7) | 34 (9.0) | 0.88 |
| Non-fatal myocardial infarction | 22 (5.8) | 31 (8.2) | 0.20 |
| Stroke | 8 (2.1) | 11 (2.9) | 0.48 |
| Cardiovascular hospitalisation | 58 (15.3) | 82 (21.7) | 0.023 |
a Angiographic variables were analysed on an available-case basis. Data on no-reflow were available for 538 patients, and data on multivessel disease were available for 653 patients; percentages were calculated using the number of patients with available data in each TyG group as the denominator. ALT – alanine aminotransferase, AST – aspartate aminotransferase, CAD – coronary artery disease, HDL-C – high-density lipoprotein cholesterol, IQR – interquartile range, LDL-C – low-density lipoprotein cholesterol, MACE – major adverse cardiovascular events, TyG – Triglyceride-Glucose Index, WBC – white blood cell count.
With respect to laboratory parameters, patients in the high-TyG group demonstrated higher white blood cell counts (10.94 [9.00–13.50] vs. 10.90 [8.50–11.50], p = 0.02), haemoglobin levels (14.10 [12.57–15.55] vs. 13.00 [11.40–14.90], p < 0.001), serum creatinine levels (1.37 [0.91–1.54] vs. 0.99 [0.84–1.40], p < 0.001), glucose levels (164 [132–239] vs. 96 [88–111], p < 0.001), and lipid parameters including LDL cholesterol (112 [89–141] vs. 91 [84–130], p < 0.001) and triglycerides (172 [152–240] vs. 154 [149–167], p < 0.001). Serum albumin levels were slightly lower in the high-TyG group (39.9 ±4.3 vs. 40.6 ±3.8, p = 0.017).
In terms of angiographic findings, multivessel disease (60.1% vs. 50.0%, p = 0.005) and no-reflow phenomenon (14.1% vs. 8.5%, p = 0.03) were more frequently observed in the low-TyG group. We note this finding early because the higher anatomical disease burden and no-reflow frequency observed in the low-TyG group appear counterintuitive and are further discussed in the Discussion section.
Clinical outcomes
During a 1-year follow-up, MACE occurred in 279 (36.8%) patients. The incidence of MACE was significantly greater in the high-TyG group compared with the low-TyG group (41.8% vs. 31.9%, p = 0.003) (Table I). When evaluating individual composite components, cardiovascular hospitalisations occurred in 58 (15.3%) low-TyG vs. 82 (21.7%) high-TyG patients; strokes occurred in 8 (2.1%) low-TyG vs. 11 (2.9%) high-TyG patients; non-fatal myocardial infarctions were tracked in 22 (5.8%) low-TyG vs. 31 (8.2%) high-TyG patients; and all-cause mortality claimed 33 (8.7%) low-TyG vs. 34 (9.0%) high-TyG patients.
Notably, the difference in overall MACE incidence between groups appeared to be driven primarily by cardiovascular hospitalisations, whereas all-cause mortality, non-fatal myocardial infarction, and stroke did not differ significantly between the groups.
Univariable logistic regression analysis
Univariable logistic regression analysis identified several variables associated with MACE (Table II). Increasing age was associated with higher odds of MACE (OR = 1.017, 95% CI: 1.004–1.032, p = 0.013), as was male sex (OR = 1.559, 95% CI: 1.108–2.193, p = 0.011). Multivessel disease was also significantly associated with MACE (OR = 1.411, 95% CI: 1.025–1.944, p = 0.03), as was LDL cholesterol (OR = 1.006, 95% CI: 1.001–1.010, p = 0.01).
Table II
Univariable logistic regression analysis for predictors of MACE
| Parameter | OR (95% CI) | P-value |
|---|---|---|
| Age [years] | 1.017 (1.004–1.032) | 0.013 |
| Male sex | 1.559 (1.108–2.193) | 0.011 |
| Smoking | 1.065 (0.793–1.432) | 0.67 |
| Hypertension | 1.301 (0.968–1.750) | 0.08 |
| Diabetes mellitus | 1.338 (0.985–1.818) | 0.06 |
| Coronary artery disease | 1.082 (0.768–1.525) | 0.65 |
| Multivessel diseasea | 1.411 (1.025–1.944) | 0.035 |
| Heart rate [bpm] | 1.003 (0.994–1.011) | 0.57 |
| LDL cholesterola | 1.006 (1.001–1.010) | 0.011 |
| TyG index (high vs. low) | 1.531 (1.137–2.062) | 0.005 |
a Multivessel disease analysis includes 653 (86.3%) patients due to missing angiographic data. LDL cholesterol analysis includes 733 (96.8%) patients due to missing values. CI – confidence interval, LDL – low-density lipoprotein, MACE – major adverse cardiovascular events, OR – odds ratio, TyG – triglyceride-glucose index.
Importantly, the high-TyG group was associated with a significantly increased risk of MACE compared with the low-TyG group (OR = 1.531, 95% CI: 1.137–2.062, p = 0.005).
Multivariable logistic regression analysis
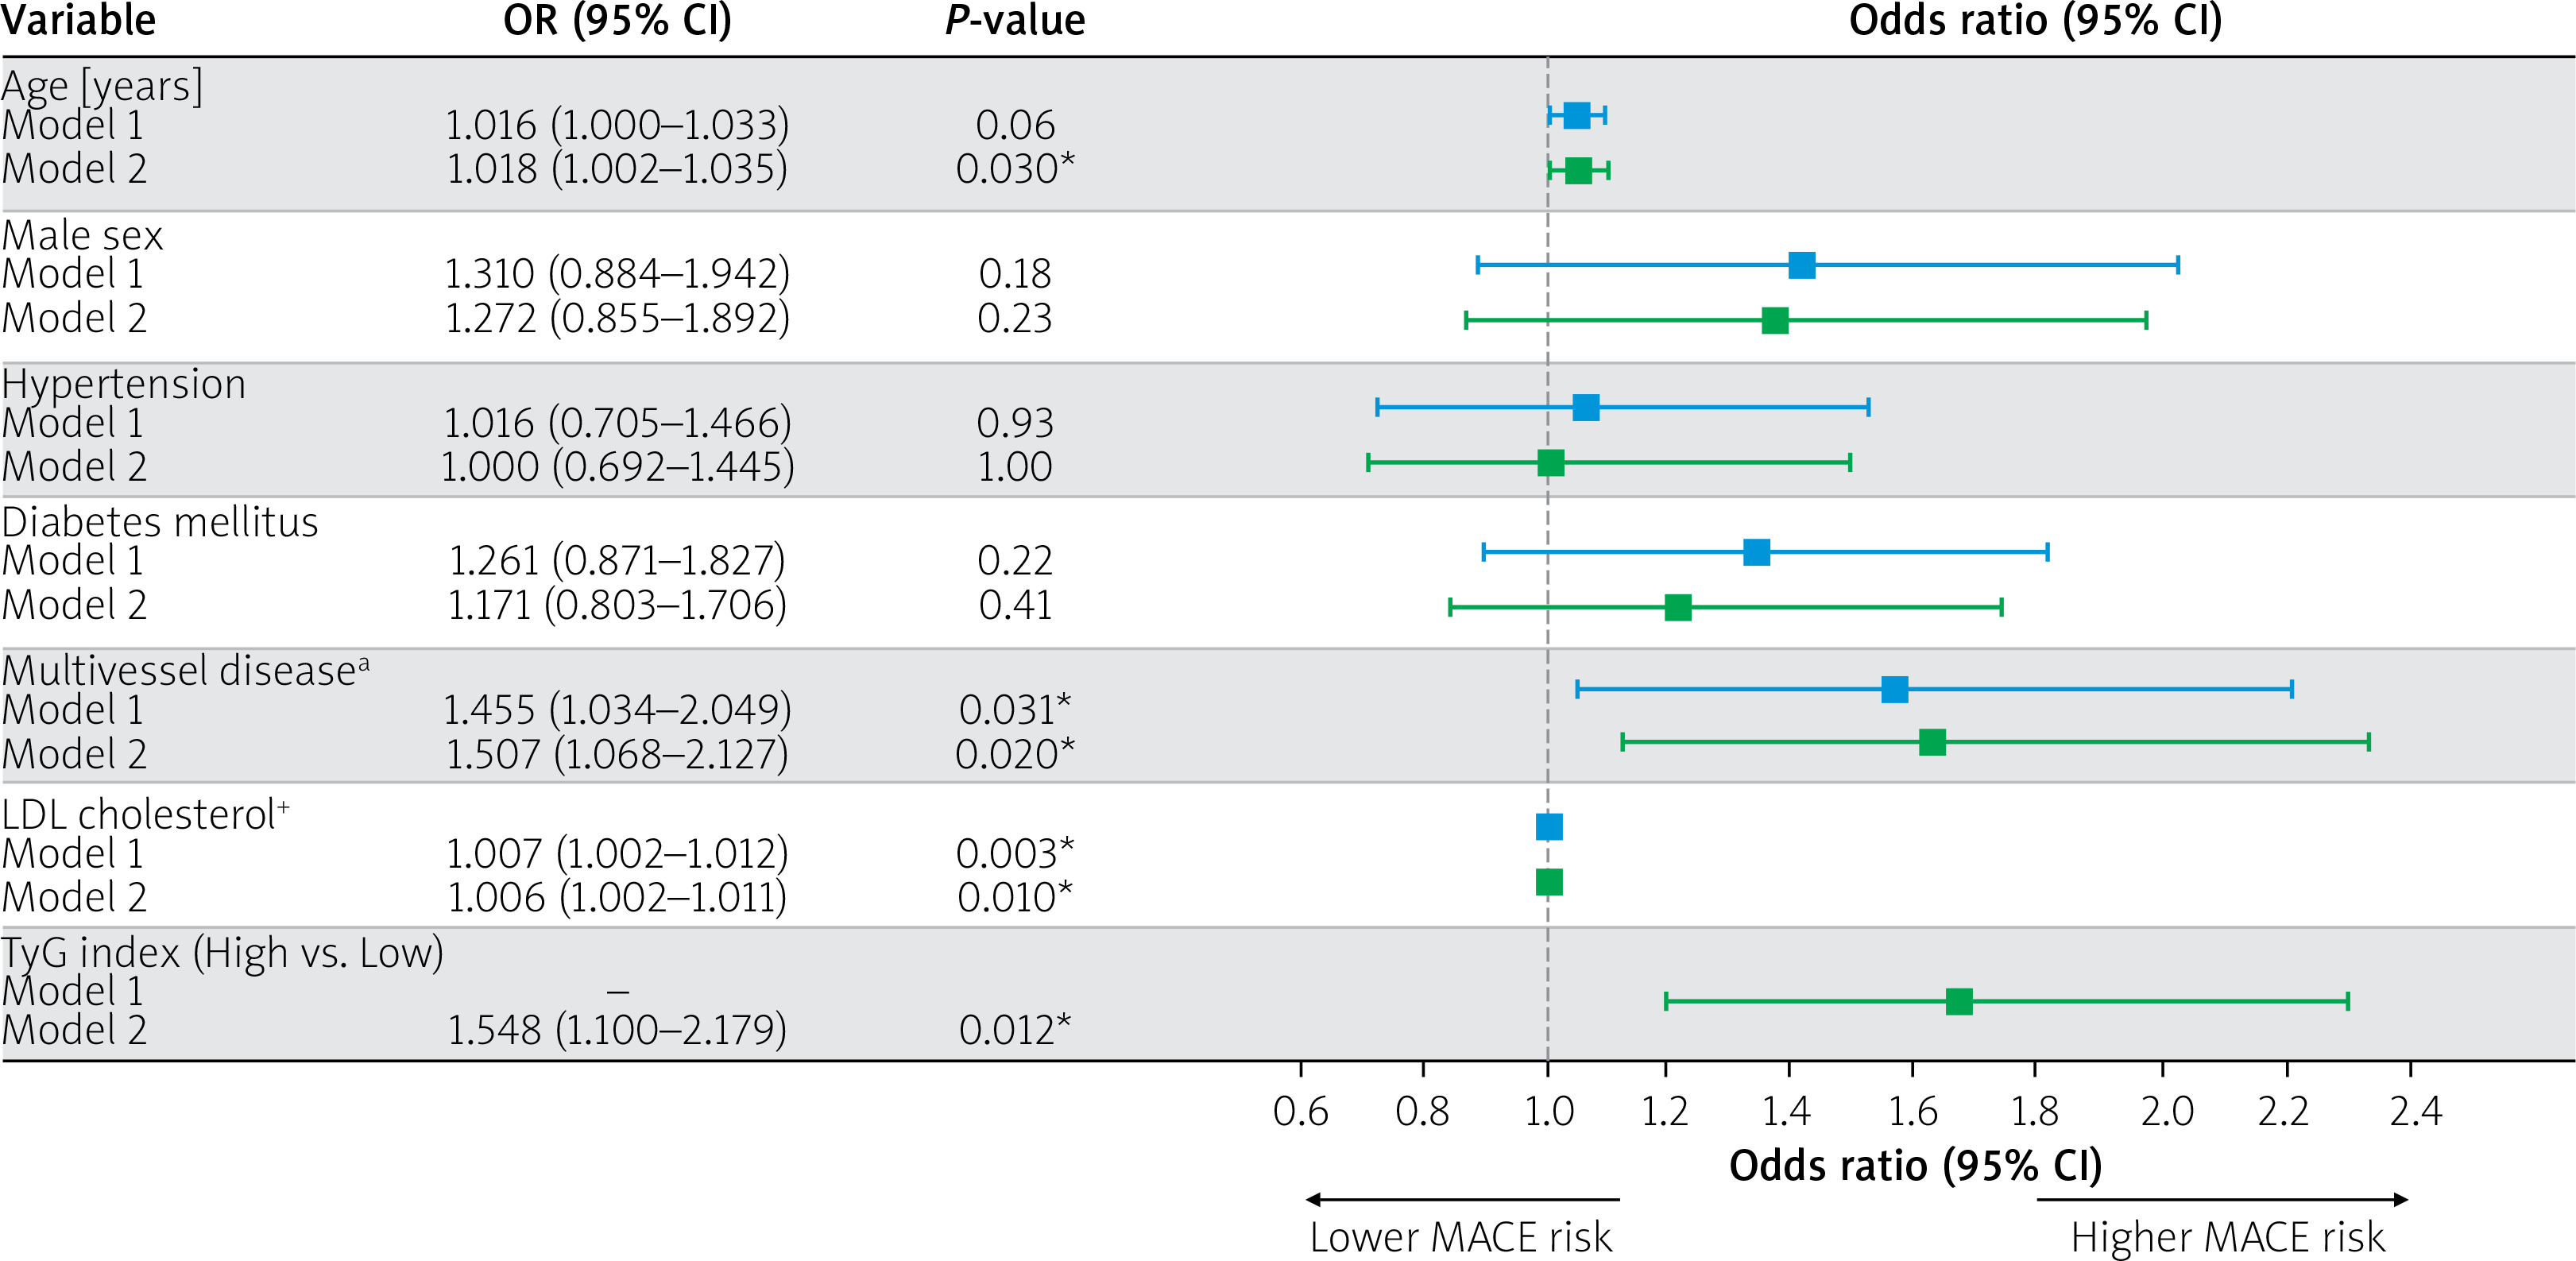
Multivariable logistic regression models are presented in Table III. In Model 1, which included age, sex, hypertension, diabetes mellitus, multivessel disease, and LDL cholesterol, multivessel disease (OR = 1.455, 95% CI: 1.034–2.048, p = 0.03) and LDL cholesterol (OR = 1.007, 95% CI: 1.002–1.012, p = 0.003) were independently associated with MACE.
Table III
Multivariable logistic regression analysis for predictors of MACE
| Parameter | Model 1 | Model 2 | ||
|---|---|---|---|---|
| OR (95% CI) | P-value | OR (95% CI) | P-value | |
| Age [years] | 1.016 (1.000–1.033) | 0.06 | 1.018 (1.002–1.035) | 0.030 |
| Male sex | 1.310 (0.884–1.942) | 0.18 | 1.272 (0.855–1.892) | 0.23 |
| Hypertension | 1.016 (0.705–1.466) | 0.93 | 1.000 (0.692–1.445) | 0.99 |
| Diabetes mellitus | 1.261 (0.871–1.827) | 0.22 | 1.171 (0.803–1.706) | 0.41 |
| Multivessel diseasea | 1.455 (1.034–2.048) | 0.031 | 1.507 (1.068–2.127) | 0.020 |
| LDL cholesterola | 1.007 (1.002–1.012) | 0.003 | 1.006 (1.002–1.011) | 0.010 |
| TyG index (high vs. low) | — | — | 1.548 (1.100–2.179) | 0.012 |
| n (analysed) | 637 | 637 | ||
| –2 Log likelihood | 821.427 | 815.085 | ||
| Nagelkerke R² | 0.051 | 0.064 | ||
| Hosmer-Lemeshow p | 0.85 | 0.71 | ||
In Model 2, which additionally included the TyG index group, the high-TyG group remained independently associated with an increased risk of MACE (OR = 1.548, 95% CI: 1.100–2.179, p = 0.012). Multivessel disease (OR = 1.507, 95% CI: 1.068–2.127, p = 0.02) and LDL cholesterol (OR = 1.006, 95% CI: 1.002–1.011, p = 0.010) also remained significant predictors. Age was also independently associated with MACE in Model 2 (OR = 1.018, 95% CI: 1.002–1.035, p = 0.03).
Model performance showed a modest improvement with the inclusion of the TyG index (Nagelkerke R² increased from 0.051 to 0.064), while model calibration remained acceptable (Hosmer–Lemeshow p = 0.85 for Model 1 and p = 0.71 for Model 2) (Figure 1).
Receiver operating characteristic (ROC) analysis
Receiver operating characteristic (ROC) curve analysis demonstrated that the TyG index had a statistically significant but modest ability to discriminate major adverse cardiovascular events (MACE) (AUC = 0.573, 95% CI: 0.532–0.615, p = 0.001) (Figure 2). The optimal TyG cut-off value identified by the Youden index was 9.38, corresponding to a sensitivity of 58.4% and a specificity of 56.1%.
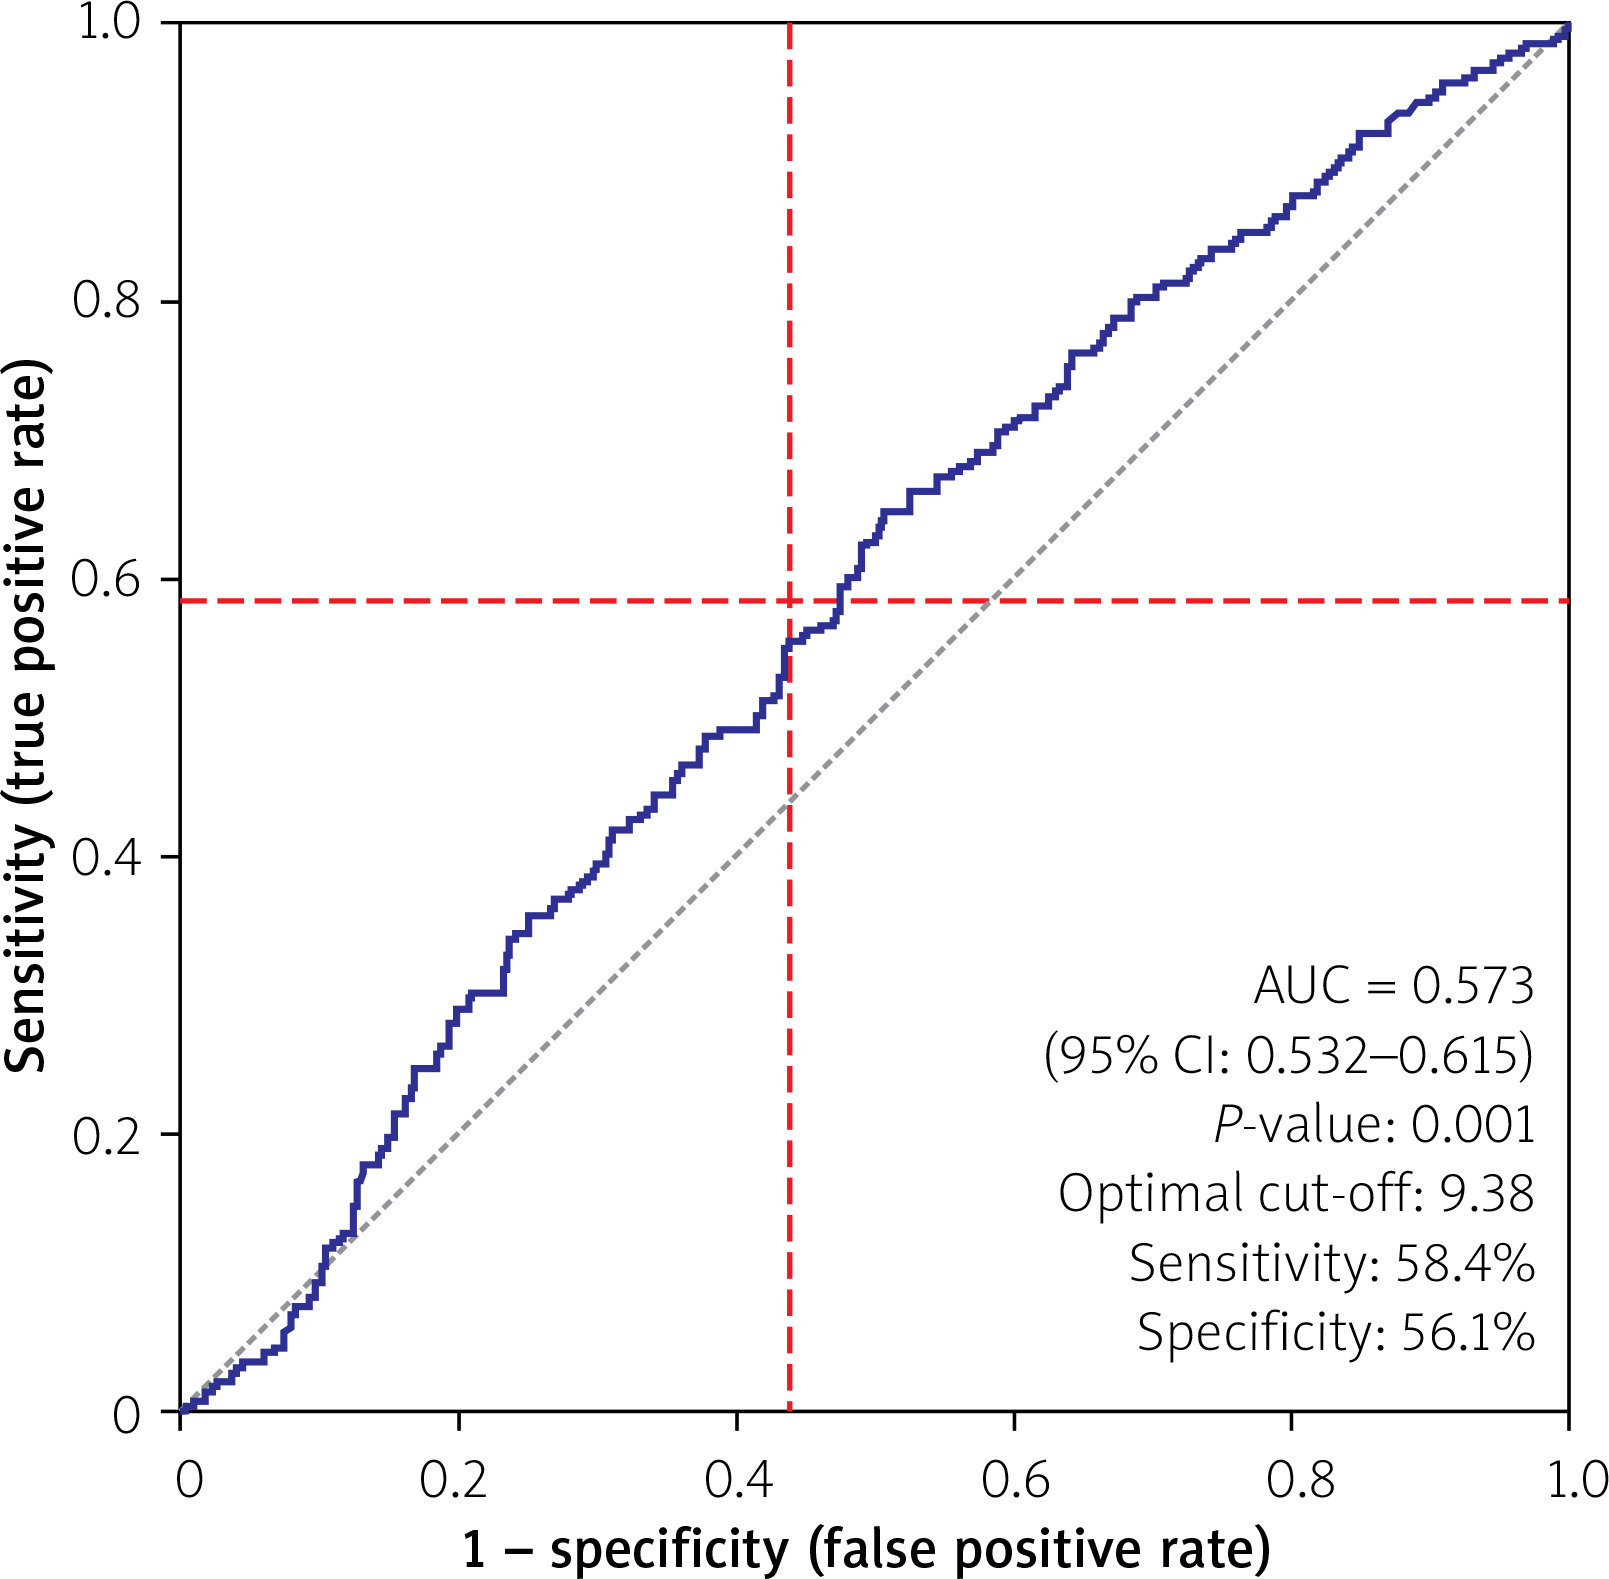
Although the TyG index remained independently associated with MACE in multivariable analysis, the relatively low AUC indicates limited standalone discriminative performance. The ROC-derived threshold (9.38) was used to assess discriminative ability and differs slightly from the median TyG value (9.24), which was used for cohort stratification.
Discussion
In this two-centre retrospective study of 757 patients with STEMI undergoing primary PCI, we demonstrated that a higher TyG index was significantly associated with an increased risk of MACE during 1-year follow-up. Importantly, this association remained significant after multivariable adjustment, suggesting that the TyG index may provide clinically relevant prognostic information beyond conventional cardiovascular risk factors and key angiographic variables.
IR is increasingly recognised as a central contributor to the pathophysiology of coronary artery disease and acute myocardial infarction. IR promotes endothelial dysfunction, oxidative stress, vascular inflammation, platelet activation, and a pro-thrombotic state, all of which may accelerate atherosclerotic progression and increase plaque vulnerability [19, 22–25]. In the acute ischaemic setting, these mechanisms may also contribute to impaired myocardial perfusion, heightened ischaemia-reperfusion injury, and adverse remodeling, thereby providing a biologically plausible explanation for the association between elevated TyG index and worse clinical outcomes.
Our findings are consistent with previous reports demonstrating that the TyG index is associated with adverse prognosis in acute coronary syndromes and PCI-treated myocardial infarction populations. Several studies have shown that higher TyG values are independently associated with mortality, recurrent ischaemic events, and composite cardiovascular endpoints in ACS and STEMI cohorts [18, 21, 26–29]. More recently, Zhang et al. reported that the prognostic significance of the TyG index also extends to acute heart failure populations, further supporting its role as a marker of adverse cardiometabolic risk [30]. In line with these observations, our data suggest that the TyG index may capture a broader cardiometabolic vulnerability that is not fully reflected by traditional clinical descriptors alone.
An important finding of our study is that the TyG index remained independently associated with 1-year MACE even after adjustment for age, sex, hypertension, diabetes mellitus, multivessel disease, and LDL cholesterol. This suggests that the prognostic relevance of the TyG index could extend beyond the mere presence of conventional metabolic comorbidities and may instead reflect a more integrated state of dysmetabolism, inflammation, endothelial dysfunction, and vascular susceptibility. In this regard, the TyG index may serve as a pragmatic marker of residual cardiometabolic risk in STEMI patients undergoing primary PCI.
A noteworthy and somewhat unexpected observation in our cohort was the higher prevalence of multivessel coronary artery disease and no-reflow phenomenon in the low-TyG group, despite this group experiencing fewer MACE events during follow-up. At first glance, this may appear paradoxical. However, this pattern suggests that anatomical coronary burden and metabolic vulnerability are not interchangeable and may contribute to adverse outcomes through partly distinct and complementary mechanisms.
Multivessel disease primarily reflects the structural extent of epicardial coronary atherosclerosis, whereas the TyG index probably captures a more systemic cardiometabolic risk profile characterised by insulin resistance, inflammatory activation, endothelial dysfunction, microvascular susceptibility, and impaired tissue-level reperfusion [16, 29, 31].
In this context, patients with higher TyG values may remain biologically more vulnerable to adverse events even in the absence of more extensive angiographic disease. The fact that both multivessel disease and the TyG index retained independent significance in the multivariable model supports the notion that these variables may represent different dimensions of cardiovascular risk rather than overlapping surrogates of the same process. Furthermore, this unexpected distribution could be linked to unique sample characteristics within our two-centre registry, localised referral patterns, or unmeasured confounding factors that influenced mechanical revascularisation dynamics independently of metabolic markers.
The no-reflow finding should also be interpreted with caution. Previous studies have suggested that higher TyG values may be associated with impaired myocardial reperfusion and microvascular dysfunction after PCI [28]. However, in our cohort, no-reflow was numerically more frequent in the low-TyG group. This discrepancy may indicate that the relationship between metabolic risk and angiographic or microvascular reperfusion is not necessarily linear or uniform across all STEMI populations. It is also possible that procedural, anatomical, thrombotic, or unmeasured clinical factors contributed to this directional inconsistency. Therefore, our no-reflow findings should be considered hypothesis-generating rather than definitive, and they underscore the need for further prospective studies specifically designed to evaluate the interaction between TyG index and reperfusion quality.
Previous literature has consistently shown that the TyG index correlates with the extent and severity of coronary artery disease, including angiographic complexity and higher SYNTAX scores [16, 29, 31]. Our results do not necessarily contradict these data, but rather suggest that in STEMI cohorts, metabolic risk and anatomical disease burden may not always move in parallel within a given sample, particularly when outcomes are assessed over 1-year follow-up rather than being limited to the acute procedural period. This distinction may be clinically relevant, as adverse outcomes after STEMI are often influenced not only by epicardial anatomy, but also by myocardial injury, systemic inflammation, neurohormonal activation, and post-infarction recovery trajectories.
From a clinical perspective, the TyG index may be useful as an adjunctive risk stratification tool in STEMI patients undergoing primary PCI. Because it is derived from two routinely measured laboratory variables, it is inexpensive, rapidly available, and broadly applicable in everyday practice. Patients with elevated TyG values may represent a subgroup requiring closer surveillance, more intensive secondary prevention, and more aggressive optimisation of glucose-lipid metabolism after the index event.
At the same time, an important nuance of our findings is that although the TyG index was independently associated with 1-year MACE, its standalone discriminative performance was modest. In ROC analysis, the TyG index demonstrated only limited ability to discriminate MACE (AUC = 0.573). This is not entirely unexpected, as adverse outcomes after STEMI are inherently multifactorial and are unlikely to be fully captured by a single metabolic biomarker. Therefore, the TyG index should not be interpreted as a strong standalone predictive classifier, but rather as a supplementary risk marker that may contribute incremental prognostic information when interpreted alongside established clinical and angiographic variables. Accordingly, the clinical value of the TyG index may lie more in risk enrichment than in standalone discrimination.
An important consideration when interpreting our findings is that the higher MACE rate observed in the high-TyG group appeared to be driven predominantly by cardiovascular hospitalisations rather than by hard ischaemic endpoints or mortality. Although the incidence of cardiovascular hospitalisation was significantly higher among patients with elevated TyG index values, differences in all-cause mortality, non-fatal myocardial infarction, and stroke did not reach statistical significance. Therefore, the association between a higher TyG index and MACE in our cohort should primarily be interpreted as reflecting an increased burden of recurrent cardiovascular morbidity and healthcare utilisation rather than a clear increase in hard ischaemic events or mortality. These findings warrant cautious interpretation and should be confirmed in larger prospective studies with sufficient power to evaluate individual clinical endpoints.
The present study has several limitations. First, its retrospective and two-centre design introduces the possibility of selection bias and residual confounding despite multivariable adjustment. Second, the TyG index was derived from fasting values obtained during the acute STEMI phase, and therefore acute stress-related metabolic fluctuations may have influenced the measured values in some patients. Acute myocardial infarction may induce stress-related metabolic changes that can transiently affect glucose and triglyceride levels. Therefore, the calculated TyG index may reflect both chronic insulin resistance and the acute metabolic response to STEMI rather than just baseline metabolic status. Third, the TyG index was measured at a single time point during the acute phase of STEMI and therefore may not fully reflect longitudinal changes in metabolic status. Fourth, the use of median-based dichotomisation, while methodologically practical for internal risk stratification and balanced subgroup comparison, may have reduced some of the information contained in the continuous TyG variable. Fifth, some angiographic variables were unavailable in a subset of patients, and regression analyses were therefore performed using a complete-case approach without multiple imputation, which may restrict the generalisation of our findings. Sixth, follow-up data were recorded as fixed 1-year outcomes rather than precise time-to-event intervals, which prevented the use of Cox proportional hazards or Kaplan–Meier survival analyses. Finally, due to localised variations in electronic data logging across the participating centres, several critical clinical parameters such as left ventricular ejection fraction (LVEF), Killip functional class at presentation, exact total ischaemic or symptom-to-balloon intervals, specific culprit vessel locations, and discharge medical therapy modifications could not be integrated into our multivariable models without causing substantial case-deletion. This omission represents a potential source of residual confounding that must be considered when interpreting the independent prognostic weight of the TyG index.
In addition, renal function and haemoglobin levels differed significantly between the study groups and may have prognostic relevance in patients with STEMI. Although these variables were available, they were not incorporated into the final multivariable model to maintain model parsimony and to avoid overfitting given the retrospective design and the predefined modelling strategy. Consequently, residual confounding related to renal dysfunction or haematological status cannot be completely excluded and should be addressed in future prospective studies.
Conclusions
In patients with ST-segment elevation myocardial infarction undergoing primary percutaneous coronary intervention, a higher TyG index was independently associated with an increased risk of major adverse cardiovascular events during 1-year follow-up. Although its independent statistical association is clear, its standalone discriminative performance is modest, indicating that it should be utilised as an adjunctive marker of risk enrichment rather than a primary standalone predictive tool. These findings suggest that the TyG index may provide complementary prognostic information beyond conventional clinical and angiographic variables, and may it be useful as an adjunctive tool for risk stratification in STEMI patients. Further prospective and externally validated studies are needed to clarify its role within integrated risk prediction models.










