
Introduction
Beta-lactam (β-lactam) antibiotics include penicillins, cephalosporins, monobactams and carbapenems. These antibiotics are a widely used group of medicinal products that are bactericidal and effective against a broad spectrum of bacteria. The common feature of all these antibiotics is the presence of a β-lactam ring, which disrupts the bacterial cell wall. Because of their clinical utility, β-lactams remain the first-line treatment for many community- and hospital-acquired infections. Up to 9–10% of the general population now carry a “penicillin-allergy” label, making β-lactams the most frequently reported drug allergens; however, more than 90% of these labels prove negative on formal testing, leading to unnecessary avoidance, broader-spectrum antibiotic use and worse clinical outcomes [1].
Allergies to antibiotics, in general, are not uncommon, but anaphylaxis occurs less frequently. It is a severe systemic hypersensitivity reaction that can be life-threatening to the patient. Prospective cohorts suggest that true IgE-mediated immediate reactions occur in barely 2% of patients who report β-lactam hypersensitivity, yet they account for a disproportionate share of drug-induced anaphylaxis in adults [2, 3]. The massive release of inflammatory mediators results from the activation and degranulation of mast cells and basophils via a specific IgE-mediated pathway upon re-exposure to the allergen.
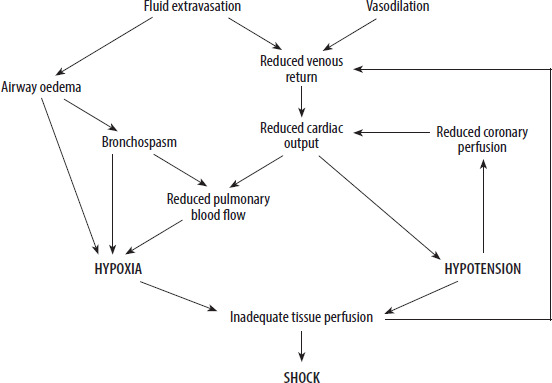
Over the past two decades the incidence of all-cause anaphylaxis has risen worldwide, with medications – particularly antibiotics – now surpassing foods as the leading trigger in many registries; despite this rise, the case fatality rate has remained stable at approximately 0.5–1%, a trend attributed to faster recognition and earlier administration of intramuscular adrenaline [4, 5]. Anaphylaxis is characterised by the rapid onset of symptoms affecting airway patency and/or ventilation and/or circulation. It may also be accompanied by skin and mucosal changes, such as urticaria or angioedema. The cascade of pathophysiological events leading from β-lactam–induced airway and vascular changes to frank shock is summarised in Figure 1.
Case report
These 2 case reports demonstrate the rapid onset of β-lactam-induced anaphylaxis in both pre-hospital and inpatient care. Together they emphasise that immediate recognition and guideline-directed adrenaline, airway and fluid management are essential to survival.
Written informed consent for publication of these case details was obtained from both patients.
Out-of-hospital scenario
The ambulance service operations centre received an emergency call about a woman who had begun choking and fell unconscious approximately 10 min after taking an amoxicillin-clavulanate tablet. The closest ground response team with a doctor departed immediately and an air ambulance also took off, as the scene of the incident was a long drive from the nearest hospital. On arrival, a 52-year-old woman was found lying unconscious on the floor of her home, with a Glasgow Coma Scale (GCS) score of 4. Gastric contents without pathological admixture were visible around her. She was bradypnoeic and had gasping respirations. A carotid pulse was palpable, but peripheral pulses were absent. Significant tachycardia was present. Peripheral oxygen saturation could not be measured because of severe hypotension and poor peripheral perfusion. Urticaria was clearly visible on the skin of the torso, and the soft tissues of the face and neck were slightly swollen. High-flow oxygen and assisted ventilation with a self-inflating bag-valve mask were initiated immediately. After positioning, the airway was patent and ventilation was possible. A dose of 0.5 mg of adrenaline was administered intramuscularly into the thigh. After repeated unsuccessful attempts to obtain intravenous access, intraosseous access was established in the right proximal humerus. An additional 0.3 mg of adrenaline was injected intraosseously using this route. Next, delivery of balanced crystalloid solution was initiated using a pressure cuff. A total of 750 ml of balanced crystalloid solution was administered. The patient’s condition then began to improve. She regained consciousness and responded to verbal stimuli, was able to breathe spontaneously, and had a normal respiratory rate. Following haemodynamic improvement, intravenous access was established, and 2 mg of bisulepin was administered, followed by 24 mg of dexamethasone. The patient was airlifted to the emergency department of the University Hospital, with spontaneous ventilation, a patent airway, good saturation with mask oxygen therapy, GCS 15, a heart rate of 90 beats per minute and blood pressure at 115/70 mm Hg. Her medical history additionally revealed that she had experienced a mild allergic reaction to metamizole in adolescence. She had taken various antibiotics repeatedly with no allergic reaction. She had begun taking a β-lactam antibiotic prescribed to treat a urinary tract infection. The patient was discharged after 2 days in hospital without any further complications.
In-hospital scenario
A 27-year-old man, who had no previous serious illness, was admitted to hospital for extensive left-sided community-acquired pneumonia. On admission, he was conscious and eupnoeic, with no cyanosis. His oxygen saturation was 90%, and oxygen therapy via nasal prongs was therefore initiated. Capillary refill time was within 2 s, heart rate was 80 beats per minute, and blood pressure was at 125/75 mm Hg. The electrocardiogram (ECG) showed no ischaemic changes or arrhythmias. Laboratory results showed significantly elevated levels of inflammatory markers: C-reactive protein (CRP) 232 mg/l, procalcitonin 1.25 µg/l and ferritin 789 µg/l. Baseline laboratory parameters are summarised in Table 1.
TABLE 1
Baseline laboratory values obtained on admission (in-hospital scenario)
Based on the patient’s clinical condition, X-ray findings, and laboratory values, a decision was made to initiate antibiotic therapy with a combination of ceftriaxone and clarithromycin. Shortly after starting the infusion of 2 g of ceftriaxone, the patient began to report chest tightness, shortness of breath and a swelling sensation in the throat. Urticaria began to appear on his torso and neck. The patient became objectively anxious, restless, tachypnoeic, tachycardic with a heart rate of 120 beats per minute, and his blood pressure dropped to 80/50 mm Hg. The antibiotic infusion was stopped immediately, and a doctor was called. Adrenaline 0.3 mg was administered intramuscularly, followed by 2 mg of bisulepin intravenously and initiation of a 500 ml balanced crystalloid infusion. Oxygen therapy with a high-flow oxygen mask was also begun. In view of the mildly spasmodic auscultatory findings, 5 mg of salbutamol was administered by nebulisation, with good effect. Next, 200 mg of hydrocortisone was also administered intravenously. The patient’s condition improved rapidly, and a repeat dose of adrenaline was not required. After treatment of the acute phase, the serum tryptase concentration was measured at 94.4 µg/l. The measurement was repeated on the second day of hospitalisation, when the concentration was 7.1 µg/l. The result helped confirm the diagnosis of anaphylaxis. As part of the antibiotic treatment for community-acquired pneumonia, it was necessary to switch to a fluoroquinolone. The patient was discharged in generally good condition after 7 days of hospitalization.
Discussion
β-Lactam antibiotics are the most commonly reported cause of antibiotic allergy. In the United States, β-lactam allergy is documented in approximately 8% of patients using healthcare services. Cephalosporin allergy is recorded in approximately 1% of patients, while allergies to β-lactams other than penicillins and cephalosporins are documented even less frequently. However, the majority of reported allergic reactions to penicillin are not associated with clinically significant IgE-mediated reactions after repeated administration of penicillin [6]. Beta-lactam antibiotics are widely prescribed in the general population, especially to outpatients, due to their efficacy against many Gram-positive, Gram-negative and anaerobic infections, and their low cost. However, prescription of these antibiotics is often limited by the occurrence of a hypersensitivity reaction. Ben Fadhel et al. [7] state that previously published data report hypersensitivity to β-lactam antibiotics in 10% to 20% of patients in clinical practice. Solensky [8] points out that recent publications have shown that more than 90% of patients with a history of penicillin allergy are able to tolerate penicillins after a complete examination based on skin tests and, where appropriate, oral provocation testing. Moussa et al. [9] performed preoperative testing of 194 patients with a history of allergy to β-lactam antibiotics. Based on the skin and oral provocation tests performed, hypersensitivity was not confirmed in 94.3% of patients. Picard et al. [10] performed a retrospective analysis of 1738 patients admitted to selected hospital wards over a 1-year period. 172 (9.9%) patients had an allergy to β-lactam antibiotics listed in their medical records. Only 30% of patients had an allergic reaction described in their records. The use of alternative antibiotics increased the cost of the treatment provided by 16,000 Canadian dollars. Excessive and unsubstantiated history of allergy to β-lactam antibiotics significantly increases the cost of care provided. Sousa-Pinto et al. [11] carried out an economic evaluation study, in which they modelled the financial cost of care provided to patients with a history of penicillin allergy who would undergo diagnostic testing (oral provocation or skin test) and compared this cost to care provided to patients with a history of penicillin allergy without diagnostic testing. For hospitalised patients, diagnostic testing and subsequent selection of the appropriate antibiotic would result in average savings of $657 per patient (United States: $1,444; Europe: $489). These conclusions support the concept of widespread diagnostic testing of patients with a history of allergy to β-lactam antibiotics. From a sociological perspective, the “penicillin allergy” label may function as a form of medical labelling that shapes both patients’ understanding of their health and clinicians’ treatment decisions. The consequences of inaccurate labelling may be particularly significant in populations affected by limited health literacy [12, 13], where such labelling can exacerbate existing health inequities by increasing reliance on costlier broad-spectrum antibiotics and exposing patients to their associated risks. Implementing routine de-labelling programs is therefore not only a clinical quality measure but also a social-justice intervention that promotes equitable access to optimal antimicrobial therapy.
Although a history of β-lactam allergy is frequently mentioned in medical records, only approximately 10% of these patients actually have a diagnostically verified β-lactam allergy. Clinical manifestations of β-lactam hypersensitivity vary, with urticaria being the most common [14]. Anaphylaxis is a rare but life-threatening manifestation. Liang et al. [15] published a retrospective population-based study focused on the incidence of adverse events associated with the use of penicillins, carbapenems, monobactams, and clindamycin. In this study, one incident of penicillin-associated anaphylaxis was identified in 255,320 oral exposures. For parenteral administration of penicillin, there was 1 case of anaphylaxis per 123,792 exposures. Only 1/1543 (0.065%) oral and 1/1030 (0.097%) parenteral penicillin-associated allergy reports were confirmed to be anaphylaxis. Furthermore, no anaphylaxis was identified after the administration of carbapenems or monobactam.
Adrenaline is an essential medication in the treatment of anaphylaxis [16]. Adrenaline increases myocardial contractility and accelerates the heart rate. It increases blood pressure by vasoconstriction and by increasing peripheral vascular resistance. In adults and children over 12 years of age, it is administered intramuscularly at a dose of 0.5 mg. For children between 6 and 12 years of age, it is 0.3 mg. For even smaller children, it is 0.15 mg. Intravenous administration of adrenaline in anaphylaxis needs to be carried out by specialists with practical experience of this route of administration due to the higher risk of adverse reactions and dosing errors [17, 18]. These specialists are primarily anaesthesiologists, emergency doctors and intensivists. After adrenaline administration, continued monitoring is necessary to detect clinical deterioration or a biphasic reaction promptly. Up to 10% of patients require a second dose of adrenaline and 2.2% require multiple doses [19]. Persistent respiratory or cardiovascular symptoms despite two appropriate intramuscular doses of adrenaline indicate refractory anaphylaxis [20]. Nebulised adrenaline may also be administered as an adjunct to the treatment of upper airway obstruction caused by laryngeal oedema [21].
An integral part of the treatment of anaphylaxis is oxygen therapy with the goal of maintaining a saturation of 94–98%. In patients at risk of hypercapnic respiratory failure, this should be 88–92% [22]. Fluid therapy should be carried out using crystalloid solutions. The initial fluid bolus should be 10 ml/kg in children and 500–1000 ml in adults. The role of antihistamines in the treatment of anaphylaxis is still under debate. The consensus remains that antihistamines should not be used as first-line treatment [23, 24]. Even the administration of corticosteroids continues to be debated. Their primary effect is more one of modulating the late phase of the inflammatory reaction and they have no proven positive impact on the treatment of the first phase of the reaction. Their effect on preventing a biphasic anaphylactic reaction is also questionable [25, 26]. The most commonly recommended corticosteroid for administration is hydrocortisone. Its use has long been widespread beyond the treatment of anaphylaxis. In sepsis, for example, its effect on reducing mortality and vasopressor usage has long been considered. A combination of hydrocortisone, thiamine and ascorbic acid could be promising [27].
Conclusions
Because β-lactam antibiotics are widely used, clinicians must be prepared to recognise and initiate treatment for anaphylaxis, even in patients without a documented drug allergy. Prompt administration of intramuscular adrenaline is critical. High-flow oxygen should be initiated, and adequate crystalloid fluid therapy should be provided once vascular access has been established. If an allergic reaction occurs during intravenous antibiotic administration, the infusion must be stopped immediately. In the event of cardiac arrest, cardiopulmonary resuscitation must be initiated in accordance with current international guidelines.











