
Purpose
Hepatocellular carcinoma (HCC) is the most common primary liver malignancy, and represents the sixth most frequently diagnosed cancer worldwide and the third leading cause of cancer-related mortality [1]. Upfront surgical resection is considered the standard curative treatment for early-stage disease, while liver transplantation offers the highest overall survival (OS) for tumors confined to the liver [2-4]. However, many patients are not suitable surgical candidates and excluded from operative management due to patient-related factors, such as advanced age, comorbid medical conditions, severity of hepatic decompensation, unfavorable anatomical lesion sites, extent of metastases, prior abdominal surgery, or patient preferences [5-8]. For HCC, local therapy options include radiofrequency ablation (RFA), microwave ablation (MWA), trans-arterial chemoembolization (TACE), selective internal radiation therapy (SIRT), and local radiotherapy.
Among local radiotherapy approaches, interstitial high-dose-rate brachytherapy (iBT) and stereotactic body radiotherapy (SBRT) have demonstrated favorable local control rates with minimal toxicity, particularly for patients who are not candidates for surgical resection or thermal ablation [9-21]. Direct comparisons between these two radiation techniques remain restricted, as the available literature is predominantly limited to dosimetric analyses or comparisons of dose-volume parameters, with comparative clinical outcomes insufficiently defined [22-26]. Therefore, this retrospective study was conducted to address this knowledge gap by providing a comparative real-world evaluation of clinical outcomes for iBT and SBRT in patients with HCC treated at a large tertiary cancer center.
Material and methods
Patient selection
This retrospective study included data of patients treated with iBT or SBRT for HCC at the University of Leipzig Medical Center between January 2014 and December 2024. Clinical data were extracted from institutional medical records.
Eligible patients with radiologically or histologically confirmed HCC, having one to four liver lesions and adequate liver function were included. Patients with extra-hepatic disease or subsequent liver transplantation were excluded from the analysis. During follow-up, seven patients in the iBT group and one patient in the SBRT group underwent liver transplantation and were therefore excluded. Treatment allocation to iBT or SBRT was non-randomized and based on multidisciplinary tumor board recommendations along with shared decision-making involving every patient. Treatment selection was guided by technical feasibility of catheter placement and expected ability to achieve adequate target coverage. IBT was preferentially used for larger lesions and tumors adjacent to critical organs at risk, whereas SBRT was favored when a non-invasive approach was desired. Treatment planning and delivery were performed in accordance with institutional protocols and practical guidelines [27, 28].
The study was approved in advance by the local Ethics Committee (approval number: 432/24-ek), and conducted in accordance with the Declaration of Helsinki. The study followed the STROBE reporting guidelines [29].
Brachytherapy
Brachytherapy catheter placement was performed under CT guidance by interventional radiologist using the Seldinger technique under conscious sedation. After positioning of the catheters, a 3D treatment plan based on contrast-enhanced CT or MRI scan with 3 mm slice thickness was created using a planning system (Oncentra® Brachy, Elekta Instrument AB, Stockholm, Sweden) and the Task Group No. 43 (TG-43) algorithm [30]. Gross tumor volume (GTV) was treated to a single fraction between 15 Gy and 25 Gy, as described earlier [26]. Dose prescription aimed to achieve full target coverage with the goal to encompass 100% of the GTV volume with the prescribed dose. IBT was performed using a microSelectron afterloader (Elekta AB, Stockholm, Sweden), equipped with an iridium-192 (192Ir) radiation source.
Stereotactic body radiotherapy
The patient was placed in a supine position in a vacuum mattress for a planning CT scan with 2 mm slice thickness in deep inspiration breath hold (DIBH) or free breathing (FB). Tumor was delineated based on a 4D planning CT that was co-registered to the available diagnostic magnetic resonance imaging (MRI) or contrast-enhanced CT. Internal target volume (ITV) was derived by combining GTV contours of all DIBH CTs or 4D CT scans with a 2 mm margin, respectively. Planning target volume (PTV) was defined by applying a 3 mm margin to account for motion and setup uncertainties. Collapsed cone algorithm (CCDose v. 5.4) was used for dose calculation in RayStation planning system (version 12A; RaySearch Laboratories AB, Stockholm, Sweden). A total dose of 3 x 12.5 Gy was prescribed to the surrounding 65% isodose, resulting in a dose maximum of 57.7 Gy and requiring that 95% of PTV was covered by the 95% isodose of the prescribed dose. All SBRT plans were treated with a TrueBeam STx linear accelerator (Varian Medical Systems, Palo Alto, CA, USA), with a 120-leaf micro-multileaf collimator and 6 MV flattening filter-free photons [27, 31]. Treatment was performed every other day with DIBH or FB techniques, depending on patient condition and abilities.
Response assessment
Radiological findings from routinely performed quarterly follow-up imaging with CT and MRI were retrospectively analyzed for local, intra-hepatic, and distant tumor progressions. For the assessment of local control (LC), local recurrence was defined as radiological progression or re-appearance of the treated lesion on follow-up imaging, as determined by multidisciplinary tumor board consensus and/or documented radiological assessment. HCC lesions without evidence of recurrence were censored at the time of the most recent imaging. For patients treated for more than one HCC lesion, LC was analyzed at the lesion level using a patient-clustered robust variance estimator, and OS and progression-free survival (PFS) were patient-level endpoints. A sensitivity analysis restricted to one lesion per patient provided concordant results. OS was calculated from the end of radiotherapy to death from any cause or last follow-up. The time interval from the termination of SBRT or iBT until death or the occurrence of any imaging-confirmed progression of the tumor disease, was defined as PFS. Acute (≤ 90 days post-irradiation) and chronic (> 90 days post-irradiation) treatment-related adverse events were reported according to the common terminology criteria for adverse events (CTCAE) version 5.0 [32].
Statistical analysis
Categorical variables were summarized as absolute and relative frequencies, and continuous variables as median with interquartile range or mean with standard deviation. Baseline characteristics were summarized descriptively by treatment group. To explore confounding from baseline imbalances, an additional exploratory 1 : 1 matched sensitivity analysis was created, with multivariable Cox regression serving as the primary adjustment. Residual imbalance persisted after matching for sex, CCI, and ALBI, so the matched analysis was interpreted as exploratory. In the unmatched cohort, continuous variables were compared using the Mann-Whitney U test, while for categorical variables, the Fisher’s exact test was applied. In the matched cohort, baseline balance was assessed using absolute standardized mean differences (SMDs) rather than significance testing [33]. Patients with complete data for lesion diameter, Karnofsky performance status, Charlson comorbidity index (CCI), albumin-bilirubin (ALBI) score, Child-Pugh score (CPS), and liver cirrhosis status, were eligible for matching. Each SBRT patient was matched to one iBT patient by optimal direct covariate-distance matching based on these variables, resulting in equally-sized groups. Baseline balance before and after matching was assessed using absolute standardized mean differences (SMDs). For time-to-event analyses, OS, PFS, and LC were defined as endpoints. Kaplan-Meier estimates were used to analyze OS, PFS, and LC. One-, two-, and three-year rates with 95% confidence intervals (95% CIs) were reported, whereas differences between iBT and SBRT were assessed using the log-rank test.
To investigate the association of potential prognostic factors with OS, PFS, and LC, Cox proportional hazards regression models were applied. In univariable analyses, treatment modality (iBT vs. SBRT), age, sex, lesion diameter, Karnofsky performance status (KPS), CCI, liver cirrhosis, CPS, model of end stage liver disease (MELD), α-fetoprotein (AFP), and albumin-bilirubin (ALBI) score, were evaluated separately. Results were reported as hazard ratios (HRs) with 95% CI and p-values. Variables with clinical relevance and/or a univariable threshold of p-value < 0.20 were entered into multivariable Cox models for OS and LC. Due to the limited number of events, PFS was analyzed using univariable Cox models only. Given the exploratory nature of the study and that all p-values were two-sided, p-values were not adjusted for multiple testing, and should therefore be interpreted descriptively. All analyses were performed using Python 3.11 (including the packages matplotlib v. 3.10.0, pandas v. 2.2.3, lifelines v. 0.30.0, and statsmodels v. 0.14.4). Dose-volume parameters were extracted from treatment-planning systems and summarized by treatment group. Biologically effective dose (BED10) and equivalent dose in 2 Gy fractions (EQD2) were derived from the prescribed dose and fractionation with an α/β of 10 Gy.
Results
Patient characteristics
A total of 92 patients with 125 HCC lesions were analyzed. Of these, 60/92 patients (65.2%) with 86/125 lesions (68.8%) received iBT, and the remaining patients were treated using SBRT. There were 71/92 patients (77.2%) with a single lesion. Median patient age was 70 years (range, 39-89 years), and most patients were males (85.7%). Liver cirrhosis was present in 87/92 (94.6%) patients, and most cases were classified as CP A (74/87, 85.1%). The median tumor diameter was 3.0 cm (range, 1.0-8.0 cm). Of the 125 HCC lesions, 17 (18.5%) were treated with radiation therapy as the primary treatment, while the remaining lesions received radiation therapy as the salvage treatment after prior surgery, RFA, MWA, TACE, or SIRT. The details of the patients’ characteristics are presented in Table 1.
Table 1
Patient characteristics
[i] SBRT – stereotactic body radiotherapy, iBT – interstitial high-dose-rate brachytherapy, HCC – hepatocellular carcinoma, CI – confidence interval, AFP – α-fetoprotein, IQR – interquartile range, MELD – model of end stage liver disease, TACE – trans-arterial chemoembolization, RFA – radiofrequency ablation, MWA – microwave ablation, SIRT – selective internal radiotherapy, ALBI – albumin-bilirubin, RT – radiotherapy, CT – computed tomography, MRI – magnetic resonance imaging, PET – positron emission tomography
Considering the entire cohort, the most frequently used dose concept for SBRT was 3 × 12.5 Gy (33/39, 84.6%) prescribed to the surrounding isodose, and 1 × 20 Gy for iBT (57/86, 66.3%). The dosimetric data are shown in Table 2. The median prescription dose, expressed as BED10 and EQD2, was higher in the SBRT group compared with iBT (84.4 Gy vs. 60.0 Gy and 70.3 Gy vs. 50.0 Gy, respectively). The median target coverage (D98, % of the prescription dose) was comparable. The median GTV volume was larger in the iBT group compared with SBRT (22.7 cm3 vs. 14.8 cm3).
Table 2
Dosimetric parameters by treatment modality (median [IQR])
[i] BED – biologically effective dose, EQD2 – equivalent dose in 2 Gy fractions, GTV – gross tumor volume, PTV – planning target volume, D98 – dose to 98% of the volume, V10Gy – volume receiving ≥ 10 Gy, iBT – interstitial brachytherapy, SBRT – stereotactic body radiotherapy; Coverage D98 refers to GTV for iBT and PTV for SBRT; BED and EQD2 (α/β = 10 Gy) computed from prescription dose
Compared with the iBT group, the SBRT treatment group had significantly higher proportion of female patients and higher comorbidity burden, reflected by higher CCI and ALBI score. To reduce baseline imbalances resulting from the SBRT cohort having more pre-existing comorbidities, a matched sub-cohort was generated, as described above. The matched cohort comprised 32 iBT and 32 SBRT patients. Median imputation was used only to compute matching distances, with original values retaining for reporting, which explains why some variables retained missing values in the matched cohort. The details of the cohort analysis are listed in Table 3.
Table 3
Baseline characteristics of unmatched and 1 : 1 matched cohorts by treatment modality
Oncological outcome parameters
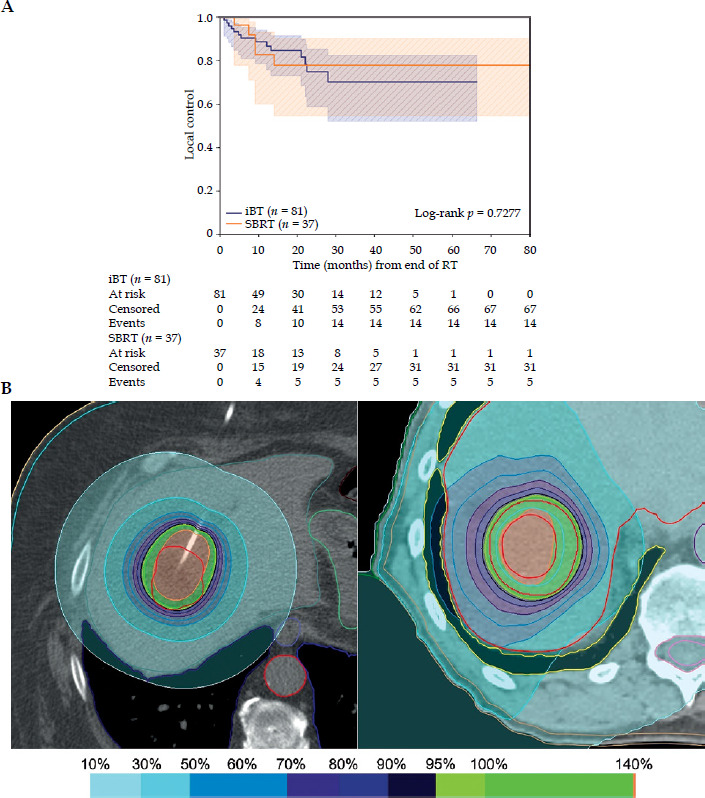
The median follow-up time was 21 months (IQR, 11-39 months). In this period, 59 patients died (SBRT: 26/32, 81.3%, and iBT: 33/60, 55.0%), and 19 local recurrences were observed (SBRT: 5/39, 12.8%, and iBT: 14/86, 16.3%).Oncological outcomes were evaluated separately for SBRT and iBT treatment groups. No significant difference was observed regarding LC and PFS. LC at 1 and 3 years in the unadjusted iBT was 88.7% (95% CI: 78.5-94.2) and 70.2% (95% CI: 52.1-82.5), respectively. For the SBRT sub-group, 1- and 3-year LCs were 82.8% (95% CI: 60.0-93.2) and 77.9% (95% CI: 54.5-90.2), respectively (Figure 1).
Fig. 1
A) Local control of lesions treated with interstitial high-dose-rate brachytherapy (iBT) and stereotactic body radiotherapy (SBRT). B) Illustrative dose distribution for iBT (left) with 1 × 20.0 Gy, and SBRT (right) with 3 × 12.5 Gy, prescribed to the surrounding 65% isodose
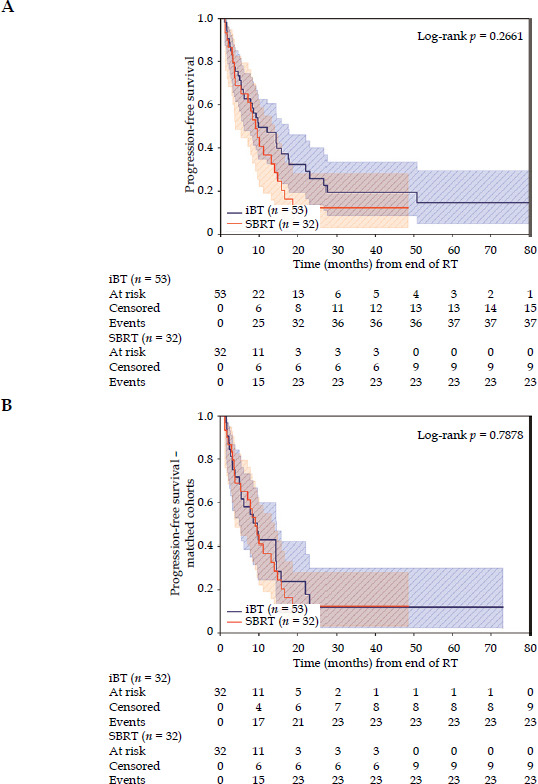
PFS at 1 and 3 years for the unadjusted iBT was 49.4% (95% CI: 34.7-62.6) and 19.4% (95% CI: 8.6-33.4), respectively. For the SBRT sub-group, 1- and 3-year PFSs were 36.7% (95% CI: 18.9-54.6) and 12.2% (95% CI: 3.1-28.0) (Figure 2). In both groups, the most frequent type of tumor progression was new intra-hepatic HCC lesion (SBRT: 14/32, 43.8%, and iBT: 30/60, 50.0%).
Fig. 2
Progression-free survival for (A) the entire cohort, and for (B) the matched interstitial high-dose-rate brachytherapy (iBT) and stereotactic body radiotherapy (SBRT) cohorts
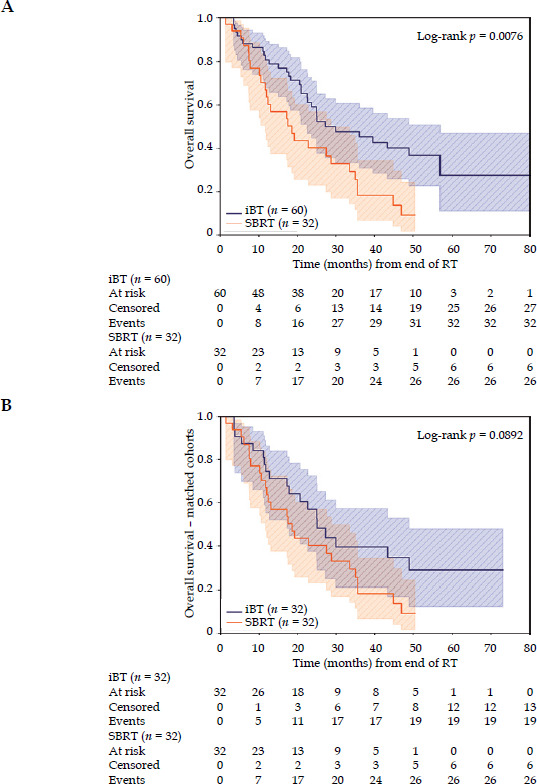
In the unmatched cohort, OS was significantly higher in the iBT group (p < 0.01). No statistical significance was found after adjustment for baseline characteristics in the matched cohorts (p = 0.089). For the unmatched iBT sub-group, 1- and 3-year OSs amounted to 80.7% (95% CI: 67.8-88.8) and 47.6% (95% CI: 33.2-60.7), and for the matched cohort, OSs were 74.4% (95% CI: 55.3-86.3) and 39.4% (95% CI: 21.1-57.3), respectively. For the SBRT sub-group, 1- and 3-year OSs were 63.6% (95% CI: 44.0-78.0) and 18.3% (95% CI: 6.8-34.2), respectively (Figure 3).
Fig. 3
Overall survival for (A) the entire cohort, and for (B) the matched interstitial high-dose-rate brachytherapy (iBT) and stereotactic body radiotherapy (SBRT) cohorts
In multivariable analysis, tumor size was associated with less favorable PFS and OS, while CCI, AFP (in ng/ml), and ALBI score were associated with worse OS (HR: 1.18, p = 0.03; HR: 1.0002, p = 0.01; and HR: 2.85, p < 0.001, respectively). LC, PFS, and OS were comparable irrespective of the treatment technique (Table 4).
Table 4
Uni- and multivariable analyses of overall survival, progression-free survival, and local control before cohort matching
[i] OS – overall survival, PFS – progression-free survival, HR – hazard ratio, iBT – interstitial high-dose-rate brachytherapy, SBRT – stereotactic body radiotherapy, KPS – Karnofsky performance status, CCI – Charlson comorbidity index, CPS – Child-Pugh score, AFP – α-fetoprotein, ALBI – albumin-bilirubin score
Safety analysis
The most frequently observed grade 1 toxicity following iBT was a transient elevation of liver enzymes (12/60, 20%), whereas fatigue was the most common grade 1 toxicity in the SBRT group (5/32, 15.6%). In the iBT cohort, two minor bleeding events (2/60, 3.3%) and one pneumothorax (1/60, 1.7%) were observed. Three acute grade 3 toxicities were observed in each treatment group, including elevations of liver enzymes in the iBT group and nausea in the SBRT cohort. Late toxicity following iBT was low (10/60, 16.7%) and limited to grade 1-2 events, such as ascites, cholecystitis, and hydrothorax. In the SBRT group, late toxicity occurred in 9/32 patients (28.1%) and consisted predominantly of elevated liver enzymes grade 1. No severe late toxicity grade ≥ 3 was observed in both treatment groups, and no cases of liver abscess, acute liver failure, or abdominal bleeding were reported (Tables 5 and 6).
Table 5
iBT-related acute and chronic adverse events reported according to the common terminology criteria for adverse events (CTCAE) version 5.0, with n = number and additionally relative values in percentage of total number of iBT patients, n = 60 (100%)
Table 6
SBRT-related acute and chronic adverse events reported according to the common terminology criteria for adverse events (CTCAE) version 5.0, with n = number and additionally relative values in percentage of total number of SBRT patients, n = 32 (100%)
Discussion
To the best of our knowledge, this is the first comparative study to evaluate clinical outcomes of iBT vs. SBRT in patients with HCC.
After a median follow-up of 21 months, LC and PFS were comparable between SBRT and iBT groups, while OS was worse in the SBRT group but not significant after adjustment, indicating it was likely due to patient selection.
A major strength of this study is the matched analysis of clinical cases, which minimizes potential confounding factors and enhances the comparability of clinical outcomes between iBT and SBRT in patients with HCC. By assessing real-world clinical outcomes, the study helps bridge the gap between theoretical planning-based comparisons and routine clinical practice. To date, several studies have investigated treatment planning and dosimetric characteristics of these treatment modalities in liver malignancies. Planning studies indicated that iBT can often achieve highly conformal dose delivery with steep dose gradients, potentially sparing normal liver tissue and adjacent organs. Similarly, SBRT enables precise dose delivery with reduced variability through motion management strategies, such as respiratory gating and image guidance. Dosimetric comparisons suggested that both modalities can provide excellent target coverage, although the pattern of dose distribution differs due to their inherent technical characteristics [22, 23, 25, 26, 34-36].
The reported 12-month OS rates following iBT in HCC range from 64% to 87.6%, and the 12-month OS of 80.7% observed in our study compares favorably with the published literature. Although the 36-month OS of 47.6% was statistically higher than those previously reported in the literature (range, 25-41.6%), this difference is likely attributable to a more favorable baseline patient cohort. LC after iBT in HCC has consistently been reported to be high, with 12-month LC rates between 90% and 95%. The LC rate of 89% at 12 months observed in our study is in line with these reports [9-21], despite differences in the prescribed dose. In our cohort, iBT was predominantly delivered as a single 20 Gy fraction, which is higher than those reported in several earlier studies [16, 18, 21]. The median prescription dose, expressed as BED10, was higher in the SBRT group compared with iBT. The reported BED10 for SBRT in our cohort falls within the range described in the literature. In a meta-analysis of published SBRT series, including 17 studies and 1,889 patients with HCC, the BED10 varied widely due to heterogeneous fractionation schedules, with a median of 85.8 Gy10 (range, 71.4-137.7 Gy10) [37]. Clinical outcomes reported for SBRT in the literature are similarly favorable. A recent meta-analysis observed a median 3-year LC rate of 81% (range, 31-100%), a median 3-year OS of 64% (range, 29-87%), and a median 3-year PFS of 39% (range, 15-61%), with tumor size identified as the only significant prognostic factor [37]. In our matched SBRT cohort, the observed 3-year LC rate of 77.9% is comparable with these reported values, whereas 3-year OS (18.3%) and PFS (12.2%) were statistically lower, which may be explained by differences in baseline characteristics.
After assessing baseline balance using absolute standardized mean differences, the groups were found to be inadequately matched with respect to gender (SMD = 0.414), CCI (SMD = 0.360), and ALBI (SMD = 0.328), indicating high comorbidity burden. Our cohort included fewer patients with truly solitary HCC, a higher proportion of Child-Pugh non-A patients, and slightly larger tumors. In addition, non-viral etiologies and a higher comorbidity burden may have influenced the survival outcomes.
In this study, both iBT and SBRT demonstrated favorable safety profiles. In previous research, treatment-related adverse events have been consistently reported as mild and manageable [38-42]. Treatment-related complications in the iBT cohort included bleeding (2/60, 3.3%) and pneumothorax (1/60, 1.7%), associated with catheter placement. Bleeding represents a rare complication of iBT, but warrants careful consideration in patients with underlying liver disease. Large series have reported overall major complication rates below 5%, and the rate observed in our patients falls within the reported range [41, 42].
This study has several limitations, including its retrospective design with the potential for selection bias and unmeasured confounding as well as limited follow-up in a sub-set of patients that may affect the assessment of long-term outcomes. The non-randomized treatment allocation may have introduced selection bias. Consequently, our results should be interpreted with caution, as they may partly reflect underlying differences in patient or tumor characteristics rather than treatment result alone. Additionally, the differentiation between treatment-related side effects and disease progression remains challenging, potentially introducing uncertainty into outcomes of patients with HCC. Lastly, although our findings align with previously reported data on patients with HCC, there is a need for prospective, multicenter trials to better define treatment protocols and to develop validated selection criteria.
Conclusions
Both iBT and SBRT represent effective local treatment modalities for patients with HCC, achieving comparable LC and PFS rates in this cohort. Though OS appeared superior in the iBT group in unadjusted analyses, this difference was no longer significant after adjustment for baseline characteristics, reflecting that patient selection may have contributed to the observed survival advantage. These findings support the use of both modalities as viable treatment options in appropriately selected patients. Treatment decisions should therefore be individualized based on tumor characteristics, liver function, and institutional expertise. As one of the first comparative real-world analyses of iBT and SBRT in patients with HCC, this study provides clinically relevant insights into the relative performance of these two local treatment approaches.











