
Purpose
Non-melanoma skin cancer (NMSC) incidence has become a significant clinical burden worldwide, with a continuously increasing number of diagnoses across different age groups and geographical areas. The growing incidence, along with the progressive aging of global population, is contributing to a substantial impact on healthcare systems in terms of treatment demand, follow-up, and resource allocation [1, 2].
Traditionally, surgery has been considered the first choice of treatment, particularly for accessible lesions and in patients suitable for surgical procedures, provided that adequate margins can be achieved (which may vary greatly according to different histologies). However, recent international guidelines have progressively included radiotherapy among valid therapeutic alternatives, particularly in selected cases where organ preservation, functional outcomes, and cosmetic results are of primary importance [3-7]. Among radiotherapeutic approaches, interventional radiotherapy (IRT; modern brachytherapy) plays a pivotal role in the management of selected NMSC cases. Because of its intrinsic physical characteristics, this technique allows for a steep dose gradient, delivering high doses to target volume while sparing surrounding organs at risk and healthy tissues [8-11]. The high level of dose conformity and the ability to tailor treatment to irregular superficial lesions make it particularly attractive in anatomically complex areas. For these reasons in the last years, contact IRT (cIRT) has gained increasing clinical interest, both in terms of scientific production and practical implementation in dedicated centers [12]. Its non-invasive nature, short overall treatment time, and favorable toxicity profile, further contribute to the technique expanding use.
From interventional perspective, despite being often regarded as a low-complexity procedure, contact radiotherapy presents a non-negligible dosimetric complexity. The aim of this paper was to highlight the dosimetric complexity underlying contact interventional radiotherapy and to provide a detailed analysis of the factors influencing dose distribution and treatment accuracy.
Dosimetric comparisons between cIRT and external beam radiotherapy (EBRT), particularly VMAT, indicate that selected OAR dose-volume parameters may be numerically similar in specific planning comparisons; however, these techniques do not generate equivalent dose distributions. In contact skin brachytherapy, the high superficial dose and steep dose fall-off with depth may allow excellent sparing of deeper structures, whereas VMAT generally provides a more conformal and homogeneous dose distribution around the PTV, though often at the expense of a broader low-dose bath [13]. An important consequence is that the delivered dose inside the CTV is often superior to the nominal prescribed dose. Although prescription is defined at a specific depth, the high-dose region above the prescription line increases the mean CTV dose in IRT, reflecting an intrinsic dose intensification effect. In Figure 1, the schematic comparison between non-stereotactic EBRT and cIRT is presented [14-17].
Fig. 1
A) Dose distribution calculated using TG-43 algorithm. B) Schematic comparison of dose distribution in non-stereotactic external beam radiotherapy (EBRT) and interventional radiotherapy (IRT). Left: EBRT with relatively homogeneous dose delivery (delivered dose [DD] ≈ prescribed dose [PD]). Right: IRT with “rainbow” dose distribution and central dose escalation (DD > PD)
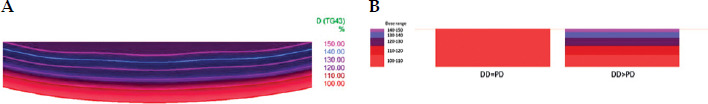
In Figure 1A, the real dose distribution of a cIRT implant is shown, while the dose distribution is schematically illustrated in the right CTV of Figure 1B, which may be referred to as “rainbow” dose distribution.
Beyond its dosimetric characteristics, cIRT offers important practical and clinical advantages. Owing to hypofractionated schedules, treatment can generally be completed within a short overall treatment time, improving patient convenience and compliance, particularly in elderly and frail patients, while optimizing healthcare resource utilization and potentially reducing costs. Moreover, excellent local control and cosmetic outcomes have been reported despite the use of lower total doses and fewer fractions than conventional EBRT.
The aim of this paper was to provide clinical suggestions with regard to cIRT using flaps and/or moulds to manage challenging anatomical scenarios, including the therapeutic window concept, the impact of target curvature on the therapeutic window, the role of bolus and air gap in dose distribution as well as the role of 3D-printed devices.
The maximum thickness of the target that can be managed by contact IRT: The “therapeutic window”
In cIRT, the maximum treatable target thickness is closely related to the concept of the therapeutic window, defined as the volume included between the therapeutic isodose (100% of the prescribed dose) and an upper dose limit. Although a 150% isodose is frequently used in clinical practice, no universally accepted upper threshold has been established for contact skin brachytherapy, with values reported in literature ranging from approximately 120% to 200%, depending on clinical setting and institutional practice [18].
International recommendations emphasize careful control of high-dose regions in superficial brachytherapy to preserve cosmesis and limit side effects. According to contemporary practice patterns and consensus guidelines, the prescription depth in skin surface brachytherapy is commonly limited to approximately 3-5 mm [19-22]. Due to the underlying steep dose gradient in brachytherapy, increasing the prescription depth to adequately cover thicker lesions may result in excessive superficial doses (> 150%), thus narrowing the therapeutic window. This concept is illustrated in the dose distribution shown in Figure 2A, where the 100% (purple line) and 150% (red line) isodoses define the effective therapeutic region.
Fig. 2
A) Examples of different widths of the therapeutic window (distance between 100% isodose in red and 150% in purple). In the right arrangement, dwell times of the upper layer channels are longer compared with the lower layer catheters. B) Schematic representation of the variation of the therapeutic window in a multilayer interventional radiotherapy configuration
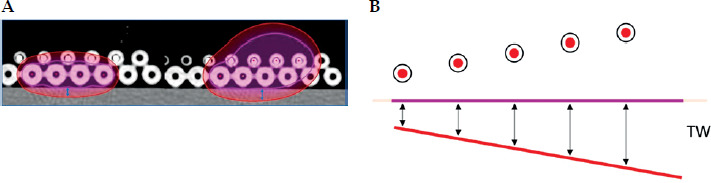
By modulating the source-to-skin distance, the dose distribution can be re-shaped. Multilayer intensity-modulated cIRT increases the distance between sources and the skin surface, reducing superficial hotspots, and shifting the high-dose region deeper. As presented in Figure 2, this configuration enlarges the region between the 100% and 150% isodoses, expanding the therapeutic window effectively. The geometrical rationale of this approach is schematically illustrated in Figure 2B: increasing the source-to-skin distance modifies both isodose depth and coverage. This strategy may allow treatment of targets thicker than 5 mm while maintaining acceptable superficial dose constraints, thus “stretching” the therapeutic window in cIRT (100% isodose line in red, 150% in purple).
Additional dosimetric investigations have demonstrated that customized superficial moulds with thicknesses ranging from 5 mm to 20 mm may provide adequate coverage of lesions up to 10 mm deep while improving dose homogeneity and reducing superficial hotspots, thereby potentially expanding the therapeutic window [23].
For lesions exceeding the conventional thickness limits of superficial IRT, interstitial or combined interstitial–surface mould techniques can be considered to achieve adequate target coverage while maintaining acceptable dose distributions [24].
The impact of the target curvature on the therapeutic window: The “Nautilus effect”
The curvature of the target to be covered has a significant impact on the therapeutic window. According to so-called “Nautilus effect”, a spatial relationship between the 100% and 150% isodoses changes as a function of surface geometry, i.e., a convex target needs a concave mould or flap that leads to a broader therapeutic window [25].
From dosimetric perspective, surface curvature directly influences source-to-target distance and dose fall-off, as previously reported in both contact and intra-operative HDR brachytherapy settings [26-29]. In convex geometries, the relative proximity of applicator to the central portion of target and the divergence of isodoses lead to a compression of the region between 100% and 150% lines, increasing the risk of superficial hotspots. Conversely, in concave geometries, the isodose distribution tends to “expand” inward, increasing the distance between the therapeutic and maximum allowed isodoses.
This behavior is clearly visible in the real dose distributions shown in Figure 3A and B, where concave configurations demonstrate a broader region between the purple (100%) and red (150%) isodoses compared with convex ones. The graphical representation schematically illustrates this phenomenon: for the same nominal prescription depth, curvature modifies the geometric spacing between isodose lines, effectively enlarging or narrowing the therapeutic window.
Fig. 3
A) Different values of therapeutic windows according to surface curvature (dwell times are the same for the channel in the two curvatures). B) Schematic illustration of the therapeutic window (TW) variation according to target curvature (100% isodose line in red and 150% in purple)
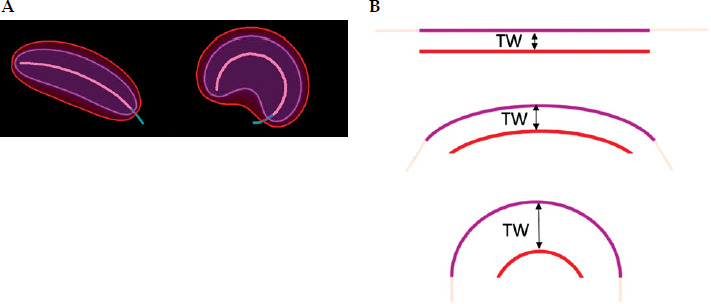
Therefore, target curvature represents an intrinsic geometric determinant of dose distribution in cIRT. Although often underestimated in clinical routine, it can significantly affect coverage and toxicity balance, reinforcing that contact brachytherapy, even in superficial settings, presents a relevant dosimetric complexity.
Previous dosimetric studies have confirmed that even small variations in applicator positioning, mould geometry, and source-to-skin distance can substantially alter dose distribution, emphasizing the importance of accurate mould fabrication and applicator placement in cIRT [30]. Given the marked dosimetric influence of surface geometry, customized mould applicators should be considered for anatomically challenging and highly curved sites, such as the nose and earlobe, in order to improve target coverage, dose homogeneity, treatment reproducibility, and overall dose conformity [31, 32].
The role of bolus and air gap in dose distribution
For small superficial targets located close to critical organs at risk (OARs), the use of bolus can have a clinically relevant impact on dose distribution. By modifying the build-up region and increasing the source-to-surface distance, bolus can re-shape high-dose region and potentially improve target coverage while reducing excessive dose to adjacent OARs [33].
In cIRT, dose calculation formalism plays a crucial role in evaluating this effect. The TG-43 formalism assumes a homogeneous water medium and does not account for tissue heterogeneities, air gaps, or shielding effects, which may be particularly relevant in head and neck regions. In contrast, model-based dose calculation algorithms (TG-186) incorporate heterogeneity corrections and provide a more realistic representation of scatter conditions and material interfaces [34-38].
When calculated with TG-43, the dose appears more uniform and less sensitive to the presence of bolus or tissue inhomogeneities. Conversely, TG-186 calculations demonstrate measurable variations in isodose shape and extension, especially near air cavities and tissue interfaces, with potential implications for both target coverage and OAR sparing.
Air gaps between the applicator (or bolus) and the skin surface represent a significant geometric uncertainty in contact interventional radiotherapy. Even minimal separations can alter backscatter conditions and modify local dose distribution, particularly in anatomically irregular regions, such as the ear or nose. Small air gaps up to approximately 1 mm can be partially counter-balanced by the presence of bolus material, which restores backscattering conditions and mitigates dose loss at the skin interface [39]. However, this compensation is not uniform and depends on the exact size and localization of the gap. Experimental and clinical dosimetric analyses have shown that air cavities can lead to localized dose reductions, especially at the interface between the applicator and the target (values reported in literature range from 1% to 10%) [40-44].
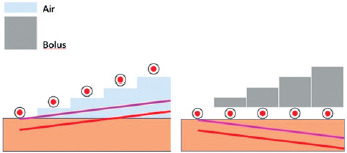
The graphical representation in Figure 4 schematically illustrates how the introduction of bolus shifts the 100% and 150% isodoses, modifying the thickness of the therapeutic window, and spatial relationship between the target and nearby critical structures. In addition, it is shown that a localized air pocket can shift the 100% isodose away from the skin surface, creating a focal reduction of dose. Therefore, during plan approval, careful attention should be paid not only to global dosimetric parameters, but also to the exact spatial localization of potential air gaps. Even sub-millimetric separations may translate into clinically significant local dose variations in small superficial targets adjacent to critical structures. It should be noted that the schematic illustration in Figure 4 is intended only to provide a simplified representation of how air gaps, bolus, or missing catheter material may affect the dose distribution and the therapeutic window, and should not be interpreted as a quantitative representation of these effects.
Fig. 4
Conceptual representation of isodose lines in interventional radiotherapy with the presence of air gaps and bolus. Left: air gaps between applicator and tissue lead to dose reduction at depth. Right: absence of air gaps ensures more homogeneous dose delivery. Air is shown in light blue, bolus in grey, 150% isodose in purple, and 100% isodose in red
Advanced dose calculation algorithms represent a relevant step forward in reducing dosimetric uncertainties in cIRT. Conventional TG-43 formalism assumes a homogeneous medium and does not account for tissue heterogeneities, air gaps, or material interfaces, potentially leading to discrepancies between calculated and delivered dose, particularly in superficial treatments. In contrast, model-based approaches (e.g., TG-186) incorporate these factors, providing a more realistic demonstration of dose distribution, especially in anatomically complex regions, such as the head and neck. Dosimetric studies have reported that these algorithms can reveal variations in target coverage and organs at risk exposure, which are not obtained by TG-43 calculations [45, 46].
Recent developments in model-based and Monte Carlo-based dose calculation platforms have facilitated the clinical implementation of TG-186 recommendations, enabling more accurate patient-specific dosimetry and a more realistic characterization of dose distributions in complex and heterogeneous treatment geometries. These advanced computational tools can improve treatment optimization in cIRT, particularly in anatomically challenging scenarios where conventional TG-43 calculations may be insufficient [47, 48].
The emerging role of 3D-printed devices
The introduction of 3D-printed devices is progressively enhancing precision and treatment personalization in contact interventional radiotherapy. Patient-specific applicators allow for improved conformity to irregular anatomical surfaces, better reproducibility, and more accurate control of source-to-skin distance, thereby reducing uncertainties related to curvature and air gaps [49, 50]. Additive manufacturing may also support the use of biocompatible materials and the direct integration of catheter pathways within patient-specific applicators [51].
3D printing enables the design of customized geometries with pre-defined catheter channels and step-like multilayer configurations, allowing for precise modulation of dwell positions and depth distribution. This approach supports advanced intensity-modulated strategies and multilayer arrangements, aiming at optimizing the therapeutic window [52].
An additional advantage is the possibility of integrating different materials within the same device. High-density inserts or shielding components can be incorporated to selectively protect nearby OARs, particularly in anatomically complex regions, such as the head and neck [53]. The combination of personalized geometry and material heterogeneity represents a further step towards biologically and geometrically optimized dose delivery.
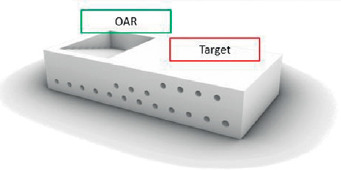
Therefore, 3D-printed applicators are not only technical tools but emerging platforms for precision brachytherapy, enabling tailored dose distribution and improved OARs sparing in superficial treatments [54]. An example of 3D-printed device is displayed in Figure 5.
Conclusions
Contact IRT enables advanced dose modulation and highly conformal dose distributions, which improve target coverage while preserving surrounding healthy tissues. Close collaboration between radiation oncologists and medical physicists is essential to optimize treatment planning and achieve optimal oncological outcomes with limited toxicity. The ongoing development of novel technologies, including model-based dose calculation algorithms and 3D-printed devices is expected to further enhance dosimetric accuracy and treatment personalization, especially in complex clinical scenarios.











