
Purpose
Cervical cancer is one of the most common gynecological cancers, with more than 600,000 observed cases and over 300,000 deaths worldwide in 2020 [1]. The current standard treatment for locally advanced cervical cancer is external beam radiotherapy concurrently with weekly cisplatin, followed by brachytherapy [2]. Brachytherapy remains an essential role in the treatment scheme due to its ability to deliver adequate dose required for favorable oncologic outcome without exceeding organs at risk (OARs) dose tolerance [3].
Brachytherapy technique has developed in the past several decades: from treatment planning in 2D orthogonal X-ray to image-guided adaptive brachytherapy (IGABT) with computed tomography (CT) or magnetic resonance imaging (MRI) guidance for 3D brachytherapy planning, as supported by the Gynecologic Groupe Européen de Curiethérapie-European Society for Radiation Oncology (GEC-ESTRO) Working Group [4]. A large multicenter cohort study showed that dose escalation using CT- or MRI-guided IGABT while respecting OAR constraints, achieved excellent local control and survival outcomes with low incidence of severe adverse events [5], which is consistent with results from our institution [6]. Moreover, similar favorable outcomes have been reported in the EMBRACE-I study, a prospective multi-institutional observational cohort study evaluating MRI-guided IGABT combined with concurrent chemoradiotherapy [2]. Not only IGABT allowed to deliver treatment to target adequately and accurately, it also resulted in better OAR assessment due to accurate OAR delineation and planning by using dose-volume parameters defined by GEC-ESTRO recommendation [7]. An analysis from a prospective EMBRACE study demonstrated that rectal dose-volume parameters (D2cc and D0.1cc) significantly correlate with late rectal toxicity [8]. Therefore, patients are advised to self-prepare their rectum by defecating before IGABT and taking prescribed medications, such as simethicone and sennoside.
Nevertheless, intraluminal gas in rectum is still frequently noticed during simulation, leading to increase of rectal volume and decrease of distance between the rectum and target volume. Protocol of intraluminal gas removal was established within the institution using Foley catheter based on the hypothesis that the diminishing of rectal distension may result in the improvement of rectal dosimetric parameters. Thus, the study purpose was to evaluate the dosimetric impact of intraluminal gas removal using Foley catheter in cervical cancer patients who underwent IGABT.
Material and methods
The study was designed as a retrospective study, and was approved by Siriraj Institutional Review Board, Faculty of Medicine Siriraj Hospital, Mahidol University (COA no. Si 518/2019).
Study population
Twenty treatment plans from 17 locally advanced cervical cancer patients, who received definitive concurrent chemoradiotherapy between January 2018 and May 2019, and had paired CT images before and after intraluminal gas drainage by Foley catheter, were randomly selected and included in the analysis. All patients received whole pelvis radiotherapy of 45-50.4 Gy in 25-28 fractions. IGABT was delivered with a prescribed dose of 7 Gy to HR-CTV for each fraction, and was administered once or twice weekly in four fractions. Patients underwent IGABT using Fletcher-Suit applicator or tandem-ring applicator (Varian Medical System, Palo Alto, CA, USA) at our hospital.
Simulation and CT image acquisition
During simulation, the patient was positioned horizontally, head first, with hands placed on thorax before CT image acquisition by CT simulator (GE Healthcare Systems, Milwaukee, WI, USA). For CT image before intraluminal gas removal, the patient was scanned 2 cm cranially from the tip of inserted applicator to pubic symphysis, with 2.5 mm slice thickness. For CT image after intraluminal gas removal, the patient was scanned 4 cm cranially from the tip of applicator to perineum, with 1.25 mm slice thickness. Both pre- and post-procedure images used the same pelvic exposure protocol, with tube potential of 120 kV and tube current of 180-250 mA depending on patient size, and were reconstructed in para-transverse plane for treatment planning.
Rectal intraluminal gas removal
The procedure was performed on a CT simulator couch without changing patient’s position. A 16-Fr Foley catheter was lubricated and inserted into the rectum. The catheter was then connected to a 50 ml disposable syringe, and the rectal intraluminal air was drawn into the syringe. Subsequently, the catheter was removed from the patient’s rectum, and the simulation process was resumed promptly.
Treatment planning
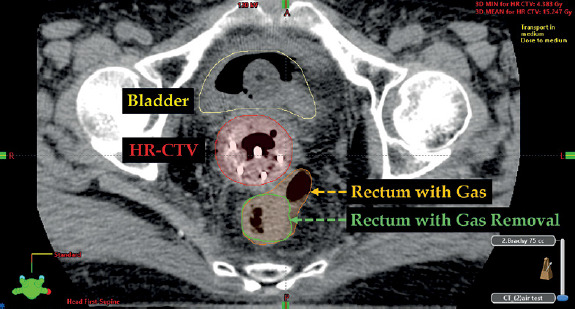
For treatment planning, both pre- and post-procedural CT images (CT_PRE and CT_POST, respectively) were sent to BrachyVision version 15.6 (Varian Medical Systems, Palo Alto, CA, USA) treatment planning system. Target volumes and OARs were delineated by radiation oncologist according to the GEC-ESTRO recommendations (Figure 1) [7]. Treatment plan was designed by medical physicist, so that the minimum dose delivered to 90% of high-risk clinical target volume (D90 HR-CTV) was 7 Gy, and the maximum dose at the 2 cm3 of rectal volume (rectal D2cc) and bladder volume (bladder D2cc) did not exceed 4.2 Gy and 6.0 Gy, respectively. Iridium-192 (192Ir) was employed as the brachytherapy source for IGABT [9]. Grid-based Boltzmann solver (GBBS) algorithm that accounts for heterogeneity corrections at the rectum-air interface was used for dose calculations. Dosimetry was conducted with a model-based dose calculation algorithm to enable more accurate assessment of rectal dose in the presence of air-tissue interface.
Data collection and statistical analysis
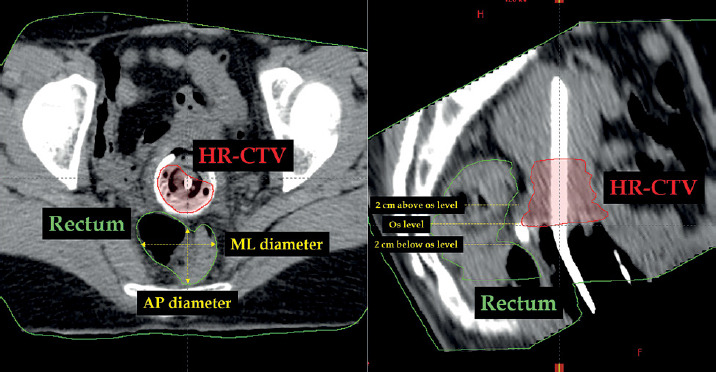
Rectum width in anterior-posterior (AP) and medio-lateral (ML) directions at 5 levels, including 2 cm upper, 1 cm upper, 1 cm lower, and 2 cm lower than the cervical os, and at the cervical os (Figure 2) were measured on pre- and post-procedural CT images. Distance from applicator surface to anterior rectal wall at the cervical os was also assessed on pre- and post-procedural CT images. Comparison of parameters between before and after intraluminal gas removal were performed to evaluate the procedure efficacy in the reduction of rectal distension from intraluminal gas.
Fig. 2
Rectal dimension measurement in anteroposterior (AP) and mediolateral (ML) directions at 2 cm above cervical os to 2 cm below cervical os
Dosimetric parameters of target volume and OARs, such as bladder and rectum were collected from treatment plan designed for both pre- and post-procedural CT images for comparison to evaluate the impact of the procedure on dosimetry and treatment planning. Target volume parameters assessed were the minimum dose received by 90%, 95%, 98%, and 100% of HR-CTV (D90, D95, D98, and D100 of HR-CTV, respectively). For OARs, parameters evaluated included the minimum dose in the most irradiated tissue volume of 0.1 cc, 1 cc, and 2 cc (D0.1cc, D1cc, and D2cc, respectively) of both OARs (rectum and bladder), according to Gynecological GEC-ESTRO Working Group guidelines [7].
All collected parameters were analyzed and presented as mean and standard deviations. Statistical comparison of the parameters between pre- and post-procedural data was performed using Student’s t-test at 95% confidence interval in Microsoft Excel 2013 (Microsoft Corporation, Redmond, WA, USA). P-value of less than 0.05 was determined as statistically significant. Ratio of plans’ parameters in pre-procedural imaging to post-procedural imaging was calculated for each case.
Results
The diameters’ comparison of the rectum in AP and ML directions at five locations referenced to the cervical os before and after the procedure is displayed in Table 1. The procedure significantly reduced the diameter of the rectum in ML direction at all other levels, from the level of 1 cm above the cervical os to 2 cm below the cervical os. Furthermore, it significantly reduced the AP rectal diameter at the level of 1 cm above the cervical os. However, there was no significant difference of the distance between the inserted applicator surface and the anterior wall of the rectum before and after the procedure (1.03 ±0.85 cm vs. 1.17 ±0.87 cm, p-value = 0.539). This indicated that intrarectal gas can significantly affect the rectal diameter, mostly in ML direction, and the removal of intrarectal gas leads to a significant reduction of rectal diameter.
Table 1
Comparison of rectal dimension and distance from the anterior rectal wall to the applicator surface between prior and after intrarectal gas removal
The dosimetric parameters of HR-CTV, bladder, and rectum based on treatment plans for pre- and post-procedural CT images are presented in Table 2. There was no statistically significant difference in any HR-CTV dosimetric parameters between pre- and post-procedural plans. The dosimetric parameters of the bladder were also comparable between pre- and post-procedural plans. Therefore, the intrarectal gas did not substantially affect the target dose coverage or dose received by the bladder. In contrast, all rectal dosimetric parameters (D0.1cc, D1cc, and D2cc) in pre-procedural plans were significantly higher than in post-procedural plans.
Table 2
Comparison of target and organs at risk dosimetric parameters between prior and after intrarectal gas removal
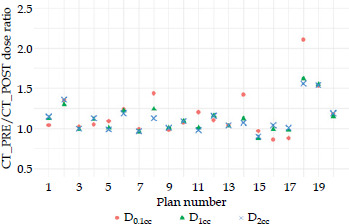
The analysis of rectal dose ratios between pre-procedural CT images (CT_PRE) and post-procedural CT images (CT_POST) is presented in Figure 3. Dose ratios ranged from 0.80 to 1.60, with majority of plans demonstrating values greater than 1.0. Across the cohort, D2cc and D1cc exhibited the least variability, whereas D0.1cc showed the greatest interpatient variability, likely reflecting the increased sensitivity of smaller high-dose rectal volumes to the presence of rectal gas.
Discussion
Rectal gas is one of the components that can increase rectal volume and result in rectal distention. Prior dosimetric study from the US revealed that increased rectal distention significantly correlated with an elevated D2cc [10]. The minimum dose in the most irradiated rectal volume, such as D0.1cc and D2cc has a significant association with rectal morbidity in cervical cancer patients treated with concurrent chemoradiotherapy and MRI-guided adaptive brachytherapy [8]. The escalation of these parameters leads to an increased rate of proctitis, rectal bleeding, rectal fistula, and overall rectal morbidity [8]. Therefore, reduction of these parameters decreases the occurrence of rectal toxicity events.
Consequently, an approach to reduce rectal gas during brachytherapy has been investigated with the objective of reducing the dose delivered to the rectal wall. A French single-center study, including 23 patients treated with 35 brachytherapy fractions, demonstrated that active gas evacuation using a rectal emptying tube significantly reduced the mean rectal volume and substantial D0.1cc and D2cc reduction [11]. Another single-center study from the US among 15 cervical cancer patients treated with 21 fractions of brachytherapy, showed that rectal gas drainage via rectal tube in patients with rectal diameter larger than 4 cm in HR-CTV-adjacent region can significantly reduce all rectum’s dose parameters, including D0.1cc, D1cc, and D2cc [12]. The results from both the studies are similar to the current one, where rectal gas removed by Foley catheter resulted in lower rectal D0.1cc, D1cc, and D2cc. This demonstrates that rectal gas has a significant effect on rectal dose parameters, while rectal gas drainage by applying Foley’s catheter into the rectum is still efficient as the standard rectal tube. This supports the recommendation of EMBRACE-II protocol that rectum should be deflated by catheter if significant gas is noticed during simulation process [13].
The fundamental and easiest concept is the rectum to be as empty as possible, since the increase of rectal volume is associated with higher rectal dose parameters, such as D0.1cc, D1cc, and D2cc [14]. Therefore, patient rectal preparation has an essential role in reducing rectal volume by emptying the stool prior brachytherapy session. However, a study of two pre-brachytherapy self-administered fleet rectal enema investigating rectal filling reduction in 20 cervical cancer patients who underwent intracavitary brachytherapy, did not demonstrate rectal volume reduction or dosimetric benefit on rectal dose parameters [15]. Likewise, the ineffectiveness of fleet enema was mentioned in the EMBRACE-II protocol, which does not recommend using an enema [13].
Other interventions were also explored to reduce rectal dosimetric parameters by displacing the rectum from the applicator, leading to lower dose to the rectum. Intravaginal techniques, such as vaginal packing, rectal retractor insertion, or intravaginal balloon, distend vaginal posterior wall and increase the distance between applicator and rectum. A single-center Canadian retrospective study of cervical cancer patients treated with tandem and ring applicator, which reviewed 377 brachytherapy fractions with rectal retractor insertion and 86 fractions with vaginal packing, showed that rectal retractor resulted in lower rectum D2cc compared with vaginal packing [16]. Another small prospective study in Canada among 11 patients treated with tandem and ring applicator, in whom rectal retractor blade, vaginal gauze packing, and a tandem Foley catheter were applied, also demonstrated that rectal retractor can significantly lower rectal and sigmoid dose compared with the other two techniques [17]. However, a single-center retrospective study from Japan reviewed 50 patients treated with tandem and ovoid applicator who had rectal retractor insertion and vaginal packing at least one fraction, and demonstrated that vaginal packing had a better rectal and bladder dosimetric parameters then rectal retractor insertion [18]. Although a large volume vaginal packing leads to further reduction of rectal dose, a retrospective study in Serbia with 40 patients treated with Fletcher-Suit applicator revealed that vaginal packing volume exceeding 25.6 cm3 can cause inadequate dose coverage in vaginal mucosa included in CTV [19]. While another prospective trial in India among 40 patients treated with tandem and ovoid applicator, using bladder-rectum spacer balloon in one fraction and vaginal gauze packing in another one, reported a significant reduction of rectal dose parameters in spacer balloon arm compared with vaginal packing arm [20]. Some studies on combining vaginal packing with intravaginal balloon [21] or rectal retractor [22] demonstrated lower rectal dose parameters compared with vaginal packing alone. Nevertheless, there is still no evidence-based consensus on determining the best intravaginal procedure to reduce rectal dose, and these methods may cause patient discomfort due to distended vaginal wall; the current EMBRACE-II protocol mentions only the conventional vaginal gauze packing [12].
Another concept in increasing the distance between applicator and rectal wall to expand the distance between posterior vaginal wall and anterior rectal wall is using a hydrogel spacer. A Japanese study with 36 patients treated by gynecological brachytherapy revealed a significant reduction of rectal D0.1cc and D2cc after receiving perirectal hyaluronate gel injection compared with pre-injection CT-simulated images of treatment plan [23]. Another Japanese study comparing 42 patients treated with hyaluronate gel injection into rectovaginal and vesico-uterine fossa with 42 patients without gel injection, demonstrated that the injection group had higher HR-CTV D90 doses compared with non-injection group, with tolerable rectal and bladder D2cc values [24]. However, the hyaluronate gel injection is invasive and may increase treatment cost, since it requires re-injection in every fraction due to the gel’s rapid absorbance.
Despite the efficiency of rectal gas removal by Foley catheter in dose parameters of the rectum, the current study has some limitations, including its retrospective nature, which may have influence selection bias. The study was the dosimetric comparison of treatment plans in CT images before and after rectal gas drainage, and was unable to assess the clinical benefit of the procedure. However, it is unethical and unjustified to randomize patients with substantial amount of rectal gas to control group without gas drainage, since there is evidence that larger rectal volume result in worse rectal dose parameters [10], and higher rectal dose parameters lead to an increase of rectal morbidity [8]. Notably, a higher rectal dose parameters were observed in post-procedural images of some plans, as reflected by dose ratios of less than 1 (Figure 3). This finding may be attributable to individual variations in rectal anatomy. Despite the removal of intrarectal gas, changes in rectal dimension may lead to a displacement of the anterior rectal wall closer to the target volume, which warrants further investigation. Moreover, dose parameters obtained from dosimetric study may not reflect the actual dose at rectum, which may require in vivo dosimetry to obtain the accurate dose. This should however be done with caution, because the probe can push the rectum closer to the high-dose region, resulting in escalation of dose to rectum [25]. The image obtained during simulation process might not accurately represent the anatomy during treatment delivery, since there is a substantial time gap between simulation and treatment delivery. The proximal bowel filling or gas might move distally into the rectum, leading to increased rectal volume compared with the rectum during simulation. Therefore, in-room imaging before treatment delivery may be required to ensure that the rectum is still empty or the filling is similar to simulation imaging. Lastly, the study included only patients treated with intracavitary brachytherapy, and further studies are required to validate these findings in interstitial brachytherapy cases.
Conclusions
In summary, Foley catheter placement in rectum was proposed as a method to remove rectal intraluminal gas in cervical cancer patients during brachytherapy. The comparison of CT images obtained during pre- and post-drainage reveals a significant decrease in rectal diameter in ML dimension without substantially affecting AP dimension and rectum–applicator distance. Also, the dosimetric comparison demonstrates a significant decline of rectal dose parameters after the procedure without changing HR-CTV dose coverage or bladder dose. The procedure should be applied in patients with remaining rectal gas after rectal self-preparation, because it is a simple, inexpensive, and minimally invasive procedure.











