
Purpose
Uveal melanoma (UM) is the most common primary intra-ocular malignancy in adults, and ruthenium-106 (106Ru) brachytherapy represents a well-established treatment option. However, following radiation treatment, up to 70% of patients are expected to develop some form of side effects, which can finally compromise the visual outcome [1]. In anti-vascular endothelial growth factor (anti-VEGF) era, the non-invasive diagnosis of initial stages of radiation maculopathy (RM) is crucial for the prompt implementation of treatment in high-risk patients to maintain their best possible visual acuity (VA) [2].
Pathogenesis of RM remains unclear; although it resembles diabetic retinopathy, ischemic damage to the retina and choroid cannot be reversed. Therefore, treatment aims only at prolonging the best VA as long as possible.
According to recent studies, choroidal damage may precede the appearance of retinal signs. It has been suggested that radiation can induce changes similar to the clinical spectrum of choroidal neovascularization (CNV), polypoidal choroidal vasculopathy (PCV), or retinal angiomatous proliferation (RAP) [3]. However, possible neuro-inflammation may also play a role before the onset of RM, with hyperreflective foci (HRF) visible on optical coherence tomography (OCT) scans [4, 5].
Radiation maculopathy diagnosis has been primarily based on fundus examination, fluorescein angiographic data, or OCT findings. Numerous studies have investigated the role of OCT angiography (OCTA) in early detection of RM, and most indicate that OCTA is the most sensitive tool for detecting early signs of RM, including vascular dropout in superficial and deep capillary plexi, and foveal avascular zone enlargement [6-8]. But whether OCTA is superior to OCT alone in the clinical setting is still a debate.
The aim of the study was to retrospectively evaluate the early OCT signs of RM, and to review 5-year outcomes in terms of VA following radiation treatment.
Material and methods
Medical charts of patients who underwent 106Ru plaque brachytherapy for uveal melanoma in the ocular oncology service between 2013-2019 were retrospectively reviewed. Exclusion criteria were co-existing macular or choroidal pathology, central localization of the tumor (involving the foveola), tumor located in the iris, or loss to follow-up.
All patients underwent 106Ru plaque placement under general anesthesia with muscle disinsertion in all cases, while for tumors located in the macula, eccentric plaque placement technique was employed. Extra-ocular muscles during plaque brachytherapy were temporarily disinserted for proper positioning of radioactive plaque. It protects the muscles from localized radiation damage, achieving optimal tumor coverage and safe positioning of the plaque. In all cases, concave applicator B (CCB) plaque was used, whereas radiation protocol aimed to deliver 80-120 Gy to tumor apex. Post-operatively, patients attended follow-up visits at 7 days, 4 weeks, and then every 6 months. On every follow-up visit, a full ophthalmic examination was performed, including VA assessment (Snellen chart), anterior and posterior fundus examination, color and autofluorescence fundus photographs (Topcon, TRC-50 DX), ultrasound (Eye Cubed, Ellex), and OCT scans (SD-OCT, Zeiss Cirrus 4000, 6 mm and 5-lines cross sectional scans, and Triton Topcon, 9 mm radial scans).
Data were collected at specific time points: before treatment, at 6 mts, 12 mts, 18 mts, 24 mts, 36 mts, and after 5 years (60 mts). The analyzed OCT parameters included: 1. Central retinal thickness (CRT), measured manually perpendicular from internal, limiting membrane to retinal pigment epithelium-Bruch membrane’ complex layer in the center of sub-foveolar region; 2. Presence and vertical diameter of the biggest intraretinal cyst (IRC) in the macular region; and 3. Presence of HRF within all retinal layers, and sub-dividing them to inflammatory (i-HRF) and exudative (e-HRF) types [4]. Since this study was retrospective in nature, all measurements were performed manually using OCT scans of an affected eye before brachytherapy as a reference. Horizontal scans centered in the fovea from every follow-up visit were considered for analysis (Figure 1). Vascular and pigmentary HRFs were deemed not relevant in terms of radiation changes and were not included in the final analysis [4].
Fig. 1
B-scan from SD-OCT showing cystoid macular oedema (yellow arrow) and example of HRS (blue arrows) after brachytherapy of uveal melanoma located in the superior-temporal quadrant
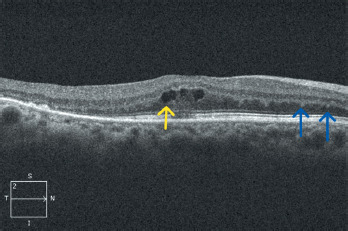
Inflammatory type of HRF was defined as discrete intraretinal reflectivity changes ≤ 30 µm in size, with reflectivity similar to nerve fibre layer and without back shadowing. Exudative type of HRF was described as > 30 µm in size, with high reflectivity similar to retinal pigment epithelium (RPE) [4]. Vertical diameter of the biggest IRC was measured manually.
Diagnosis of RM and implementation of treatment was considered an observation end-point.
All statistical analyses were conducted using Statistica software (version 14.1). To analyze the distribution of studied variables, Shapiro-Wilk test for normality was used to assess whether the data followed a normal distribution. A significance level of α = 0.05 was assumed, with p-value below 0.05 considered statistically significant. The study adhered to the Declaration of Helsinki and received a consent of the Internal Review Board (approval number: 758/20).
Results
Between 2013-2019, 186 eyes of 186 patients received 106Ru plaque brachytherapy due to choroidal and/or ciliary body melanoma at our institution. From this group, 51 (27%) patients were excluded due to co-existing macular pathology (10 patients), choroidal disease (1 patient), central localization of the tumor involving the foveola (33 patients), and loss to follow-up (7 patients). Finally, 135 patients met the inclusion criteria and were subjected to further analysis. The demographic data of patients are listed in Table 1.
Table 1
Demographic data of the patients and dosimetry parameters of 106Ru plaque brachytherapy
Eight patients had predominantly ciliary body melanoma with choroidal involvement, and 127 had strictly choroidal melanomas. The most common localization of the tumor was the temporal quadrant (49 patients, 36.3%). The median follow-up following plaque radiotherapy was 55 months (range, 7-123 months). The median tumor thickness was 3.56 mm (mean, 3.95 mm), and the median distance to the fovea was 3.7 mm (mean, 4.47 mm). The median scleral dose was 380 Gy to the sclera and 99 Gy to the tumor apex. The plaque dosimetry is shown in Tables 1 and 2.
Table 2
Relations between dosimetry parameters, tumor size (Mann-Whitney U test), and radiation maculopathy regarding final visual acuity (Spearman’s r correlations coefficient)
Radiation maculopathy developed in 63 patients (46.67%) in the median time of 24 months post-treatment (mean, 24.56 months; range, 2-63 months). On fundus examination, the most common symptoms of RM were macular edema (74.6%), retinal hemorrhages (28.6%), and hard exudates (15.9%). On OCT, an increased incidence of intraretinal cysts over time was observed, i.e., from 12 patients (8.9%) at 6 months follow-up to 36 patients (26.7%) at 24 months follow-up. The appearance of cysts correlated with the RM occurrence (from 12 months to 5 years), with p < 0.05 (Table 3). The size of cysts did not correlate with RM occurrence and was not statistically significant until 18-month follow-up (Table 3).
Table 3
Relation between cyst occurrence on OCT scans (Pearson’s chi-square test), size of the biggest cyst (Mann-Whitney U test), central retinal thickness changes (Mann-Whitney U test), hyperreflective foci (Pearson’s chi-square test), and radiation maculopathy occurrence during follow-up
The median CRT on OCT B-scans was greater at every follow-up visit in eyes with RM compared with those without RM, reaching statistical significance at 12- and 60-month follow-up (p < 0.05) (Table 3).
The analysis of HRF occurrence at check-up points revealed a significant association with the presence of RM, from 6 months follow-up and throughout the entire follow-up period (χ2 test, p < 0.05) for both inflammatory and exudative types of HRF (Table 3).
Radiation maculopathy was not detected if the margin of tumor from the foveola was 9.84 mm or more. The tumor’s distance to the foveola had an impact on RM development (p < 0.05) but did not correlate with final VA (p > 0.05).
Moreover, doses to the apex of the tumor and to the sclera as well as tumor size correlated with the occurrence of RM after brachytherapy. Doses to the sclera and tumor thickness were associated with the final VA (p < 0.05) (Table 2).
The incidence of RM was not related to gender, patients’ age, other co-existing diseases (i.e., hypertension, diabetes mellitus, cardiovascular diseases, anticoagulants drugs intake, previous general, or ocular surgeries), and co-existing ocular diseases, such as conjunctiva lesion, strabismus, history of iridis or episcleritis, ocular hypertension, glaucoma, or amblyopia (Pearson’s chi-square test, p > 0.05).
Most of the patients received some form of treatment for RM, including anti-VEGFs injections in various schemes (46%), sub-Tenon injections of steroids (11%), or laser therapy (6%), while several patients did not show any improvement in VA due to sub-foveal photoreceptor loss.
The final visual outcome at 5-year follow-up was up to 0.1 for 23 patients (34%), between 0.1 and 0.5 for 15 patients (22%), and better than 0.5 for 29 patients (43%). For 31 (46%) cases, it dropped 3 lines or more at Snellen chart at 5 years follow-up. The mean VA at presentation was 0.72, and VA at last control was 0.49 (for all cases); 35 patients (26%) developed metastases and 55 patients (41%) died during follow-up.
Discussion
Radiation maculopathy is a vision-threatening complication following 106Ru plaque brachytherapy for uveal melanoma. With the current available treatment techniques, there is no agreement in the literature on when and how to treat early symptoms of RM to maintain the best possible VA of the patient.
The incidence of radiation retinopathy (RR) after brachytherapy for uveal melanoma varies widely among studies (n = 3), between 8% for proliferative RR and 42% for non-proliferative RR at 5 years (n = 9), with the median time of onset of symptoms at 21 and 32 months, respectively [9-11].
The established risk factors related to the development of non-proliferative RR are tumor margin of less than 4 mm from the foveola, tumor limited to the choroid, and radiation dose greater than 260 cGy/h to the tumor base [9, 12]. Risk factors for proliferative RR are among others, such as tumor base diameter greater than 10 mm and diabetes mellitus [9, 12, 13]. Also, female sex and tumor height are associated with the increased risk of RR [14].
In our cohort, 12.7% of patients developed RM up to 1 year post-irradiation, 44.4% at 2-year follow-up, and 71.4% by 3-year follow-up. This was related to the tumor size, plaque dosimetry, and distance to the foveola. These findings are consistent with other reports [9, 13], and the median time to the onset of symptoms at 24 months in our group is also in line with other studies [9-11].
Interestingly, we found that RM did not occur more frequently in any gender and over the age of 50, which is in contrast with other authors [11, 14]. Similarly, the RM occurrence in our group was not related to co-existing diseases, such as hypertension, diabetes mellitus, and cardiovascular diseases) [9, 15, 16].
In our study, we demonstrated that OCT-derived metrics, including CRT, cysts occurrence, and HRF incidence were altered in irradiated eyes over time. The size of the cyst was not statistically significant, but we did not investigate the response to treatment of RM in this study. However, in the literature, cysts play a significant role as the basis for RR multimodal imaging classifications [17-19], and cysts occurrence allowed separation of treatable edematous components of RM from irreversible atrophic counterparts. The vertical size of the biggest intraretinal cyst on OCT scans has been associated with poor prognosis of VA [19], whereas cysts’ changes over time have been considered as biomarker of poor VA also after anti-VEGF therapy [20].
Hyperreflective foci or hyperreflective dots (HRDs) have been observed in various retinal diseases, such as age-related macular degeneration, diabetic macular edema, retinal vein occlusion, central serous chorioretinopathy, macular telangiectasias, retinal dystrophies, or uveitis. They were defined in various manner, assuming that they are accumulations of lipofuscin or lipid deposits due to breakdown of blood-retina barrier (exudative type) or microglia cells or macrophages (inflammatory type), and detected throughout the retina layers [4, 21-23]. In addition, HRFs were considered as biomarkers of retinal inflammation after brachytherapy, leading to the development of RM. HRF progressively and significantly increased in number after irradiation, reflecting the appearance of ME after brachytherapy [5]. In our study, we noticed that HRFs were associated with RM throughout the observation period and both, i-HRF and e-HRF occurrence was statistically significant, even before cystoid changes. However, the results should be interpreted with caution due to the retrospective setting of the study and different devices used.
Central retinal thickness was increasing in the irradiated eyes during follow-up (Table 3). In the study by Mashayekhi et al., the increased central macular thickness of > 10 μm without cystoid changes was common in eyes with uveal melanoma before and at 4 months after plaque radiotherapy, and it was associated with larger tumor size. Therefore, it was suggested that tumor-related factors, most likely mediated through pro-inflammatory cytokines, may play a significant role in post-radiation macular edema, while those eyes with early sub-clinical macular edema, are at significantly higher risk for future cystoid macular edema (CME) [24]. Our observations are in line with that suggestion.
The limitations of the study are mostly related to its retrospective nature, imaging acquisition, and image resolution, which was changing over time.
Conclusions
In summary, there are many factors influencing the development of RM. Radiation maculopathy increases with doses to the sclera and apex of the tumor, and tumor size and distance to the foveola. OCT scans are convenient in the detection of early signs of RM. The presence of HRF and cysts have the greatest diagnostic value as they are the first signs of RM observed on OCT scans.











