
Introduction
Asthma is a common chronic respiratory disease that affects both children and adults. According to the Global Burden of Disease study, in 2019, approximately 262 million people worldwide were affected by asthma, and the disease was responsible for 455,000 deaths [1, 2]. Chronic obstructive pulmonary disease (COPD) is another common chronic respiratory disease affecting approximately 12.6% of the adult population over 40 years of age [3]. Furthermore, it is predicted that the number of estimated COPD cases will increase to 592 million by 2050 [4]. The most relevant measure to prevent and treat COPD is smoking cessation, while the pharmacological treatment of the disease is based on bronchodilators and anti-inflammatory agents used in the form of inhalation.
Inhaled drugs are also the cornerstone of asthma treatment. The number of patients using inhaler medications is gradually increasing – it is estimated that globally, more than 1.2 billion inhalers are purchased for asthma and COPD annually [5]. The right choice of the medication and the inhaler device is critical for achieving successful management in both diseases [6, 7] and is a compromise between choosing the right active substance, the optimal inhaler, patient preferences, potential side effects, treatment costs, and environmental concerns on sustainability [8]. Management guidelines for asthma and COPD emphasise that choosing the right inhaler should be a collaborative decision between the patient and their healthcare professional (HCP) [6, 7]. Adequate treatment efficacy may be achieved only with proper inhaler use and is enhanced by the patient’s satisfaction with the inhaler. The dosage of inhaled medications, particularly in asthma, can vary depending on the severity of symptoms or disease control, but it has been shown that for optimal treatment effectiveness, it is best to use one fixed type of inhaler [9] and refrain from changing the type of inhaler device without medical justification.
Several statements or guidelines advise against medically unjustified inhaler switch in patients who are stable on their current medication. Treatment modifications may include brand-to-brand and brand-to-generic change. One of the most common reasons for switching inhalers not related to clinical indications is the cost of the treatment [10–12]. Another reason for inhaler switch a search for more environmentally friendly devices [5, 13, 14]. However, as many authors emphasise, the choice of the optimal inhaler should be dictated merely by medical indications – safety and effectiveness of treatment, and economic and environmental factors should play a secondary role [15–17].
INHALED DRUGS COMPRISE NOT ONLY THE ACTIVE SUBSTANCE BUT ALSO THE INHALER
Inhaled medications must be taken properly to achieve the anticipated therapeutic effect. Delivery directly to the airways and an adequate pulmonary deposition is the prerequisite for a rapid onset of action and a reduction of the risk of systemic adverse reactions [18, 19]. The choice of the inhaled medication should be based not only on the selection of the right active substance, but also on matching an optimal inhaler device to the individual patient. Even the most advanced therapeutic molecule will not achieve its full effect if it is not effectively delivered to the lower respiratory airways [20]. Improper inhalation technique is associated with a higher risk of exacerbation and higher risk of hospitalisation, worse disease control and quality of life, and an increased frequency of treatment-related adverse effects [6, 7, 21–23] what may ultimately lead to increased use of oral corticosteroids and antibiotics [24]. It has been shown that many patients with asthma or COPD make numerous inhalation mistakes – the proportion of patients making inhalation errors ranges from 25% to 80% [21, 25, 26].
There are currently 3 main types of inhalers available on the market: 1) dry powder inhaler (DPI), 2) pressurized metered-dose inhaler (pMDI), 3) soft mist inhaler (SMI).
These inhalers differ in the way the aerosol is generated and differ in the inhalation technique. There is no single perfect inhaler for all patients. Some of the inhalation errors that patients make are specific to the type of inhaler, and so they may be eliminated by choosing the right inhaler device. A number of algorithms for choosing the right inhaler for the individual patient have been proposed and the factors that need to be taken into account in this procedure have been well described [20, 27, 28]. The basic issue is to assess the ability to operate the inhaler and to generate an appropriate inhalation force. All devices require a minimal inhalation flow to deliver the drug successfully into the lungs [27]. In this regard, a lower inspiratory flow is necessary for pMDIs (10 l/min) than for DPIs, with the optimal flow for DPIs varying considerably between devices (20–60 l/min) [29]. About a third of COPD patients using DPIs do not achieve the peak inspiratory flow (PIF) values required for their daily inhaler, and a suboptimal PIF is associated with worse health status [30]. Other patient-dependent factors that need to be taken into account, particularly in the elderly population, are cognitive function, manual dexterity, hand strength, coordination of actuation and inhalation in order to deliver the adequate medication dose [20].
Indications for inhaler switch
In some patients, the need for inhaler switch may be due to clinical factors, specifically due to the need to change the active substance which may only be available in a different type of inhaler than used by the patient. In patients with poor asthma control and in patients with COPD with frequent exacerbations, it is crucial to assess inhaler competence. As the GINA report recommends – in patients with incomplete asthma control, the correctness of inhalation technique is mandatory before intensifying treatment [7]. A significant proportion of patients may reduce the number of inhalation mistakes after inhalation technique training and may not require a change in the medication [31].
A change of inhaler should be considered in patients who, despite training in inhalation technique, still make inhalation errors. Critical errors, i.e. those that affect the lung deposition of inhaled drug, resulting in little or no medicine being inhaled or reaching the lungs, are particularly important [21]. A higher number of critical errors correlates with poorer asthma control and more frequent COPD exacerbations [21]. Modification of treatment should also be considered in patients using several types of inhalers at the same time, what increases the risk of inhalation errors and their types [32]. It is recommended to use as few inhalers as possible, and, if the use of more than one inhaler is necessary, treatment via the same type of inhaler (MDI vs. DPI vs. SMI) is strongly advocated. However, despite the availability of dual- and triple-therapy inhalers on the market, a considerable number of patients with asthma and COPD are still treated with multiple devices [33]. If a patient is currently taking inhaled therapy and is able to use his/her current device correctly, new therapy should best be prescribed with the same device [6]. In Table 1, the pros and cons for switching inhaler devices with regard to medical reasons are presented.
TABLE 1
Arguments for and against switching inhalers
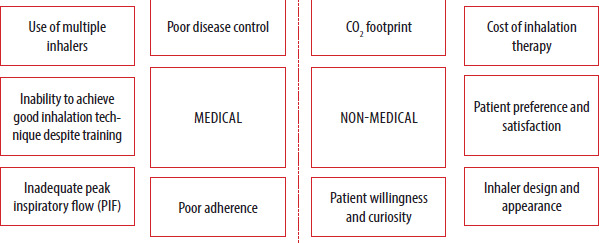
The introduction of generic equivalents to branded inhalers is expected to offer economic benefit, however it may be offset by worsening the course of the disease due to improper inhaler use, reduced adherence, and, by consequence, worse disease control [34, 35]. Often, an inhaler switch is dictated by economic and environmental considerations. However, many studies have shown that an unjustified change can worsen disease control and thus increase treatment costs. In Spain, the impact of uncontrolled inhaler switching for non-clinical reasons in patients with COPD generated an annual estimated cost of EUR 923 per patient, leading to an excess annual expenditure exceeding EUR 216 million. For asthma patients, the annual impact is almost EUR 263 per patient, accounting for an additional EUR 118 million annual expenditure. The environmental cost of such a switch, generated mainly by additional exacerbation-associated hospitalizations and GP visits, is also significant and is estimated to leave a footprint of more than 45,000 tCO2e [35]. This is in line with other reports. Principe et al. found that more frequent inhaler changes in patients with asthma correlated with more exacerbations [36] and Ekberg-Jansson et al. reported an increase in healthcare resource utilization among patients who had switched versus those who had not [37]. It is estimated that about 9% of COPD exacerbations may be attributed to switching inhaler devices [38]; other reports suggest that inhaler switch may have led to as much as 15.8% of hospitalizations [39]. Bjornsdottir et al. showed that the number of healthcare visits increased by 44% in 1 year following inhaler switch in patients with asthma or COPD [40]. A study by McCarthy et al. demonstrated that 17.2% of patients required a change of therapy due to worsened asthma control ≤ 12 weeks following switching [12]. In the review by Albanna et al., 6 of the 7 studies indicated that an unsupervised and unconsented inhaler switch in asthma patients resulted in worse disease control and had a negative impact on medication adherence or persistence [34]. Branded and generic medications must use bioequivalent, chemically identical compounds, but generic agents are not necessarily delivered by the same devices as the original branded drug [41]. Thus, between-brand differences in therapeutic effect may be observed for the same medicinal compound, driven by variations in the dose and particle size delivered to the lungs [34]. Switching from original drugs to generic drugs is common, but it is important to bear in mind that a vast majority of inhaler switches involve a completely different device with its own characteristics, administration and handling technique. Therefore, the process of switching inhalers requires a careful approach [42]. Patients have their own preferences regarding the appearance and shape of the inhaler, but factors also include ease of handling, choice of a once vs twice daily regimen, a short inhalation time, fast onset of action and low inhalation resistance [43]. The medical and non-medical reasons for considering inhaler switch are summarised in Figure 1.
When changing from a branded inhaler to a generic inhaler, the patient may receive the same active ingredient in a completely different inhaler – a specific DPI, can vary markedly in design and method of operation. As Pirozynski and Sosnowski emphasise, problems in obtaining good performance of generic DPIs are related not only to the correct duplication of the shape and working principle of the original device but also to the adjustment of the properties and stability of the powder which is required for proper quality of the released aerosol. Both aspects (device and formulation) are of equal importance [44]. A significant proportion of patients are not consulted or even asked for their consent when changing their inhaler [8]. Any patient who receives a new medicine should be re-trained on how to use the new inhaler correctly, which is particularly difficult if the patient is not aware of the change in treatment. To maintain the effect of training of proper inhalation technique, training sessions should be regularly repeated. As also emphasised by the recommendations and numerous authors, choosing the right inhaler requires checking the patient’s ability to use a given device. Both the GOLD and GINA reports emphasise the need for repeated training in the correct technique of inhalation during each medical visit [6, 7]. However, some healthcare professionals do not know how to take inhaled medications correctly. In such case, they are unable to adequately assess and teach proper inhalation techniques to their patients [45].
The patient’s acceptance of the treatment is one of the important factors affecting adherence to treatment, what, in turn, leads to better disease control. Patients’ approaches to generic drugs can vary. Some are positive about the expected lower treatment costs [46], however there are studies which show that asthma patients had negative perceptions of switching from brand to generic DPIs [47]. Patients who were offered to switch from DPI to generic DPI tend to have doubts about the usability, efficacy and their own ability to use the generic DPI correctly [48].
A change in treatment regimen requires presenting clear and comprehensive information about the change and acceptance of the new proposed treatment. Several studies showed that inhaler regimen switches could be detrimental to the patient-HCP relationship, especially when the switches were non-consented [8, 49]. Consented patients were also generally more satisfied with their switches than non-consented or partially consented patients [49, 50]. Proper inhaler selection improves patients’ concordance between recommended therapy and the patient’s behaviour. Concordance indicates a partnership between patient and healthcare provider, and implies that patients and clinicians work together [51, 52].
Changing the inhaler also raises concerns among physicians [53]. Peirce et al. reported that majority of clinicians negatively perceive switching the inhaler for non-medical reasons pointing to the necessity of additional clinician-patient communication, poor inhaler tolerance and concerns about worsening patient outcomes [53].
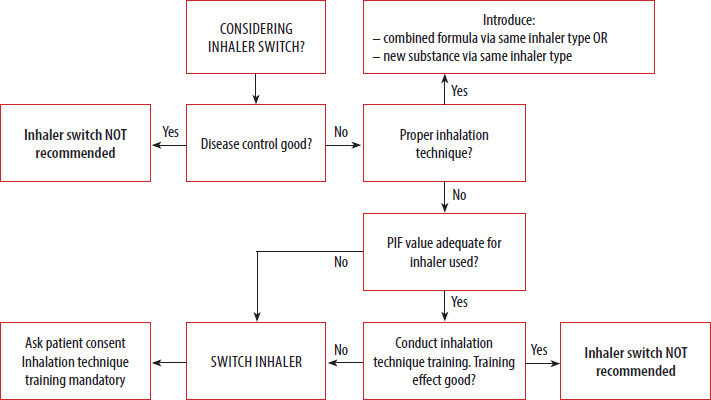
The basic elements to be considered in decision making on inhaler switch are depicted in Figure 2.
Legal issues of switching inhalers
Under Polish law, a person dispensing reimbursed medicines is obliged to inform the patient about the possibility of purchasing a reimbursed medicinal product different from the one prescribed, provided that it has the same international non-proprietary name, strength, and pharmaceutical form that does not cause therapeutic differences, is intended for the same indication is the same, and whose retail price does not exceed the public funding limit or the retail price of the medicinal product prescribed [54]. The current definition of ‘generic medicinal products’ is found in European Medicines Agency (EMA) Directive 2001/83/EC, Article 10(2)(b), which states that a generic medicinal product is a product that has the same qualitative and quantitative composition of active substances and the same pharmaceutical form as the reference medicinal product, and whose bioequivalence with the reference medicinal product has been demonstrated through appropriate bioavailability studies [55]. With regard to non-reimbursed medicines, reimbursement regulations do not apply; therefore, there is no statutory obligation for a pharmacist to inform the patient about generics for non-reimbursed medicines. However, as shown in the study by Drozdowska and Hermanowski, the majority of pharmacists in Poland always (40%) or often (46%) inform consumers about a generic option [56]. Importantly, the patient must always give consent to any change of medicine prescribed by the doctor.
Conclusions
Choosing the appropriate inhaled medication is crucial in the treatment of patients with asthma and COPD. Treatment outcomes depend not only on selecting the correct active substance, but also on choosing an inhaler that is suitable for the individual patient. Therefore, if good control of obstructive disease is achieved with given inhalers, any further change of inhaled therapy should be driven mainly by medical factors, such as the need to modify the active substance or situations in which the patient is unable to use the inhaler correctly despite proper training. Switching inhalers for non-clinical reasons frequently leads to poorer disease control and a higher frequency of exacerbations and hospitalizations. It may also be detrimental to the patient–healthcare professional relationship. Moreover, any expected economic benefits of switching inhalers should be perceived in the context of the costs associated with worsening disease control due to improper inhaler use and reduced adherence.











