
INTRODUCTION
Chimeric antigen receptor (CAR) T-cell therapy is a relatively new and innovative treatment that is increasingly being used in the management of hematologic malignancies derived from B lymphocytes and is currently being investigated for use in autoimmune diseases [1-3]. This therapy uses the patient’s own T lymphocytes, which are genetically modified to recognize a specific antigen on tumor cells. Binding of the CAR to its target antigen leads to T-cell activation, initiation of an inflammatory response, and subsequent tumor cell death. The modified T cells also retain the ability for in vivo expansion, enhancing their therapeutic effect. CAR T-cell therapy is associated with specific toxicities, the two most characteristic being cytokine release syndrome (CRS) and neurotoxicity, commonly referred to as immune effector cell-associated neuroto-xicity syndrome (ICANS). Both are linked to the cytokine storm that follows the activation of T lymphocytes [4].
ICANS is defined as a pathological process involving the central nervous system (CNS), developing after immune therapy, and resulting in the activation or engagement of endogenous or infused T-cells or other immune effector cells. The most common symptoms are aphasia, altered level of consciousness, cognitive impairment, motor weakness, seizures, and cerebral edema. Symptoms typically manifest between 4 to 9 days after infusion of CAR T-cell and last 5-13 days, although the spectrum of clinical presentation is highly variable in type and severity, but also in time of onset [4-7].
The mechanisms underlying CAR T-cell-related neurotoxicity remain incompletely understood. Some trials and clinical findings suggest that elevated cytokine levels and disruption of the blood-brain barrier likely play a role in its pathogenesis. Most neurologic symptoms are reversible; however, not all resolve completely [7, 8]. The incidence of ICANS following CAR T-cell therapy ranges from 37.5 to 77%. Reported risk factors include, among others, the pre-sence and severity of CRS, high blood cytokine levels (e.g., ferritin, interleukin-6 (IL-6)), high initial tumor burden as well as the type and dose of CAR T-cell product [7, 8]. CRS and ICANS are graded using the American Society of Transplantation and Cellular Therapy criteria, which define five levels of toxicity mainly based on clinical symptoms [4]. For grading ICANS, a particularly useful tool is the Immune Effector Cell-Associated Encephalopathy (ICE) score, a brief neurological assessment, evaluating orientation, ability to name objects, follow commands, writing a simple sentence, and counting backwards from 100 by tens. The ICE score provides a quick and structured method to assess encephalopathy severity in patients receiving CAR T-cell therapy [4]. Management of CRS and ICANS should be based on grades and may include supportive treatment and high-dose corticosteroids and/or biological agents such as tocilizumab (IL-6 receptor blocker) and anakinra (IL-1 receptor antagonist). Tocilizumab is recommended exclusively for CRS management, as it may exacerbate ICANS by increasing cyto-kine levels within CNS, likely due to its large molecular size, preventing blood-brain barrier penetration [8].
Here, we present a rare and unusual neurotoxicity case, manifested as transverse myelitis following CAR T-cell therapy.
Case description
A 45-year-old woman with primary mediastinal B-cell lymphoma was admitted to our department in May 2024 for CAR T-cell therapy. Her diagnosis, clinical stage IVB, was established in October 2023 based on histopatholo-gical examination of a mediastinal tumor specimen. She was treated with six cycles of R-CHOP (rituximab, cyclo-phosphamide, doxorubicin, vincristine, prednisone) chemotherapy but due to disease resistance, one cycle of R-ESHAP (rituximab, etoposide, cisplatin, cytarabine, prednisolone). Despite this, positron emission tomography–computed tomography (PET-CT) revealed disease progression, and the patient was subsequently qualified for CAR T-cell therapy with axicabtagene ciloleucel, in accordance with the National Health Fund therapeutic program criteria. Axicabtagene ciloleucel is one of the CAR T-cell products approved for the treatment of relapsed or refractory B-cell non-Hodgkin lymphoma.
Her medical history included hypertension, pericarditis (in 2011), thyroidectomy due to nodular goiter, overweight, gallstones, and bronchial asthma.
Lymphocyte collection for CAR T-cell manufacturing was performed on April 17, 2024. As bridging therapy (during the manufacturing period) she received R-COMP (rituximab, cyclophosphamide, liposomal doxorubicin, vincristine, prednisone) chemotherapy. There was no CNS involvement during the course of the disease. A PET-CT post-bridging therapy showed an active mediastinal mass.
Standard lymphodepletion with fludarabine and cyclophosphamide was administered from May 18 to May 20, 2024, followed by infusion of axicabtagene ciloleucel on May 23, 2024. From the time of infusion, the patient received prophylactic levetiracetam. On day +1 post-infusion, the patient developed Grade 1 CRS, managed with tocilizumab followed by dexamethasone, resulting in symptoms resolution (Table 1). By day +5, she presented typical signs of ICANS, Grade 4, with inability to speak or follow commands, and ICE score of 0/10 points. Brain CT scan revealed no abnormalities. She was transferred to the intensive care unit (ICU) and started on high-dose steroids, followed by anakinra due to worsening symptoms. Shortly after ICU admission, she experienced life-threatening prolonged seizures, requiring intubation and mechanical ventilation. Valproic acid was administered as part of anticonvulsant therapy.
Table 1
Course of treatment
By day +10 post-infusion, her condition improved and she was successfully extubated. After discontinuation of sedation, she presented with lower limb paralysis and loss of sensation. Neurologic examination revealed flaccid paralysis of the lower limbs without pathological reflexes, severe sensory disturbances from the T10 level and sphincter dysfunction. Additionally, she exhibited upper limb weakness (proximal 3/5, distal 4/5). Magnetic resonance imaging (MRI) of the thoracic and lumbar-sacral spine revealed abnormal signal from the T7 level down to the cauda equina, without pathological enhancement, indicative of myelopathy. The most pronounced abnormality was found at T7, where areas of increased signal were observed in the left anterior column, extending from T9 to encompass the entire cross-section of the cord (Figure I). The observed changes were characteristic of inflammatory circumscribed foci. Brain and cervical spine MRI were unremarkable.
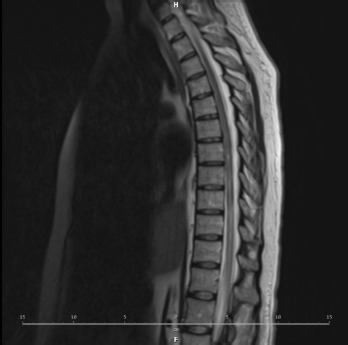
Lumbar puncture was performed, followed by a comprehensive cerebrospinal fluid (CSF) analysis, including routine examination (showed elevated protein level 0.89 g/l with normal cytosis), cytometric analysis, microbiological and meningitidis panels, virological tests, CSF culture, and oligoclonal band detection (all negative). Microbiological tests from plasma (HBV, HCV, HIV, CMV, EBV, aspergillus, HHV6/7, JCV) were also negative. No specific etiology of the myelitis was established, leading to a diagnosis of longitudinally extensive transverse myelitis associated with CAR T-cell therapy.
Acute transverse myelitis (TM) is a rare neurologic condition characterized by acute or subacute spinal cord dysfunction, resulting in paresis or complete paraplegia, sensory deficits, and autonomic dysfunction below the lesion. Etiologies include parainfectious, paraneoplastic, drug/toxin-induced, autoimmune, and demyelinating diseases [9, 10]. Diagnosis requires exclusion of compressive causes and assessment of CSF for signs of inflammation. MRI of the entire spinal cord is mandatory, typically showing an increased T2-weighted signal in the affected area, indicating edema or spinal cord injury. Lesions often involve the full cross-section of the spinal cord as reflected by the term “transverse” myelitis. The changes may affect both the anterior and posterior columns of the spinal cord [9, 11].
At peak deficit, 50% of patients are completely paraplegic, most with some degree of bladder/bowel dysfunction. Approximately 33% of patients recover with minimal or no permanent deficits, 33% have moderate permanent disability, and 33% are permanently disabled. The reco-very should begin within 1 to 3 months and should continue to progress with exercise and rehabilitation therapy. Recovery typically occurs within 1-3 months from symptom onset and may continue for up to 2 years. If there is no recovery within the first 3 to 6 months, the recovery is unlikely [9-11].
In this patient, the steroid dose was increased and anakinra was continued alongside high dose intravenous immunoglobulin (IVIG), 1 g/kg of body weight for 2 consecutive days. The treatment is presented in Table 1.
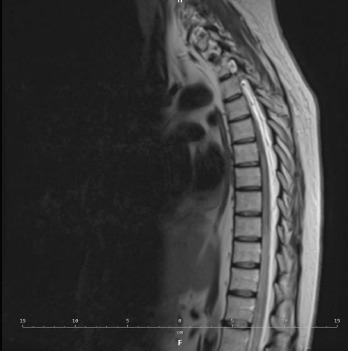
Despite these interventions, no significant clinical improvement was observed. Next MRI, two weeks later at day +34 showed persistent changes, with increased signal intensity in the spinal cord extending from T7 to the cauda equina, with focal, larger lesions resembling a “string of pearls” (Figure II). By day +90, the patient presented complete paralysis of lower limbs, markedly reduced deep sensation, temperature and vibration sense, loss of superficial sensation from T10 level and complete loss of all sensory modalities below the mid-thigh on the right lower limb and below the lower 1/10 of the thigh on the left lower limb.
An analysis of plasma inflammatory markers revealed only mild and transient increase during the entire treatment course (Table 2).
Table 2
Profile of cytokines during treatment
| Day post infusion | 0 | +2 | +3 | +4 | +5 | +10 | +14 |
|---|---|---|---|---|---|---|---|
| CRP (mg/dl): N < 4 | 8 | 80 | 41 | 21 | 13 | < 4 | < 4 |
| IL-6 (pg/ml): N < 4.4 | 2.7 | 457.3 | 74.2 | 1296 | 17.8 | 7.7 | 5.3 |
| Ferritin (ng/ml): N 10-291 | 240.9 | 224.6 | 368.7 | 222.4 | 264.0 | 151.9 | 247.6 |
PET-CT at days +30 and +90 demonstrated a complete metabolic response from lymphoma. In August 2024, she was referred to a neurological rehabilitation department for intensive rehabilitation.
In the follow-up neurological assessment in November 2024, the patient presented persistent flaccid lower limb paralysis, with minimal proximal hip movement. Reflexes in the lower limbs remained absent and there was a complete loss of all sensory modalities, as previously noted. Muscle strength in the upper limbs was normal. The cause of the initially observed upper-limb weakness remains unclear; it may have been symptomatic and related to radiculitis, a resembling Guillain-Barré syndrome. It is possible that these symptoms resolved following the treatment. The patient reported occasional radiating pain from the lower back to the lower limbs, particularly triggered by loud sounds. She was able to independently assume a sitting position. No other symptoms were observed, she was fully oriented and responsive, with an ICE score of 10/10. There were no signs or symptoms of infection, although blood tests revealed hypogammaglobulinemia.
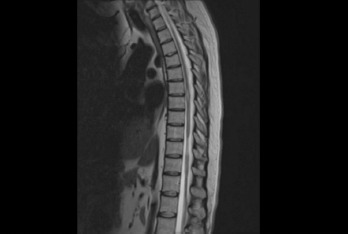
The follow-up MRI from November 2024 revealed persistent areas of increased T2 signal intensity within the spinal cord at the level of T7. No diffusion restriction or contrast enhancement was observed in the lesions. Compared to the baseline examination performed in June 2024, there was a noticeable reduction in spinal cord volume at the level of T8, indicating atrophic changes (Figure III).
Neurological assessment in January 2025 following further rehabilitation showed no clinical improvement. Among patients with transverse myelitis, recovery occurs mostly within the first three months after symptom onset, with rehabilitation improving outcomes. The lack of recovery within the first three to six months predicts poor prognosis [12]. In this case, the likelihood of further recovery is minimal, especially due to atrophic changes of the spine. One year after CAR T-cell infusion, the patient remains in complete remission of lymphoma, however disabled and wheelchair-dependent.
Commentary
Neurotoxicity associated with CAR T-cell therapy is one of the most concerning complications of this treatment. As the number of treated patients increases, reports of atypical neurological symptoms, including myelitis with limb paresis, are also on the rise. To date, several similar cases of myelitis have been described in both pediatric and adult populations, though the clinical course and therapeutic approaches have varied considerably [13-19].
Due to the rarity of the myelitis complication, identifying potential risk factors is challenging. It also remains unclear whether myelitis is directly attributable to CAR T-cell therapy or influenced by other factors, such as prior treatment, leukemic infiltration or viral infection [14, 19]. Distinguishing CAR T-cell-associated neurotoxicity from alternative etiologies is particularly difficult. Multiple mechanisms may be involved in the pathogenesis of this inflammatory response, including cytokine storm, viral infection and spinal cord infarction; most likely, the condition results from a complex interplay between multiple factors [13].
Although elevated cytokine levels are considered a key factor in the pathogenesis of ICANS, it is noteworthy that in some reported cases of myelitis, plasma inflammatory markers were not significantly increased [20]. Similarly, in our patient, no marked elevations of plasma inflammatory markers (ferritin, CRP, IL-6) were observed (Table 2). Moreover, she did not present with other recognized risk factors for neurotoxicity, such as high baseline tumor burden or severe CRS.
First-line therapy for autoimmune TM consists of high-dose intravenous glucocorticoids. Additionally, high- dose intravenous immunoglobulins, and antiviral agents may also be administered. In patients with poor or no response to corticosteroids, plasmapheresis should be considered, as well as other immunomodulatory therapies, such as cyclophosphamide, mycophenolate or ritu-ximab [9-11]. However, in patients who develop TM following CAR T-cell therapy, both diagnosis and treatment are more challenging. These patients often present with cytopenias and hypogammaglobulinemia, may have concurrent infections and are at risk of viral reactivation. Moreover, chemotherapy-related toxicities can overlap with neurological symptoms. In this context, the use of plasmapheresis, additional cytotoxic or immunosuppressive agents, such as rituximab, carries a particularly high risk of severe infections. Most importantly, the extreme rarity of such complications, together with their heterogeneous presentation and clinical course, precludes systematic analysis.
Given its rarity, no established guidelines exist for the investigation and management of these rare, emerging complications [13]. Furthermore, it remains uncertain whether clinical improvements observed in some patients result from therapeutic interventions or occur spontaneously over time, regardless of treatment, while in others, damage appears irreversible [13, 18]. Reporting such unusual toxicities associated with this novel therapy is essential for improving our ability to predict and manage these complications.








