
Introduction
Mucopolysaccharidoses (MPS) are a group of inherited metabolic diseases associated with impaired lysosomal degradation of mucopolysaccharides (known as glycosaminoglycans, GAGs), which include heparan sulfate (HS), dermatan sulfate (DS), keratan sulfate, hyaluronan, and chondroitin sulfate (CS) [1, 2]. GAGs are the main component of the extracellular matrix. DS has a particularly damaging effect on the formation of connective tissue, while HS has an affinity and toxic effect on the central nervous system (CNS) [2].
MPS type III (MPS III) is also called Sanfilippo syndrome and is caused by a deficiency of one of the 4 enzymes responsible for the degradation of HS (Table I). Mutations in the HGSNAT gene (chromosome 8p11.1) which encodes the enzyme heparan-α-glucosaminide N-acetyltransferase (EC 2.3.1.78) are responsible for MPS IIIC (Sanfilippo syndrome type C) [3, 4]. MPS IIIC is a less aggressive form of Sanfilippo syndrome, with an average survival of about 19–34 years. According to Jurecka et al. [5], the overall prevalence of MPS in the Polish population was 1.81 per 100,000 while MPS III was the most frequent one, with a birth prevalence of 0.86 per 100,000 live births.
Table I
Subtypes of mucopolysaccharidosis type III (MPS III)
The aim of this manuscript was to report a case of a patient with MPS IIIC diagnosed at 12 years of age – to raise awareness among pediatricians and pediatric neurologist about the possible misdiagnosis.
Case report
The patient was the first child of Polish parents (unknown father; the mother was affected by schizophrenia) born at 40 weeks of gestation with a weight of 3,890 g, length of 55 cm, and head circumference of 34 cm.
She was able to sit steadily at 10 months of age and walk independently at 17 months of age. She spoke the first words at 12 months of age.
From the age of 3 years, hyperactivity was observed, and the patient was referred to a psychologist. Autistic features and attention deficit hyperactivity disorder with a mild intellectual disability were diagnosed at the age of 5 years. At that time, brain magnetic resonance (MR) and electroencephalography were unremarkable. In the following years, due to behavioral difficulties the patient was treated with various drugs, including methylphenidate, atomoxetine, risperidone, levomepromazine, and chlorprothixene. No clinical improvement was observed.
At the age of 12 years, psychomotor regression, mainly of speech, was noted. At that time, the patient presented with a body mass of 65 kg (> 97th percentile), height of 156 cm (50th percentile) and occipitofrontal circumference of 48 cm (< 3rd percentile), and subtle dysmorphic features (hypertelorism, slightly fused eyebrows). In physical examination, generalized hypotonia, kyphoscoliosis, and moderate intellectual disability were observed. Brain MR revealed widening of the pericerebral spaces supratentorially with a reduced volume of cerebral gyri. No diagnosis was established.
The grandmother of the patient decided to undergo a molecular analysis; whole exome sequencing was performed. Whole exome sequencing revealed the presence of paternal uniparental isodisomy of chromosome 8 as well as the homozygous variant c.1342_1377+1dup located on chromosome 8 in the HGSNAT gene. This variant was not previously reported; according to American College of Medical Genetics criteria, the NM_15241.3:c.1342_1377+1dup variant was assessed to be pathogenic (10 points). The patient was referred for further metabolic investigation.
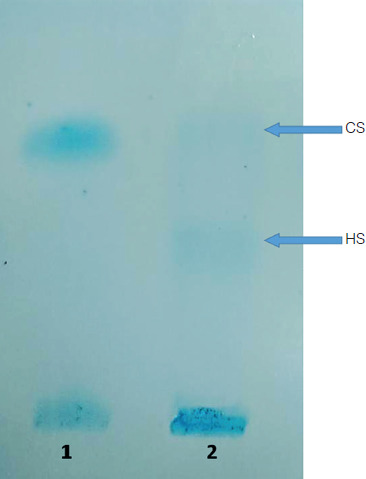
On admission, the patient presented with typical coarse facial features. MPS III diagnosis was established. Urinary GAG electrophoresis revealed the presence of CS and HS bands (Figure 1). An elevated level was observed in the semi-quantitative turbidimetric test with CPC (456 mg/g creatinine; reference range for age: 115 ±61). Markedly low activity of acetyltransferase (0.35 nmol/mg protein/18 h; reference range 40 ±130) was noted in blood leukocytes. The final diagnosis of MPS IIIC was established.
Discussion
The paper presents a case of MPS IIIC firstly presenting with autism spectrum disorder and hyperactivity with normal motor development. During the follow-up, psychomotor regression with no active speech and moderate intellectual disability were observed. The patient was referred for further metabolic work-up only after obtaining the results of molecular analysis.
Clinical symptoms of MPS III (Sanfilippo disease) are similar regardless of the subtype and are characterized by early, progressive degeneration of the CNS with mild somatic symptoms.
All MPS III phenotypes are characterized by a progressive course of the disease with three phases that begin after a period of apparently normal development [4, 6]. In the first phase, usually beginning between the ages of 1 and 3 years, slowing or stabilization of psychomotor development becomes apparent; speech is often more impaired than other cognitive functions [6]. At this stage, motor development is usually normal. The second phase begins around 3–4 years of age and is characterized by progressive cognitive decline and a behavioral phenotype. Behavioral difficulties, including hyperactivity, impulsivity, anxiety, and autistic-like behavior, worsen over time [6]. The third phase begins, usually in adolescence, with the onset of severe dementia and deterioration of motor function [6]. Patients ultimately die most often in the late second or early third decade of life [7]. In milder forms of Sanfilippo disease, longer survival (sixth to seventh decade of life) is observed, with possible mild cognitive impairment.
Somatic symptoms are heterogeneous in the MPS III population and may be less severe than in other forms of MPS. Only about half of MPS III patients have hepatomegaly, and a small percentage have splenomegaly. Skeletal symptoms (scoliosis, kyphosis, lumbar lordosis, hip dysplasia, carpal tunnel syndrome) appear later and are observed only in a minority of patients [4, 6].
In MPS diagnostics, identification of the stored substrate is crucial, including the quantitative and qualitative (using electrophoresis or thin-layer chromatography) analysis of GAGs excreted in urine [8, 9]. The final diagnosis is based on the demonstration of deficiency/lack of activity of a given enzyme in leukocytes or dried blood spot (DBS). Genetic testing should be performed in every patient with suspected MPS.











